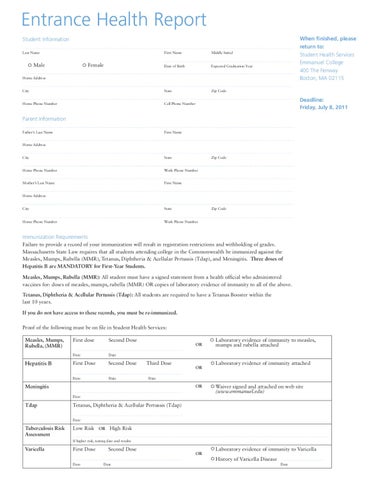
Entrance Health Report When finished, please return to: Student Health Services Emmanuel College 400 The Fenway Boston, MA 02115
Student Information Last Name
First Name
Middle Initial
Date of Birth
Expected Graduation Year
City
State
Zip Code
Home Phone Number
Cell Phone Number
Male Female
Home Address
Deadline: Friday, July 8, 2011
Parent Information Father’s Last Name
First Name
Home Address City
State
Zip Code
Home Phone Number
Work Phone Number
Mother’s Last Name
First Name
Home Address City
State
Zip Code
Home Phone Number
Work Phone Number
Immunization Requirements Failure to provide a record of your immunization will result in registration restrictions and withholding of grades. Massachusetts State Law requires that all students attending college in the Commonwealth be immunized against the Measles, Mumps, Rubella (MMR), Tetanus, Diphtheria & Acellular Pertussis (Tdap), and Meningitis. Three doses of Hepatitis B are MANDATORY for First-Year Students. Measles, Mumps, Rubella (MMR): All student must have a signed statement from a health official who administered vaccines for: doses of measles, mumps, rubella (MMR) OR copies of laboratory evidence of immunity to all of the above. Tetanus, Diphtheria & Acellular Pertussis (Tdap): All students are required to have a Tetanus Booster within the last 10 years. If you do not have access to these records, you must be re-immunized. Proof of the following must be on file in Student Health Services: Measles, Mumps, Rubella, (MMR)
Hepatitis B
First dose
Second Dose
Date
Date
First Dose
Second Dose
Date
Date
OR
Third Dose
OR
Laboratory evidence of immunity to measles, mumps and rubella attached Laboratory evidence of immunity attached
Date
Meningitis
OR
Waiver signed and attached on web site (www.emmanuel.edu)
Date
Tdap
Tetanus, Diphtheria & Acellular Pertussis (Tdap) Date
Tuberculosis Risk Assessment
Low Risk OR High Risk If higher risk, testing date and results
Varicella
First Dose Date
Second Dose Date
OR
Laboratory evidence of immunity to Varicella History of Varicella Disease Date
When finished, please return to: Student Health Services Emmanuel College 400 The Fenway Boston, MA 02115
Student Name:
Please list all medications and dosage you are currently taking:
Please list and describe any medication allergies you have:
Deadline: Friday, July 8, 2011
Please list current medical problems:
Is the student able to fully participate in sports?
Yes
No
If no, please explain:
Health Care Provider’s Signature
Health Care Provider’s Name (please print)
Date
NP
MD
Address
City
State
Zip Code
Phone Number Fax Number
Permission for Medical & Emergency Treatment This information must be completed and signed by a parent or legal guardian for students under 18 years of age. Medical Treatment: This is to certify that permission is granted to Emmanuel College Student Health Services to provide medical treatment for illness, injury or required immunizations for the above named student.
Signature of parent or legal guardian
Emergency Treatment: Permission is granted for emergency treatment (including surgery & anesthesia) for above named student, when parent or guardian is unable to be contacted.
Signature of parent or legal guardian
Health Insurance Information Company Name: Subsriber Name: Policy #: (If possible, please attach a copy of the front and back of the Health Insurance card.)
Please feel free to contact us by phone at 617-735-9817 or e-mail orientation@emmanuel.edu with any questions or concerns.