Form
990
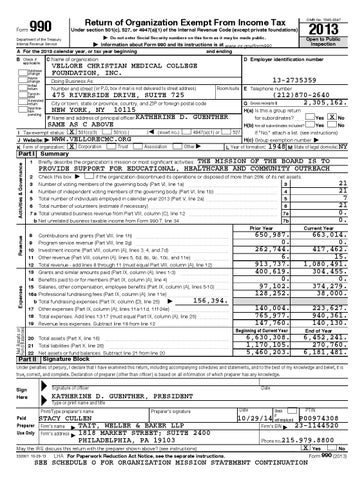
Return of Organization Exempt From Income Tax
OMB No. 1545-0047
| Do not enter Social Security numbers on this form as it may be made public.
Open to Public Inspection
2013
Under section 501(c), 527, or 4947(a)(1) of the Internal Revenue Code (except private foundations)
Department of the Treasury Internal Revenue Service
| Information about Form 990 and its instructions is at www.irs.gov/form990. A For the 2013 calendar year, or tax year beginning and ending
B
C Name of organization
Check if applicable: Address change Name change Initial return Terminated Amended return Application pending
Doing Business As Number and street (or P.O. box if mail is not delivered to street address)
475 RIVERSIDE DRIVE, SUITE 725
Activities & Governance Revenue Expenses
13-2735359 Room/suite E Telephone number
(212)870-2640 2,305,162.
City or town, state or province, country, and ZIP or foreign postal code
NEW YORK, NY
10115
F Name and address of principal officer:KATHERINE
SAME AS C ABOVE 501(c) ( I Tax-exempt status: X 501(c)(3) J Website: | WWW.VELLORECMC.ORG Trust K Form of organization: X Corporation Part I Summary
Net Assets or Fund Balances
D Employer identification number
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC.
D. GUENTHER
) § (insert no.) Association
4947(a)(1) or Other |
G H(a) Is this a group return for subordinates? ~~ H(b) Are all subordinates included? Gross receipts $
Yes X No Yes No 527 If "No," attach a list. (see instructions) H(c) Group exemption number | L Year of formation: 1948 M State of legal domicile: NY
THE MISSION OF THE BOARD IS TO PROVIDE SUPPORT FOR EDUCATIONAL, HEALTHCARE AND COMMUNITY OUTREACH Briefly describe the organization's mission or most significant activities:
1
Check this box | if the organization discontinued its operations or disposed of more than 25% of its net assets. 21 Number of voting members of the governing body (Part VI, line 1a) ~~~~~~~~~~~~~~~~~~~~ 3 21 Number of independent voting members of the governing body (Part VI, line 1b) ~~~~~~~~~~~~~~ 4 7 Total number of individuals employed in calendar year 2013 (Part V, line 2a) ~~~~~~~~~~~~~~~~ 5 21 Total number of volunteers (estimate if necessary) ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 6 0. Total unrelated business revenue from Part VIII, column (C), line 12 ~~~~~~~~~~~~~~~~~~~~ 7a 0. Net unrelated business taxable income from Form 990-T, line 34 •••••••••••••••••••••• 7b Prior Year Current Year 650,987. 663,014. 8 Contributions and grants (Part VIII, line 1h) ~~~~~~~~~~~~~~~~~~~~~ 0. 0. 9 Program service revenue (Part VIII, line 2g) ~~~~~~~~~~~~~~~~~~~~~ 262,744. 417,462. 10 Investment income (Part VIII, column (A), lines 3, 4, and 7d) ~~~~~~~~~~~~~ 6. 15. 11 Other revenue (Part VIII, column (A), lines 5, 6d, 8c, 9c, 10c, and 11e) ~~~~~~~~ 913,737. 1,080,491. 12 Total revenue - add lines 8 through 11 (must equal Part VIII, column (A), line 12) ••• 400,619. 304,455. 13 Grants and similar amounts paid (Part IX, column (A), lines 1-3) ~~~~~~~~~~~ 0. 0. 14 Benefits paid to or for members (Part IX, column (A), line 4) ~~~~~~~~~~~~~ 97,102. 374,279. 15 Salaries, other compensation, employee benefits (Part IX, column (A), lines 5-10) ~~~ 128,252. 38,000. 16a Professional fundraising fees (Part IX, column (A), line 11e)~~~~~~~~~~~~~~ 156,394. | b Total fundraising expenses (Part IX, column (D), line 25) 2 3 4 5 6 7a b
140,004. 765,977. 147,760.
17 Other expenses (Part IX, column (A), lines 11a-11d, 11f-24e) ~~~~~~~~~~~~~ 18 Total expenses. Add lines 13-17 (must equal Part IX, column (A), line 25) ~~~~~~~ 19 Revenue less expenses. Subtract line 18 from line 12 ••••••••••••••••
Beginning of Current Year 20 Total assets (Part X, line 16) ~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 21 Total liabilities (Part X, line 26) ~~~~~~~~~~~~~~~~~~~~~~~~~~~ 22 Net assets or fund balances. Subtract line 21 from line 20 ••••••••••••••
Part II
6,630,308. 1,170,105. 5,460,203.
223,627. 940,361. 140,130.
End of Year
6,452,241. 270,760. 6,181,481.
Signature Block
Under penalties of perjury, I declare that I have examined this return, including accompanying schedules and statements, and to the best of my knowledge and belief, it is true, correct, and complete. Declaration of preparer (other than officer) is based on all information of which preparer has any knowledge.
= =
Sign Here
Signature of officer Type or print name and title
Print/Type preparer's name
Paid Preparer Use Only
Date
KATHERINE D. GUENTHER, PRESIDENT Preparer's signature
STACY CULLEN TAIT, WELLER & BAKER LLP Firm's name 1818 MARKET STREET; SUITE 2400 Firm's address PHILADELPHIA, PA 19103
9 9
Date
10/29/14
Check if self-employed
Firm's EIN
9
PTIN
P00974308 23-1144520
Phone no.215.979.8800
May the IRS discuss this return with the preparer shown above? (see instructions) ••••••••••••••••••••• 332001 10-29-13 LHA For Paperwork Reduction Act Notice, see the separate instructions.
X
SEE SCHEDULE O FOR ORGANIZATION MISSION STATEMENT CONTINUATION
Yes No Form 990 (2013)
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Form 990 (2013) Part III Statement of Program Service Accomplishments 1
13-2735359
Page 2
Check if Schedule O contains a response or note to any line in this Part III •••••••••••••••••••••••••••• Briefly describe the organization's mission:
X
THE FOUNDATION'S MISSION IS TO PROVIDE A FOCUS FOR EXCELLENCE AND INTEGRITY AT CHRISTIAN MEDICAL COLLEGE THROUGH PARTICIPATION IN AND CONTINUING SUPPORT OF CMC'S DRIVE TO MAINTAIN EXCELLENCE.
4a
Did the organization undertake any significant program services during the year which were not listed on the prior Form 990 or 990-EZ? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Yes X No If "Yes," describe these new services on Schedule O. Did the organization cease conducting, or make significant changes in how it conducts, any program services?~~~~~~ Yes X No If "Yes," describe these changes on Schedule O. Describe the organization's program service accomplishments for each of its three largest program services, as measured by expenses. Section 501(c)(3) and 501(c)(4) organizations are required to report the amount of grants and allocations to others, the total expenses, and revenue, if any, for each program service reported. 657,714. including grants of $ 304,455. ) (Revenue $ (Code: ) (Expenses $ )
4b
(Code:
) (Expenses $
including grants of $
) (Revenue $
)
4c
(Code:
) (Expenses $
including grants of $
) (Revenue $
)
4d
Other program services (Describe in Schedule O.) including grants of $ (Expenses $ 657,714. Total program service expenses |
2
3 4
4e
FUNDING EQUIPMENT, MEDICAL SUPPLIES, SCHOLARSHIPS, AND OTHER RESOURCES FOR THE CHRISTIAN MEDICAL COLLEGE AND HOSPITAL IN VELLORE INDIA.
332002 10-29-13
09481029 758275 3064.000
) (Revenue $
) Form 990 (2013)
2 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Form 990 (2013) Part IV Checklist of Required Schedules
13-2735359
Page 3 Yes
1 2 3 4 5 6 7 8 9
10 11 a b c d e f 12a b 13 14a b
15 16
Is the organization described in section 501(c)(3) or 4947(a)(1) (other than a private foundation)? If "Yes," complete Schedule A ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Is the organization required to complete Schedule B, Schedule of Contributors? ~~~~~~~~~~~~~~~~~~~~~~ Did the organization engage in direct or indirect political campaign activities on behalf of or in opposition to candidates for public office? If "Yes," complete Schedule C, Part I ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Section 501(c)(3) organizations. Did the organization engage in lobbying activities, or have a section 501(h) election in effect during the tax year? If "Yes," complete Schedule C, Part II ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Is the organization a section 501(c)(4), 501(c)(5), or 501(c)(6) organization that receives membership dues, assessments, or similar amounts as defined in Revenue Procedure 98-19? If "Yes," complete Schedule C, Part III ~~~~~~~~~~~~~~ Did the organization maintain any donor advised funds or any similar funds or accounts for which donors have the right to provide advice on the distribution or investment of amounts in such funds or accounts? If "Yes," complete Schedule D, Part I Did the organization receive or hold a conservation easement, including easements to preserve open space, the environment, historic land areas, or historic structures? If "Yes," complete Schedule D, Part II~~~~~~~~~~~~~~ Did the organization maintain collections of works of art, historical treasures, or other similar assets? If "Yes," complete Schedule D, Part III ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization report an amount in Part X, line 21, for escrow or custodial account liability; serve as a custodian for amounts not listed in Part X; or provide credit counseling, debt management, credit repair, or debt negotiation services? If "Yes," complete Schedule D, Part IV ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization, directly or through a related organization, hold assets in temporarily restricted endowments, permanent endowments, or quasi-endowments? If "Yes," complete Schedule D, Part V ~~~~~~~~~~~~~~~~~~~~~~~~ If the organization's answer to any of the following questions is "Yes," then complete Schedule D, Parts VI, VII, VIII, IX, or X as applicable. Did the organization report an amount for land, buildings, and equipment in Part X, line 10? If "Yes," complete Schedule D, Part VI ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization report an amount for investments - other securities in Part X, line 12 that is 5% or more of its total assets reported in Part X, line 16? If "Yes," complete Schedule D, Part VII ~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization report an amount for investments - program related in Part X, line 13 that is 5% or more of its total assets reported in Part X, line 16? If "Yes," complete Schedule D, Part VIII ~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization report an amount for other assets in Part X, line 15 that is 5% or more of its total assets reported in Part X, line 16? If "Yes," complete Schedule D, Part IX ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization report an amount for other liabilities in Part X, line 25? If "Yes," complete Schedule D, Part X ~~~~~~ Did the organization's separate or consolidated financial statements for the tax year include a footnote that addresses the organization's liability for uncertain tax positions under FIN 48 (ASC 740)? If "Yes," complete Schedule D, Part X ~~~~ Did the organization obtain separate, independent audited financial statements for the tax year? If "Yes," complete Schedule D, Parts XI and XII ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Was the organization included in consolidated, independent audited financial statements for the tax year? If "Yes," and if the organization answered "No" to line 12a, then completing Schedule D, Parts XI and XII is optional ~~~~~ Is the organization a school described in section 170(b)(1)(A)(ii)? If "Yes," complete Schedule E ~~~~~~~~~~~~~~ Did the organization maintain an office, employees, or agents outside of the United States? ~~~~~~~~~~~~~~~~ Did the organization have aggregate revenues or expenses of more than $10,000 from grantmaking, fundraising, business, investment, and program service activities outside the United States, or aggregate foreign investments valued at $100,000 or more? If "Yes," complete Schedule F, Parts I and IV ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization report on Part IX, column (A), line 3, more than $5,000 of grants or other assistance to or for any foreign organization? If "Yes," complete Schedule F, Parts II and IV ~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization report on Part IX, column (A), line 3, more than $5,000 of aggregate grants or other assistance to or for foreign individuals? If "Yes," complete Schedule F, Parts III and IV ~~~~~~~~~~~~~~~~~~~~~~~~~~
Did the organization report a total of more than $15,000 of expenses for professional fundraising services on Part IX, column (A), lines 6 and 11e? If "Yes," complete Schedule G, Part I ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 18 Did the organization report more than $15,000 total of fundraising event gross income and contributions on Part VIII, lines 1c and 8a? If "Yes," complete Schedule G, Part II ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 19 Did the organization report more than $15,000 of gross income from gaming activities on Part VIII, line 9a? If "Yes," complete Schedule G, Part III ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 20a Did the organization operate one or more hospital facilities? If "Yes," complete Schedule H ~~~~~~~~~~~~~~~~ b If "Yes" to line 20a, did the organization attach a copy of its audited financial statements to this return? ••••••••••
1 2
09481029 758275 3064.000
X X
3
X
4
X
5
X
6
X
7
X
8
X
9
X
10
X
11a
X
11b
X
11c
X
11d 11e
X X
11f
X
12a
X X X X
12b 13 14a
14b
X
15
X X
16
17
332003 10-29-13
No
17 18
X X
X 19 X 20a 20b Form 990 (2013)
3 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Form 990 (2013) Part IV Checklist of Required Schedules (continued)
13-2735359
Page 4 Yes
21 22 23
24a
b c d 25a b
26
27
28 a b c 29 30 31 32 33 34 35a b 36 37 38
Did the organization report more than $5,000 of grants or other assistance to any domestic organization or government on Part IX, column (A), line 1? If "Yes," complete Schedule I, Parts I and II ~~~~~~~~~~~~~~~~~~ Did the organization report more than $5,000 of grants or other assistance to individuals in the United States on Part IX, column (A), line 2? If "Yes," complete Schedule I, Parts I and III ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization answer "Yes" to Part VII, Section A, line 3, 4, or 5 about compensation of the organization's current and former officers, directors, trustees, key employees, and highest compensated employees? If "Yes," complete Schedule J ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization have a tax-exempt bond issue with an outstanding principal amount of more than $100,000 as of the last day of the year, that was issued after December 31, 2002? If "Yes," answer lines 24b through 24d and complete Schedule K. If "No", go to line 25a ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization invest any proceeds of tax-exempt bonds beyond a temporary period exception? ~~~~~~~~~~~ Did the organization maintain an escrow account other than a refunding escrow at any time during the year to defease any tax-exempt bonds? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization act as an "on behalf of" issuer for bonds outstanding at any time during the year? ~~~~~~~~~~~ Section 501(c)(3) and 501(c)(4) organizations. Did the organization engage in an excess benefit transaction with a disqualified person during the year? If "Yes," complete Schedule L, Part I ~~~~~~~~~~~~~~~~~~~~~~~~~ Is the organization aware that it engaged in an excess benefit transaction with a disqualified person in a prior year, and that the transaction has not been reported on any of the organization's prior Forms 990 or 990-EZ? If "Yes," complete Schedule L, Part I ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization report any amount on Part X, line 5, 6, or 22 for receivables from or payables to any current or former officers, directors, trustees, key employees, highest compensated employees, or disqualified persons? If so, complete Schedule L, Part II ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization provide a grant or other assistance to an officer, director, trustee, key employee, substantial contributor or employee thereof, a grant selection committee member, or to a 35% controlled entity or family member of any of these persons? If "Yes," complete Schedule L, Part III ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Was the organization a party to a business transaction with one of the following parties (see Schedule L, Part IV instructions for applicable filing thresholds, conditions, and exceptions): A current or former officer, director, trustee, or key employee? If "Yes," complete Schedule L, Part IV ~~~~~~~~~~~ A family member of a current or former officer, director, trustee, or key employee? If "Yes," complete Schedule L, Part IV ~~ An entity of which a current or former officer, director, trustee, or key employee (or a family member thereof) was an officer, director, trustee, or direct or indirect owner? If "Yes," complete Schedule L, Part IV~~~~~~~~~~~~~~~~~~~~~ Did the organization receive more than $25,000 in non-cash contributions? If "Yes," complete Schedule M ~~~~~~~~~ Did the organization receive contributions of art, historical treasures, or other similar assets, or qualified conservation contributions? If "Yes," complete Schedule M ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization liquidate, terminate, or dissolve and cease operations? If "Yes," complete Schedule N, Part I ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization sell, exchange, dispose of, or transfer more than 25% of its net assets? If "Yes," complete Schedule N, Part II ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization own 100% of an entity disregarded as separate from the organization under Regulations sections 301.7701-2 and 301.7701-3? If "Yes," complete Schedule R, Part I ~~~~~~~~~~~~~~~~~~~~~~~~ Was the organization related to any tax-exempt or taxable entity? If "Yes," complete Schedule R, Part II, III, or IV, and Part V, line 1 ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization have a controlled entity within the meaning of section 512(b)(13)? ~~~~~~~~~~~~~~~~~~ If "Yes" to line 35a, did the organization receive any payment from or engage in any transaction with a controlled entity within the meaning of section 512(b)(13)? If "Yes," complete Schedule R, Part V, line 2 ~~~~~~~~~~~~~~~~~~~ Section 501(c)(3) organizations. Did the organization make any transfers to an exempt non-charitable related organization? If "Yes," complete Schedule R, Part V, line 2 ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization conduct more than 5% of its activities through an entity that is not a related organization and that is treated as a partnership for federal income tax purposes? If "Yes," complete Schedule R, Part VI ~~~~~~~~ Did the organization complete Schedule O and provide explanations in Schedule O for Part VI, lines 11b and 19? Note. All Form 990 filers are required to complete Schedule O •••••••••••••••••••••••••••••••
332004 10-29-13
09481029 758275 3064.000
No
21
X
22
X
23
24a 24b
X X
24c 24d 25a
X
25b
X
26
X
27
X
28a 28b
X X
28c 29
X X
30
X
31
X
32
X
33
X
34 35a
X X
35b 36
X
37
X
X 38 Form 990 (2013)
4 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Form 990 (2013) Part V Statements Regarding Other IRS Filings and Tax Compliance
13-2735359
Page 5
Check if Schedule O contains a response or note to any line in this Part V ••••••••••••••••••••••••••• Yes 6 1a Enter the number reported in Box 3 of Form 1096. Enter -0- if not applicable ~~~~~~~~~~~ 1a 0 b Enter the number of Forms W-2G included in line 1a. Enter -0- if not applicable ~~~~~~~~~~ 1b c Did the organization comply with backup withholding rules for reportable payments to vendors and reportable gaming X (gambling) winnings to prize winners? ••••••••••••••••••••••••••••••••••••••••••• 1c 2a Enter the number of employees reported on Form W-3, Transmittal of Wage and Tax Statements, 7 filed for the calendar year ending with or within the year covered by this return ~~~~~~~~~~ 2a b If at least one is reported on line 2a, did the organization file all required federal employment tax returns?~~~~~~~~~~ Note. If the sum of lines 1a and 2a is greater than 250, you may be required to e-file (see instructions) ~~~~~~~~~~~ 3a Did the organization have unrelated business gross income of $1,000 or more during the year? ~~~~~~~~~~~~~~ b If "Yes," has it filed a Form 990-T for this year? If "No," to line 3b, provide an explanation in Schedule O ~~~~~~~~~~ 4a At any time during the calendar year, did the organization have an interest in, or a signature or other authority over, a financial account in a foreign country (such as a bank account, securities account, or other financial account)?~~~~~~~ b If "Yes," enter the name of the foreign country: J See instructions for filing requirements for Form TD F 90-22.1, Report of Foreign Bank and Financial Accounts. 5a Was the organization a party to a prohibited tax shelter transaction at any time during the tax year? ~~~~~~~~~~~~ b Did any taxable party notify the organization that it was or is a party to a prohibited tax shelter transaction?~~~~~~~~~ c If "Yes," to line 5a or 5b, did the organization file Form 8886-T? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 6a Does the organization have annual gross receipts that are normally greater than $100,000, and did the organization solicit any contributions that were not tax deductible as charitable contributions? ~~~~~~~~~~~~~~~~~~~~~~~~ b If "Yes," did the organization include with every solicitation an express statement that such contributions or gifts were not tax deductible? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 7 Organizations that may receive deductible contributions under section 170(c). a Did the organization receive a payment in excess of $75 made partly as a contribution and partly for goods and services provided to the payor? b If "Yes," did the organization notify the donor of the value of the goods or services provided? ~~~~~~~~~~~~~~~ c Did the organization sell, exchange, or otherwise dispose of tangible personal property for which it was required to file Form 8282? •••••••••••••••••••••••••••••••••••••••••••••••••••• d If "Yes," indicate the number of Forms 8282 filed during the year ~~~~~~~~~~~~~~~~ 7d e Did the organization receive any funds, directly or indirectly, to pay premiums on a personal benefit contract? ~~~~~~~ f Did the organization, during the year, pay premiums, directly or indirectly, on a personal benefit contract? ~~~~~~~~~ g If the organization received a contribution of qualified intellectual property, did the organization file Form 8899 as required?~ h If the organization received a contribution of cars, boats, airplanes, or other vehicles, did the organization file a Form 1098-C? 8 Sponsoring organizations maintaining donor advised funds and section 509(a)(3) supporting organizations. Did the supporting organization, or a donor advised fund maintained by a sponsoring organization, have excess business holdings at any time during the year? 9
a b 10 a b 11 a b 12a b 13 a b c 14a b
Sponsoring organizations maintaining donor advised funds. Did the organization make any taxable distributions under section 4966?~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization make a distribution to a donor, donor advisor, or related person? ~~~~~~~~~~~~~~~~~~~ Section 501(c)(7) organizations. Enter: Initiation fees and capital contributions included on Part VIII, line 12 ~~~~~~~~~~~~~~~ 10a Gross receipts, included on Form 990, Part VIII, line 12, for public use of club facilities ~~~~~~ 10b Section 501(c)(12) organizations. Enter: Gross income from members or shareholders ~~~~~~~~~~~~~~~~~~~~~~~~~~ 11a Gross income from other sources (Do not net amounts due or paid to other sources against amounts due or received from them.) ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 11b Section 4947(a)(1) non-exempt charitable trusts. Is the organization filing Form 990 in lieu of Form 1041? If "Yes," enter the amount of tax-exempt interest received or accrued during the year •••••• 12b Section 501(c)(29) qualified nonprofit health insurance issuers. Is the organization licensed to issue qualified health plans in more than one state? ~~~~~~~~~~~~~~~~~~~~~ Note. See the instructions for additional information the organization must report on Schedule O. Enter the amount of reserves the organization is required to maintain by the states in which the organization is licensed to issue qualified health plans ~~~~~~~~~~~~~~~~~~~~~~ 13b Enter the amount of reserves on hand ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 13c Did the organization receive any payments for indoor tanning services during the tax year? ~~~~~~~~~~~~~~~~ If "Yes," has it filed a Form 720 to report these payments? If "No," provide an explanation in Schedule O ••••••••••
332005 10-29-13
09481029 758275 3064.000
2b 3a 3b 4a
5a 5b 5c 6a
No
X X X X X X
6b 7a 7b 7c 7e 7f 7g 7h
X X X X
8 9a 9b
12a
13a
X 14a 14b Form 990 (2013)
5 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. 13-2735359 Form 990 (2013) Page 6 For each "Yes" response to lines 2 through 7b below, and for a "No" response Part VI Governance, Management, and Disclosure to line 8a, 8b, or 10b below, describe the circumstances, processes, or changes in Schedule O. See instructions.
Check if Schedule O contains a response or note to any line in this Part VI •••••••••••••••••••••••••••
Section A. Governing Body and Management 1a Enter the number of voting members of the governing body at the end of the tax year ~~~~~~ If there are material differences in voting rights among members of the governing body, or if the governing body delegated broad authority to an executive committee or similar committee, explain in Schedule O.
1a
Yes
21
21 1b b Enter the number of voting members included in line 1a, above, who are independent ~~~~~~ 2 Did any officer, director, trustee, or key employee have a family relationship or a business relationship with any other officer, director, trustee, or key employee? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 2 3 Did the organization delegate control over management duties customarily performed by or under the direct supervision of officers, directors, or trustees, or key employees to a management company or other person? ~~~~~~~~~~~~~~ 3 4 4 Did the organization make any significant changes to its governing documents since the prior Form 990 was filed? ~~~~~ 5 5 Did the organization become aware during the year of a significant diversion of the organization's assets? ~~~~~~~~~ 6 6 Did the organization have members or stockholders? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 7a Did the organization have members, stockholders, or other persons who had the power to elect or appoint one or more members of the governing body? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 7a b Are any governance decisions of the organization reserved to (or subject to approval by) members, stockholders, or persons other than the governing body? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 7b 8 Did the organization contemporaneously document the meetings held or written actions undertaken during the year by the following: a The governing body? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ b Each committee with authority to act on behalf of the governing body? ~~~~~~~~~~~~~~~~~~~~~~~~~~ Is there any officer, director, trustee, or key employee listed in Part VII, Section A, who cannot be reached at the organization's mailing address? If "Yes," provide the names and addresses in Schedule O ••••••••••••••••• Section B. Policies (This Section B requests information about policies not required by the Internal Revenue Code.)
8a 8b
X X
13 14 15 a b 16a b
Did the organization have a written whistleblower policy? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Did the organization have a written document retention and destruction policy? ~~~~~~~~~~~~~~~~~~~~~~ Did the process for determining compensation of the following persons include a review and approval by independent persons, comparability data, and contemporaneous substantiation of the deliberation and decision? The organization's CEO, Executive Director, or top management official ~~~~~~~~~~~~~~~~~~~~~~~~~~ Other officers or key employees of the organization ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ If "Yes" to line 15a or 15b, describe the process in Schedule O (see instructions). Did the organization invest in, contribute assets to, or participate in a joint venture or similar arrangement with a taxable entity during the year? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ If "Yes," did the organization follow a written policy or procedure requiring the organization to evaluate its participation in joint venture arrangements under applicable federal tax law, and take steps to safeguard the organization's exempt status with respect to such arrangements? ••••••••••••••••••••••••••••••••••••
X X X
Section C. Disclosure 17 18
19 20
10a 10b 11a
X
12a 12b
X X
15a 15b
X
X
9
12c 13 14
X
X
Yes
b Were officers, directors, or trustees, and key employees required to disclose annually interests that could give rise to conflicts? ~~~~~~ c Did the organization regularly and consistently monitor and enforce compliance with the policy? If "Yes," describe in Schedule O how this was done ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~
No
X
9
10a Did the organization have local chapters, branches, or affiliates? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ b If "Yes," did the organization have written policies and procedures governing the activities of such chapters, affiliates, and branches to ensure their operations are consistent with the organization's exempt purposes? ~~~~~~~~~~~~~ 11a Has the organization provided a complete copy of this Form 990 to all members of its governing body before filing the form? b Describe in Schedule O the process, if any, used by the organization to review this Form 990. 12a Did the organization have a written conflict of interest policy? If "No," go to line 13 ~~~~~~~~~~~~~~~~~~~~
X
X X
X
16a
No
X
X
X X
16b
List the states with which a copy of this Form 990 is required to be filed JNY Section 6104 requires an organization to make its Forms 1023 (or 1024 if applicable), 990, and 990-T (Section 501(c)(3)s only) available for public inspection. Indicate how you made these available. Check all that apply. X Own website X Upon request Another's website Other (explain in Schedule O) Describe in Schedule O whether (and if so, how), the organization made its governing documents, conflict of interest policy, and financial statements available to the public during the tax year. State the name, physical address, and telephone number of the person who possesses the books and records of the organization: |
TEJAL SHAH - 212-870-2640 475 RIVERSIDE DRIVE, SUITE 725, NEW YORK, NY
332006 10-29-13
09481029 758275 3064.000
10115
Form 990 (2013) 6 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. 13-2735359 Form 990 (2013) Part VII Compensation of Officers, Directors, Trustees, Key Employees, Highest Compensated Employees, and Independent Contractors
Page 7
Check if Schedule O contains a response or note to any line in this Part VII ••••••••••••••••••••••••••• Section A. Officers, Directors, Trustees, Key Employees, and Highest Compensated Employees 1a Complete this table for all persons required to be listed. Report compensation for the calendar year ending with or within the organization's tax year. ¥ List all of the organization's current officers, directors, trustees (whether individuals or organizations), regardless of amount of compensation. Enter -0- in columns (D), (E), and (F) if no compensation was paid. ¥ List all of the organization's current key employees, if any. See instructions for definition of "key employee." ¥ List the organization's five current highest compensated employees (other than an officer, director, trustee, or key employee) who received reportable compensation (Box 5 of Form W-2 and/or Box 7 of Form 1099-MISC) of more than $100,000 from the organization and any related organizations. ¥ List all of the organization's former officers, key employees, and highest compensated employees who received more than $100,000 of reportable compensation from the organization and any related organizations. ¥ List all of the organization's former directors or trustees that received, in the capacity as a former director or trustee of the organization, more than $10,000 of reportable compensation from the organization and any related organizations. List persons in the following order: individual trustees or directors; institutional trustees; officers; key employees; highest compensated employees; and former such persons.
(1) DR. MARK STEINHOFF DIRECTOR (2) DR. MADELON FINKEL SECRETARY (3) MR. GEORGE VARUGHESE VICE CHAIRMAN (4) MR. PRASAD PALLA TREASURER (5) DR. S. BALASUBRAMANIAM DIRECTOR (6) DR. ROHAN GANGULI DIRECTOR (7) DR. MARGARET KUMAR, PHD DIRECTOR (8) DR. BIBHUTI MISHRA DIRECTOR (9) DR. HONORINE WARD CHAIRMAN OF THE BOARD (10) MRS. EMMA KOSHY DIRECTOR (11) DR. ALBERT JOHNSON DIRECTOR (12) DR. RAJ NARAYAN DIRECTOR (13) DR. THOMAS PHILIPS. PHD DIRECTOR (14) JAMSHED BHARUCHA, PHD DIRECTOR (15) LISA BEARDLEY -HARDY, PHD DIRECTOR (16) MEREDITH A. HAWKINS DIRECTOR (17) REV. CANON GORGE I. KOVOOR DIRECTOR 332007 10-29-13
09481029 758275 3064.000
0.80 0.50 0.80 0.50 0.50 0.50 0.50 0.50 0.50 0.50 0.50 0.50 0.50 0.50 0.50 0.50
X
Former
Highest compensated employee
Key employee
Officer
Institutional trustee
0.50
Individual trustee or director
Check this box if neither the organization nor any related organization compensated any current officer, director, or trustee. (A) (B) (C) (D) (E) Position Name and Title Average Reportable Reportable (do not check more than one hours per box, unless person is both an compensation compensation officer and a director/trustee) week from from related (list any the organizations hours for organization (W-2/1099-MISC) related (W-2/1099-MISC) organizations below line)
(F) Estimated amount of other compensation from the organization and related organizations
0.
0.
0.
X
X
0.
0.
0.
X
X
0.
0.
0.
X
X
0.
0.
0.
X
0.
0.
0.
X
0.
0.
0.
X
0.
0.
0.
X
0.
0.
0.
0.
0.
0.
X
0.
0.
0.
X
0.
0.
0.
X
0.
0.
0.
X
0.
0.
0.
X
0.
0.
0.
X
0.
0.
0.
X
0.
0.
0.
X
0.
0.
0.
X
X
Form 990 (2013) 7 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC.
1b c d 2
Former
Highest compensated employee
Officer
Institutional trustee
0.50
Key employee
(18) RANJIT MATHEW DIRECTOR (19) PHILIP T. NINAN DIRECTOR (20) WILLIAM S. SCUDDER DIRECTOR (21) CHRISTINE WANKE, MD DIRECTOR (22) KATHERINE GUENTHER PRESIDENT
Individual trustee or director
13-2735359 Page 8 Form 990 (2013) (continued) Part VII Section A. Officers, Directors, Trustees, Key Employees, and Highest Compensated Employees (B) (C) (A) (D) (E) (F) Position Average Name and title Reportable Reportable Estimated (do not check more than one hours per box, unless person is both an compensation compensation amount of officer and a director/trustee) week from from related other (list any the organizations compensation hours for organization (W-2/1099-MISC) from the related (W-2/1099-MISC) organization organizations and related below organizations line) X
0.
0.
0.
X
0.
0.
0.
X
0.
0.
0.
X
0.
0.
0.
150,000.
0.
47,247.
150,000. 0. Sub-total ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ | 0. 0. Total from continuation sheets to Part VII, Section A ~~~~~~~~~~ | 150,000. 0. Total (add lines 1b and 1c) •••••••••••••••••••••••• | Total number of individuals (including but not limited to those listed above) who received more than $100,000 of reportable compensation from the organization |
47,247. 0. 47,247.
0.50 0.50 0.50 35.00
X
1 Yes
3
Did the organization list any former officer, director, or trustee, key employee, or highest compensated employee on line 1a? If "Yes," complete Schedule J for such individual ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 4 For any individual listed on line 1a, is the sum of reportable compensation and other compensation from the organization and related organizations greater than $150,000? If "Yes," complete Schedule J for such individual~~~~~~~~~~~~~ 5 Did any person listed on line 1a receive or accrue compensation from any unrelated organization or individual for services rendered to the organization? If "Yes," complete Schedule J for such person •••••••••••••••••••••••• Section B. Independent Contractors
X
3 4
X
5
1
Complete this table for your five highest compensated independent contractors that received more than $100,000 of compensation from the organization. Report compensation for the calendar year ending with or within the organization's tax year. (A) (B) (C) Name and business address Description of services Compensation NONE
2
Total number of independent contractors (including but not limited to those listed above) who received more than 0 $100,000 of compensation from the organization |
332008 10-29-13
09481029 758275 3064.000
No
X
Form 990 (2013)
8 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Form 990 (2013) Part VIII Statement of Revenue
13-2735359
Page 9
Contributions, Gifts, Grants and Other Similar Amounts
1 a b c d e f
Program Service Revenue
Check if Schedule O contains a response or note to any line in this Part VIII ••••••••••••••••••••••••• (A) (B) (C) (D) Revenue excluded Related or Unrelated Total revenue from tax under exempt function business sections revenue revenue 512 - 514
2
3 4 5 6
Other Revenue
7
8
9
10
11
12
Federated campaigns ~~~~~~ Membership dues ~~~~~~~~ Fundraising events ~~~~~~~~ Related organizations ~~~~~~ Government grants (contributions) All other contributions, gifts, grants, and similar amounts not included above ~~
6,867.
1a 1b 1c 1d 1e
93,037.
1f
563,110.
g Noncash contributions included in lines 1a-1f: $ h Total. Add lines 1a-1f ••••••••••••••••• | Business Code a b c d e f All other program service revenue ~~~~~ g Total. Add lines 2a-2f ••••••••••••••••• | Investment income (including dividends, interest, and other similar amounts)~~~~~~~~~~~~~~~~~ | Income from investment of tax-exempt bond proceeds | Royalties ••••••••••••••••••••••• | (i) Real (ii) Personal a Gross rents ~~~~~~~ b Less: rental expenses ~~~ c Rental income or (loss) ~~ d Net rental income or (loss) •••••••••••••• | a Gross amount from sales of (i) Securities (ii) Other 1,505,897. assets other than inventory b Less: cost or other basis 1,224,671. and sales expenses ~~~ 281,226. c Gain or (loss) ~~~~~~~ d Net gain or (loss) ••••••••••••••••••• | a Gross income from fundraising events (not including $ of contributions reported on line 1c). See Part IV, line 18 ~~~~~~~~~~~~~ a b Less: direct expenses~~~~~~~~~~ b c Net income or (loss) from fundraising events ••••• | a Gross income from gaming activities. See Part IV, line 19 ~~~~~~~~~~~~~ a b Less: direct expenses ~~~~~~~~~ b c Net income or (loss) from gaming activities •••••• | a Gross sales of inventory, less returns and allowances ~~~~~~~~~~~~~ a b Less: cost of goods sold ~~~~~~~~ b c Net income or (loss) from sales of inventory •••••• | Miscellaneous Revenue Business Code 611710 a MISC INCOME b c d All other revenue ~~~~~~~~~~~~~ e Total. Add lines 11a-11d ~~~~~~~~~~~~~~~ | Total revenue. See instructions. ••••••••••••• |
332009 10-29-13
09481029 758275 3064.000
663,014.
136,236.
136,236.
281,226.
281,226.
15.
15.
15. 1,080,491.
15.
0.
417,462. Form 990 (2013)
9 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Form 990 (2013) Part IX Statement of Functional Expenses
13-2735359
Page 10
Section 501(c)(3) and 501(c)(4) organizations must complete all columns. All other organizations must complete column (A). Check if Schedule O contains a response or note to any line in this Part IX •••••••••••••••••••••••••• (A) (B) (C) (D) Total expenses Program service Management and Fundraising expenses general expenses expenses Grants and other assistance to governments and organizations in the United States. See Part IV, line 21
Do not include amounts reported on lines 6b, 7b, 8b, 9b, and 10b of Part VIII. 1 2 3
4 5 6
Grants and other assistance to individuals in the United States. See Part IV, line 22 ~~~ Grants and other assistance to governments, organizations, and individuals outside the United States. See Part IV, lines 15 and 16 ~ Benefits paid to or for members ~~~~~~~ Compensation of current officers, directors, trustees, and key employees ~~~~~~~~ Compensation not included above, to disqualified persons (as defined under section 4958(f)(1)) and persons described in section 4958(c)(3)(B) ~~~
7 8
Other salaries and wages ~~~~~~~~~~ Pension plan accruals and contributions (include section 401(k) and 403(b) employer contributions)
9 10 11 a b c d e f g
Other employee benefits ~~~~~~~~~~ Payroll taxes ~~~~~~~~~~~~~~~~ Fees for services (non-employees): Management ~~~~~~~~~~~~~~~~ Legal ~~~~~~~~~~~~~~~~~~~~ Accounting ~~~~~~~~~~~~~~~~~ Lobbying ~~~~~~~~~~~~~~~~~~ Professional fundraising services. See Part IV, line 17
12 13 14 15 16 17 18
Advertising and promotion ~~~~~~~~~ Office expenses~~~~~~~~~~~~~~~ Information technology ~~~~~~~~~~~ Royalties ~~~~~~~~~~~~~~~~~~
19 20 21 22 23 24
Investment management fees ~~~~~~~~ Other. (If line 11g amount exceeds 10% of line 25, column (A) amount, list line 11g expenses on Sch O.)
Occupancy ~~~~~~~~~~~~~~~~~ Travel ~~~~~~~~~~~~~~~~~~~ Payments of travel or entertainment expenses for any federal, state, or local public officials Conferences, conventions, and meetings ~~ Interest ~~~~~~~~~~~~~~~~~~ Payments to affiliates ~~~~~~~~~~~~ Depreciation, depletion, and amortization ~~ Insurance ~~~~~~~~~~~~~~~~~ Other expenses. Itemize expenses not covered above. (List miscellaneous expenses in line 24e. If line 24e amount exceeds 10% of line 25, column (A) amount, list line 24e expenses on Schedule O.) ~~
a b c d e All other expenses 25 Total functional expenses. Add lines 1 through 24e 26 Joint costs. Complete this line only if the organization reported in column (B) joint costs from a combined educational campaign and fundraising solicitation. Check here
|
304,455.
304,455.
197,247.
123,852.
37,519.
35,876.
128,690.
83,331.
21,323.
24,036.
14,311. 15,406. 18,625.
11,040. 12,075. 12,060.
86.
3,185. 3,331. 3,479.
20,800.
20,800.
38,000. 26,328.
3,086.
26,328.
38,000.
34,835.
17,357.
10,971.
6,507.
57,425. 2,480.
25,644. 1,606.
2,998. 411.
28,783. 463.
24,549. 30,712.
15,897. 19,887.
4,067. 5,089.
4,585. 5,736.
10,991.
7,117.
1,821.
2,053.
1,350. 5,642.
95.
895. 5,642.
360.
8,515. 940,361.
2,498. 657,714.
6,017. 126,253.
156,394.
if following SOP 98-2 (ASC 958-720)
332010 10-29-13
09481029 758275 3064.000
Form 990 (2013) 10 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
Form 990 (2013)
Part X
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC.
13-2735359
Balance Sheet
Page 11
Check if Schedule O contains a response or note to any line in this Part X ••••••••••••••••••••••••••••• (A) (B) Beginning of year End of year Cash - non-interest-bearing ~~~~~~~~~~~~~~~~~~~~~~~~~ Savings and temporary cash investments ~~~~~~~~~~~~~~~~~~ Pledges and grants receivable, net ~~~~~~~~~~~~~~~~~~~~~ Accounts receivable, net ~~~~~~~~~~~~~~~~~~~~~~~~~~ Loans and other receivables from current and former officers, directors, trustees, key employees, and highest compensated employees. Complete Part II of Schedule L ~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 6 Loans and other receivables from other disqualified persons (as defined under section 4958(f)(1)), persons described in section 4958(c)(3)(B), and contributing employers and sponsoring organizations of section 501(c)(9) voluntary employees' beneficiary organizations (see instr). Complete Part II of Sch L ~~ 7 Notes and loans receivable, net ~~~~~~~~~~~~~~~~~~~~~~~ 8 Inventories for sale or use ~~~~~~~~~~~~~~~~~~~~~~~~~~ 9 Prepaid expenses and deferred charges ~~~~~~~~~~~~~~~~~~ 10 a Land, buildings, and equipment: cost or other 98,544. basis. Complete Part VI of Schedule D ~~~ 10a 46,342. b Less: accumulated depreciation ~~~~~~ 10b 11 Investments - publicly traded securities ~~~~~~~~~~~~~~~~~~~ 12 Investments - other securities. See Part IV, line 11 ~~~~~~~~~~~~~~ 13 Investments - program-related. See Part IV, line 11 ~~~~~~~~~~~~~ 14 Intangible assets ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 15 Other assets. See Part IV, line 11 ~~~~~~~~~~~~~~~~~~~~~~ 16 Total assets. Add lines 1 through 15 (must equal line 34) •••••••••• 17 Accounts payable and accrued expenses ~~~~~~~~~~~~~~~~~~ 18 Grants payable ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 19 Deferred revenue ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 20 Tax-exempt bond liabilities ~~~~~~~~~~~~~~~~~~~~~~~~~ 21 Escrow or custodial account liability. Complete Part IV of Schedule D ~~~~ 22 Loans and other payables to current and former officers, directors, trustees, key employees, highest compensated employees, and disqualified persons. Complete Part II of Schedule L ~~~~~~~~~~~~~~~~~~~~~~~
Liabilities
Assets
1 2 3 4 5
23 24 25
Net Assets or Fund Balances
26
27 28 29
30 31 32 33 34
Secured mortgages and notes payable to unrelated third parties ~~~~~~ Unsecured notes and loans payable to unrelated third parties ~~~~~~~~ Other liabilities (including federal income tax, payables to related third parties, and other liabilities not included on lines 17-24). Complete Part X of Schedule D ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Total liabilities. Add lines 17 through 25 •••••••••••••••••• X and Organizations that follow SFAS 117 (ASC 958), check here | complete lines 27 through 29, and lines 33 and 34. Unrestricted net assets ~~~~~~~~~~~~~~~~~~~~~~~~~~~ Temporarily restricted net assets ~~~~~~~~~~~~~~~~~~~~~~ Permanently restricted net assets ~~~~~~~~~~~~~~~~~~~~~ Organizations that do not follow SFAS 117 (ASC 958), check here | and complete lines 30 through 34. Capital stock or trust principal, or current funds ~~~~~~~~~~~~~~~ Paid-in or capital surplus, or land, building, or equipment fund ~~~~~~~~ Retained earnings, endowment, accumulated income, or other funds ~~~~ Total net assets or fund balances ~~~~~~~~~~~~~~~~~~~~~~ Total liabilities and net assets/fund balances ••••••••••••••••
332011 10-29-13
09481029 758275 3064.000
300,214. 210,485. 1,026,356.
1 2 3 4
294,272. 207,501. 211,029.
5
4,751. 551. 4,998,379.
89,572. 6,630,308. 1,170,105.
6 7 8 9
10c 11 12 13 14 15 16 17 18 19 20 21
26,027. 52,202. 5,661,210.
0. 6,452,241. 270,760.
22 23 24
1,170,105.
25 26
270,760.
1,342,310. 2,163,382. 1,954,511.
27 28 29
1,386,948. 2,835,516. 1,959,017.
5,460,203. 6,630,308.
30 31 32 33 34
6,181,481. 6,452,241. Form 990 (2013)
11 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Form 990 (2013) Part XI Reconciliation of Net Assets Check if Schedule O contains a response or note to any line in this Part XI 1 2 3 4 5 6 7 8 9 10
Page 12
X
•••••••••••••••••••••••••••
Total revenue (must equal Part VIII, column (A), line 12) ~~~~~~~~~~~~~~~~~~~~~~~~~~ Total expenses (must equal Part IX, column (A), line 25) ~~~~~~~~~~~~~~~~~~~~~~~~~~ Revenue less expenses. Subtract line 2 from line 1 ~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Net assets or fund balances at beginning of year (must equal Part X, line 33, column (A)) ~~~~~~~~~~ Net unrealized gains (losses) on investments ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Donated services and use of facilities ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Investment expenses ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Prior period adjustments ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Other changes in net assets or fund balances (explain in Schedule O) ~~~~~~~~~~~~~~~~~~~ Net assets or fund balances at end of year. Combine lines 3 through 9 (must equal Part X, line 33, column (B)) •••••••••••••••••••••••••••••••••••••••••••••••
Part XII Financial Statements and Reporting
13-2735359
1 2 3 4 5 6 7 8 9 10
1,080,491. 940,361. 140,130. 5,460,203. 580,259.
889. 6,181,481.
Check if Schedule O contains a response or note to any line in this Part XII ••••••••••••••••••••••••••• Yes
X
1 2a
b
c
3a b
Accounting method used to prepare the Form 990: Cash Accrual Other If the organization changed its method of accounting from a prior year or checked "Other," explain in Schedule O. Were the organization's financial statements compiled or reviewed by an independent accountant? ~~~~~~~~~~~~ If "Yes," check a box below to indicate whether the financial statements for the year were compiled or reviewed on a separate basis, consolidated basis, or both: Separate basis Consolidated basis Both consolidated and separate basis Were the organization's financial statements audited by an independent accountant? ~~~~~~~~~~~~~~~~~~~ If "Yes," check a box below to indicate whether the financial statements for the year were audited on a separate basis, consolidated basis, or both: X Separate basis Consolidated basis Both consolidated and separate basis If "Yes" to line 2a or 2b, does the organization have a committee that assumes responsibility for oversight of the audit, review, or compilation of its financial statements and selection of an independent accountant?~~~~~~~~~~~~~~~ If the organization changed either its oversight process or selection process during the tax year, explain in Schedule O. As a result of a federal award, was the organization required to undergo an audit or audits as set forth in the Single Audit Act and OMB Circular A-133? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ If "Yes," did the organization undergo the required audit or audits? If the organization did not undergo the required audit or audits, explain why in Schedule O and describe any steps taken to undergo such audits ••••••••••••••••
332012 10-29-13
09481029 758275 3064.000
X
2a
2b
X
2c
X
3a
No
X
3b Form 990 (2013)
12 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
SCHEDULE A
Public Charity Status and Public Support
(Form 990 or 990-EZ)
OMB No. 1545-0047
2013
Complete if the organization is a section 501(c)(3) organization or a section 4947(a)(1) nonexempt charitable trust. Department of the Treasury Open to Public | Attach to Form 990 or Form 990-EZ. Internal Revenue Service Inspection | Information about Schedule A (Form 990 or 990-EZ) and its instructions is at www.irs.gov/form990. Name of the organization VELLORE CHRISTIAN MEDICAL COLLEGE Employer identification number
Part I
FOUNDATION, INC. Reason for Public Charity Status (All organizations must complete this part.) See instructions.
13-2735359
The organization is not a private foundation because it is: (For lines 1 through 11, check only one box.) 1 A church, convention of churches, or association of churches described in section 170(b)(1)(A)(i). 2 A school described in section 170(b)(1)(A)(ii). (Attach Schedule E.) 3 A hospital or a cooperative hospital service organization described in section 170(b)(1)(A)(iii). A medical research organization operated in conjunction with a hospital described in section 170(b)(1)(A)(iii). Enter the hospital's name, 4 city, and state: An organization operated for the benefit of a college or university owned or operated by a governmental unit described in 5 section 170(b)(1)(A)(iv). (Complete Part II.) 6 7
X
8 9
10 11
e f g
h
A federal, state, or local government or governmental unit described in section 170(b)(1)(A)(v). An organization that normally receives a substantial part of its support from a governmental unit or from the general public described in section 170(b)(1)(A)(vi). (Complete Part II.) A community trust described in section 170(b)(1)(A)(vi). (Complete Part II.) An organization that normally receives: (1) more than 33 1/3% of its support from contributions, membership fees, and gross receipts from activities related to its exempt functions - subject to certain exceptions, and (2) no more than 33 1/3% of its support from gross investment income and unrelated business taxable income (less section 511 tax) from businesses acquired by the organization after June 30, 1975. See section 509(a)(2). (Complete Part III.) An organization organized and operated exclusively to test for public safety. See section 509(a)(4). An organization organized and operated exclusively for the benefit of, to perform the functions of, or to carry out the purposes of one or more publicly supported organizations described in section 509(a)(1) or section 509(a)(2). See section 509(a)(3). Check the box that describes the type of supporting organization and complete lines 11e through 11h. a Type I b Type II c Type III - Functionally integrated d Type III - Non-functionally integrated By checking this box, I certify that the organization is not controlled directly or indirectly by one or more disqualified persons other than foundation managers and other than one or more publicly supported organizations described in section 509(a)(1) or section 509(a)(2). If the organization received a written determination from the IRS that it is a Type I, Type II, or Type III supporting organization, check this box ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Since August 17, 2006, has the organization accepted any gift or contribution from any of the following persons? (i) A person who directly or indirectly controls, either alone or together with persons described in (ii) and (iii) below, Yes No the governing body of the supported organization? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 11g(i) (ii) A family member of a person described in (i) above? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 11g(ii) (iii) A 35% controlled entity of a person described in (i) or (ii) above? ~~~~~~~~~~~~~~~~~~~~~~~~ 11g(iii) Provide the following information about the supported organization(s).
(i) Name of supported organization
(ii) EIN
(vi) Is the (iii) Type of organization (iv) Is the organization (v) Did you notify the organization in col. (vii) Amount of monetary in col. (i) listed in your organization in col. (described on lines 1-9 support (i) organized in the above or IRC section governing document? (i) of your support? U.S.? (see instructions)) Yes No Yes No Yes No
Total LHA For Paperwork Reduction Act Notice, see the Instructions for Form 990 or 990-EZ. 332021 09-25-13
09481029 758275 3064.000
Schedule A (Form 990 or 990-EZ) 2013
13 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE 13-2735359 Schedule A (Form 990 or 990-EZ) 2013 FOUNDATION, INC. Part II Support Schedule for Organizations Described in Sections 170(b)(1)(A)(iv) and 170(b)(1)(A)(vi)
Page 2
(Complete only if you checked the box on line 5, 7, or 8 of Part I or if the organization failed to qualify under Part III. If the organization fails to qualify under the tests listed below, please complete Part III.)
Section A. Public Support Calendar year (or fiscal year beginning in) | 1 Gifts, grants, contributions, and membership fees received. (Do not include any "unusual grants.") ~~
(a) 2009
(b) 2010
(c) 2011
(d) 2012
(e) 2013
(f) Total
617,194. 1691686. 698,504. 650,987. 663,014. 4321385.
2 Tax revenues levied for the organization's benefit and either paid to or expended on its behalf ~~~~ 3 The value of services or facilities furnished by a governmental unit to the organization without charge ~ 4 Total. Add lines 1 through 3 ~~~ 5 The portion of total contributions by each person (other than a governmental unit or publicly supported organization) included on line 1 that exceeds 2% of the amount shown on line 11, column (f) ~~~~~~~~~~~~
617,194. 1691686. 698,504. 650,987. 663,014. 4321385.
539,529. 3781856.
6 Public support. Subtract line 5 from line 4.
Section B. Total Support
Calendar year (or fiscal year beginning in) | 7 Amounts from line 4 ~~~~~~~ 8 Gross income from interest, dividends, payments received on securities loans, rents, royalties and income from similar sources ~ 9 Net income from unrelated business activities, whether or not the business is regularly carried on ~ 10 Other income. Do not include gain or loss from the sale of capital assets (Explain in Part IV.) ~~~~ 11 Total support. Add lines 7 through 10
(a) 2009
(b) 2010
(c) 2011
(d) 2012
(e) 2013
(f) Total
617,194. 1691686. 698,504. 650,987. 663,014. 4321385.
120,884. 115,860. 128,458.
2,789.
1,972.
1,759.
77,406. 136,236. 578,844.
4.
15.
6,539. 4906768.
12 Gross receipts from related activities, etc. (see instructions) ~~~~~~~~~~~~~~~~~~~~~~~ 12 13 First five years. If the Form 990 is for the organization's first, second, third, fourth, or fifth tax year as a section 501(c)(3) organization, check this box and stop here ••••••••••••••••••••••••••••••••••••••••••••• |
Section C. Computation of Public Support Percentage
77.07 % 14 Public support percentage for 2013 (line 6, column (f) divided by line 11, column (f)) ~~~~~~~~~~~~ 14 77.81 % 15 Public support percentage from 2012 Schedule A, Part II, line 14 ~~~~~~~~~~~~~~~~~~~~~ 15 16a 33 1/3% support test - 2013. If the organization did not check the box on line 13, and line 14 is 33 1/3% or more, check this box and stop here. The organization qualifies as a publicly supported organization ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ | X b 33 1/3% support test - 2012. If the organization did not check a box on line 13 or 16a, and line 15 is 33 1/3% or more, check this box and stop here. The organization qualifies as a publicly supported organization ~~~~~~~~~~~~~~~~~~~~~~~~~~~~ | 17a 10% -facts-and-circumstances test - 2013. If the organization did not check a box on line 13, 16a, or 16b, and line 14 is 10% or more, and if the organization meets the "facts-and-circumstances" test, check this box and stop here. Explain in Part IV how the organization meets the "facts-and-circumstances" test. The organization qualifies as a publicly supported organization ~~~~~~~~~~~~~~~ | b 10% -facts-and-circumstances test - 2012. If the organization did not check a box on line 13, 16a, 16b, or 17a, and line 15 is 10% or more, and if the organization meets the "facts-and-circumstances" test, check this box and stop here. Explain in Part IV how the organization meets the "facts-and-circumstances" test. The organization qualifies as a publicly supported organization ~~~~~~~~ | 18 Private foundation. If the organization did not check a box on line 13, 16a, 16b, 17a, or 17b, check this box and see instructions ••• | Schedule A (Form 990 or 990-EZ) 2013
332022 09-25-13
09481029 758275 3064.000
14 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
Schedule A (Form 990 or 990-EZ) 2013
Page 3
Part III Support Schedule for Organizations Described in Section 509(a)(2)
(Complete only if you checked the box on line 9 of Part I or if the organization failed to qualify under Part II. If the organization fails to qualify under the tests listed below, please complete Part II.)
Section A. Public Support Calendar year (or fiscal year beginning in) |
(a) 2009
(b) 2010
(c) 2011
(d) 2012
(e) 2013
(f) Total
(a) 2009
(b) 2010
(c) 2011
(d) 2012
(e) 2013
(f) Total
1 Gifts, grants, contributions, and membership fees received. (Do not include any "unusual grants.") ~~ 2 Gross receipts from admissions, merchandise sold or services performed, or facilities furnished in any activity that is related to the organization's tax-exempt purpose 3 Gross receipts from activities that are not an unrelated trade or business under section 513 ~~~~~ 4 Tax revenues levied for the organization's benefit and either paid to or expended on its behalf ~~~~ 5 The value of services or facilities furnished by a governmental unit to the organization without charge ~ 6 Total. Add lines 1 through 5 ~~~ 7 a Amounts included on lines 1, 2, and 3 received from disqualified persons b Amounts included on lines 2 and 3 received from other than disqualified persons that exceed the greater of $5,000 or 1% of the amount on line 13 for the year ~~~~~~
c Add lines 7a and 7b ~~~~~~~ 8 Public support (Subtract line 7c from line 6.)
Section B. Total Support
Calendar year (or fiscal year beginning in) | 9 Amounts from line 6 ~~~~~~~ 10a Gross income from interest, dividends, payments received on securities loans, rents, royalties and income from similar sources ~ b Unrelated business taxable income (less section 511 taxes) from businesses acquired after June 30, 1975 ~~~~ c Add lines 10a and 10b ~~~~~~ 11 Net income from unrelated business activities not included in line 10b, whether or not the business is regularly carried on ~~~~~~~ 12 Other income. Do not include gain or loss from the sale of capital assets (Explain in Part IV.) ~~~~ 13 Total support. (Add lines 9, 10c, 11, and 12.)
14 First five years. If the Form 990 is for the organization's first, second, third, fourth, or fifth tax year as a section 501(c)(3) organization, check this box and stop here •••••••••••••••••••••••••••••••••••••••••••••••••••• |
Section C. Computation of Public Support Percentage
15 Public support percentage for 2013 (line 8, column (f) divided by line 13, column (f)) ~~~~~~~~~~~~ 16 Public support percentage from 2012 Schedule A, Part III, line 15 ••••••••••••••••••••
Section D. Computation of Investment Income Percentage
15 16
% %
17 Investment income percentage for 2013 (line 10c, column (f) divided by line 13, column (f)) ~~~~~~~~ 17 % 18 Investment income percentage from 2012 Schedule A, Part III, line 17 ~~~~~~~~~~~~~~~~~~ 18 % 19 a 33 1/3% support tests - 2013. If the organization did not check the box on line 14, and line 15 is more than 33 1/3%, and line 17 is not more than 33 1/3%, check this box and stop here. The organization qualifies as a publicly supported organization ~~~~~~~~~~ | b 33 1/3% support tests - 2012. If the organization did not check a box on line 14 or line 19a, and line 16 is more than 33 1/3%, and line 18 is not more than 33 1/3%, check this box and stop here. The organization qualifies as a publicly supported organization~~~~ | 20 Private foundation. If the organization did not check a box on line 14, 19a, or 19b, check this box and see instructions •••••••• | 332023 09-25-13 Schedule A (Form 990 or 990-EZ) 2013
09481029 758275 3064.000
15 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE 13-2735359 Page 4 Schedule A (Form 990 or 990-EZ) 2013 FOUNDATION, INC. Part IV Supplemental Information. Provide the explanations required by Part II, line 10; Part II, line 17a or 17b; and Part III, line 12. Also complete this part for any additional information. (See instructions).
332024 09-25-13
09481029 758275 3064.000
Schedule A (Form 990 or 990-EZ) 2013
16 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
Schedule B
Schedule of Contributors
(Form 990, 990-EZ, or 990-PF)
| Attach to Form 990, Form 990-EZ, or Form 990-PF. | Information about Schedule B (Form 990, 990-EZ, or 990-PF) and its instructions is at www.irs.gov/form990 .
Department of the Treasury Internal Revenue Service
Name of the organization
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC.
OMB No. 1545-0047
2013
Employer identification number
13-2735359
Organization type (check one): Filers of: Form 990 or 990-EZ
Section:
X
501(c)(
3
) (enter number) organization
4947(a)(1) nonexempt charitable trust not treated as a private foundation 527 political organization Form 990-PF
501(c)(3) exempt private foundation 4947(a)(1) nonexempt charitable trust treated as a private foundation 501(c)(3) taxable private foundation
Check if your organization is covered by the General Rule or a Special Rule. Note. Only a section 501(c)(7), (8), or (10) organization can check boxes for both the General Rule and a Special Rule. See instructions. General Rule For an organization filing Form 990, 990-EZ, or 990-PF that received, during the year, $5,000 or more (in money or property) from any one contributor. Complete Parts I and II. Special Rules
X
For a section 501(c)(3) organization filing Form 990 or 990-EZ that met the 33 1/3% support test of the regulations under sections 509(a)(1) and 170(b)(1)(A)(vi) and received from any one contributor, during the year, a contribution of the greater of (1) $5,000 or (2) 2% of the amount on (i) Form 990, Part VIII, line 1h, or (ii) Form 990-EZ, line 1. Complete Parts I and II. For a section 501(c)(7), (8), or (10) organization filing Form 990 or 990-EZ that received from any one contributor, during the year, total contributions of more than $1,000 for use exclusively for religious, charitable, scientific, literary, or educational purposes, or the prevention of cruelty to children or animals. Complete Parts I, II, and III. For a section 501(c)(7), (8), or (10) organization filing Form 990 or 990-EZ that received from any one contributor, during the year, contributions for use exclusively for religious, charitable, etc., purposes, but these contributions did not total to more than $1,000. If this box is checked, enter here the total contributions that were received during the year for an exclusively religious, charitable, etc., purpose. Do not complete any of the parts unless the General Rule applies to this organization because it received nonexclusively religious, charitable, etc., contributions of $5,000 or more during the year ~~~~~~~~~~~~~~~~~ | $
Caution. An organization that is not covered by the General Rule and/or the Special Rules does not file Schedule B (Form 990, 990-EZ, or 990-PF), but it must answer "No" on Part IV, line 2, of its Form 990; or check the box on line H of its Form 990-EZ or on its Form 990-PF, Part I, line 2, to certify that it does not meet the filing requirements of Schedule B (Form 990, 990-EZ, or 990-PF). LHA For Paperwork Reduction Act Notice, see the Instructions for Form 990, 990-EZ, or 990-PF. Schedule B (Form 990, 990-EZ, or 990-PF) (2013)
323451 10-24-13
Page 2
Schedule B (Form 990, 990-EZ, or 990-PF) (2013) Name of organization
Employer identification number
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Part I
Contributors
(see instructions). Use duplicate copies of Part I if additional space is needed.
(a) No.
1
13-2735359
(b) Name, address, and ZIP + 4
(c) Total contributions
INTERNATIONAL MINISTRIES, ABC REV. BEN CHAN, P.O BOX 851
$
15,483.
2
(b) Name, address, and ZIP + 4
THE SCUDDER ASSOCIATION C/O MR. RICHARD WILLIAMSON, 2 TINYWOOD ROAD
(c) Total contributions
$
40,000.
3
(b) Name, address, and ZIP + 4
(c) Total contributions
DR. JANE SRINIVASAN 24 SENECA RD
$
20,000.
4
(b) Name, address, and ZIP + 4
(c) Total contributions
DR. AND MRS. NORMAN THOMS 5420 S.R. 37TH STREET
$
35,000.
5
(b) Name, address, and ZIP + 4
BAYER HEALTHCARE PHARMACEUTICALS C/O GLOBAL MEDICAL AFFAIRS HEMATOLOGY, PO BOX 1000
(c) Total contributions
$
100,000.
6
(b) Name, address, and ZIP + 4
(c) Total contributions
BERTA BINNS 3940 STACY LN
$
SANTA BARBARA, CA 93110-1516 323452 10-24-13
09481029 758275 3064.000
X
(d) Type of contribution Person Payroll Noncash
X
(d) Type of contribution Person Payroll Noncash
X
(d) Type of contribution Person Payroll Noncash
X
(Complete Part II for noncash contributions.)
MONTVALE, NJ 07045-1000 (a) No.
Person Payroll Noncash
(Complete Part II for noncash contributions.)
TECHUMSEH, KS 66542-5161 (a) No.
(d) Type of contribution
(Complete Part II for noncash contributions.)
BLOOMFIELD, CT 06002 (a) No.
X
(Complete Part II for noncash contributions.)
DARIEN, CT 06820-2429 (a) No.
Person Payroll Noncash
(Complete Part II for noncash contributions.)
VALLEY FORGE, PA 19482 (a) No.
(d) Type of contribution
15,000.
(d) Type of contribution Person Payroll Noncash
X
(Complete Part II for noncash contributions.) Schedule B (Form 990, 990-EZ, or 990-PF) (2013)
18 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
Page 2
Schedule B (Form 990, 990-EZ, or 990-PF) (2013) Name of organization
Employer identification number
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Part I
Contributors
(see instructions). Use duplicate copies of Part I if additional space is needed.
(a) No.
7
13-2735359
(b) Name, address, and ZIP + 4
(c) Total contributions
BRISTOL-MYERS SQUIBB COMPANY PO BOX 7907
$
14,156.
8
(b) Name, address, and ZIP + 4
(c) Total contributions
DOROTHY AND VICK WILLIAMS 75 BENTHAVEN PLACE
$
21,513.
9
(b) Name, address, and ZIP + 4
(c) Total contributions
ESTATE OF DR. WILLIAM COXE UNION LIFE INSURANCE, 1876 WAYCROSS RD
$
106,359.
(d) Type of contribution Person Payroll Noncash
X
(d) Type of contribution Person Payroll Noncash
X
(Complete Part II for noncash contributions.)
CINCINNATI, OH 45240 (a) No.
X
(Complete Part II for noncash contributions.)
BOULDER, CO 80305-6255 (a) No.
Person Payroll Noncash
(Complete Part II for noncash contributions.)
PRINCETON, NJ 08543 (a) No.
(d) Type of contribution
(b) Name, address, and ZIP + 4
(c) Total contributions
(d) Type of contribution Person Payroll Noncash
$
(Complete Part II for noncash contributions.) (a) No.
(b) Name, address, and ZIP + 4
(c) Total contributions
(d) Type of contribution Person Payroll Noncash
$
(Complete Part II for noncash contributions.) (a) No.
(b) Name, address, and ZIP + 4
(c) Total contributions
$
(d) Type of contribution Person Payroll Noncash (Complete Part II for noncash contributions.)
323452 10-24-13
09481029 758275 3064.000
Schedule B (Form 990, 990-EZ, or 990-PF) (2013)
19 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
Page 3 Employer identification number
Schedule B (Form 990, 990-EZ, or 990-PF) (2013) Name of organization
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Part II
Noncash Property
(a) No. from Part I
13-2735359
(see instructions). Use duplicate copies of Part II if additional space is needed.
(b) Description of noncash property given
(c) FMV (or estimate) (see instructions)
(d) Date received
(c) FMV (or estimate) (see instructions)
(d) Date received
(c) FMV (or estimate) (see instructions)
(d) Date received
(c) FMV (or estimate) (see instructions)
(d) Date received
(c) FMV (or estimate) (see instructions)
(d) Date received
(c) FMV (or estimate) (see instructions)
(d) Date received
$ (a) No. from Part I
(b) Description of noncash property given
$ (a) No. from Part I
(b) Description of noncash property given
$ (a) No. from Part I
(b) Description of noncash property given
$ (a) No. from Part I
(b) Description of noncash property given
$ (a) No. from Part I
(b) Description of noncash property given
$ 323453 10-24-13
09481029 758275 3064.000
Schedule B (Form 990, 990-EZ, or 990-PF) (2013)
20 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
Page 4 Employer identification number
Schedule B (Form 990, 990-EZ, or 990-PF) (2013) Name of organization
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. 13-2735359 Exclusively religious, charitable, etc., individual contributions to section 501(c)(7), (8), or (10) organizations that total more than $1,000 for the Part III year. Complete columns (a) through (e) and the following line entry. For organizations completing Part III, enter the total of exclusively religious, charitable, etc., contributions of $1,000 or less for the year. (Enter this information once.) | $ Use duplicate copies of Part III if additional space is needed.
(a) No. from Part I
(b) Purpose of gift
(c) Use of gift
(d) Description of how gift is held
(e) Transfer of gift Transferee's name, address, and ZIP + 4
(a) No. from Part I
(b) Purpose of gift
Relationship of transferor to transferee
(c) Use of gift
(d) Description of how gift is held
(e) Transfer of gift Transferee's name, address, and ZIP + 4
(a) No. from Part I
(b) Purpose of gift
Relationship of transferor to transferee
(c) Use of gift
(d) Description of how gift is held
(e) Transfer of gift Transferee's name, address, and ZIP + 4
(a) No. from Part I
(b) Purpose of gift
Relationship of transferor to transferee
(c) Use of gift
(d) Description of how gift is held
(e) Transfer of gift Transferee's name, address, and ZIP + 4
323454 10-24-13
09481029 758275 3064.000
Relationship of transferor to transferee
Schedule B (Form 990, 990-EZ, or 990-PF) (2013)
21 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
SCHEDULE D (Form 990)
OMB No. 1545-0047
Supplemental Financial Statements
2013
| Complete if the organization answered "Yes," to Form 990, Part IV, line 6, 7, 8, 9, 10, 11a, 11b, 11c, 11d, 11e, 11f, 12a, or 12b. Open to Public | Attach to Form 990. Department of the Treasury Inspection Internal Revenue Service | Information about Schedule D (Form 990) and its instructions is at www.irs.gov/form990. VELLORE CHRISTIAN MEDICAL COLLEGE Name of the organization Employer identification number
Part I
FOUNDATION, INC. 13-2735359 Organizations Maintaining Donor Advised Funds or Other Similar Funds or Accounts.Complete if the organization answered "Yes" to Form 990, Part IV, line 6. (a) Donor advised funds
(b) Funds and other accounts
Total number at end of year ~~~~~~~~~~~~~~~ Aggregate contributions to (during year) ~~~~~~~~ Aggregate grants from (during year) ~~~~~~~~~~ Aggregate value at end of year ~~~~~~~~~~~~~ Did the organization inform all donors and donor advisors in writing that the assets held in donor advised funds are the organization's property, subject to the organization's exclusive legal control? ~~~~~~~~~~~~~~~~~~ 6 Did the organization inform all grantees, donors, and donor advisors in writing that grant funds can be used only for charitable purposes and not for the benefit of the donor or donor advisor, or for any other purpose conferring impermissible private benefit? •••••••••••••••••••••••••••••••••••••••••••• Part II Conservation Easements. Complete if the organization answered "Yes" to Form 990, Part IV, line 7. 1 2 3 4 5
Yes
No
Yes
No
1
Purpose(s) of conservation easements held by the organization (check all that apply). Preservation of land for public use (e.g., recreation or education) Preservation of an historically important land area Protection of natural habitat Preservation of a certified historic structure Preservation of open space
2
Complete lines 2a through 2d if the organization held a qualified conservation contribution in the form of a conservation easement on the last day of the tax year. Held at the End of the Tax Year
a b c d 3 4 5 6 7 8 9
Total number of conservation easements ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 2a Total acreage restricted by conservation easements ~~~~~~~~~~~~~~~~~~~~~~~~~~ 2b Number of conservation easements on a certified historic structure included in (a) ~~~~~~~~~~~~ 2c Number of conservation easements included in (c) acquired after 8/17/06, and not on a historic structure listed in the National Register ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 2d Number of conservation easements modified, transferred, released, extinguished, or terminated by the organization during the tax year | Number of states where property subject to conservation easement is located | Does the organization have a written policy regarding the periodic monitoring, inspection, handling of violations, and enforcement of the conservation easements it holds? ~~~~~~~~~~~~~~~~~~~~~~~~~ Yes Staff and volunteer hours devoted to monitoring, inspecting, and enforcing conservation easements during the year | Amount of expenses incurred in monitoring, inspecting, and enforcing conservation easements during the year | $ Does each conservation easement reported on line 2(d) above satisfy the requirements of section 170(h)(4)(B)(i) and section 170(h)(4)(B)(ii)? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Yes In Part XIII, describe how the organization reports conservation easements in its revenue and expense statement, and balance sheet, and include, if applicable, the text of the footnote to the organization's financial statements that describes the organization's accounting for conservation easements.
Part III
No
No
Organizations Maintaining Collections of Art, Historical Treasures, or Other Similar Assets.
Complete if the organization answered "Yes" to Form 990, Part IV, line 8.
1a If the organization elected, as permitted under SFAS 116 (ASC 958), not to report in its revenue statement and balance sheet works of art, historical treasures, or other similar assets held for public exhibition, education, or research in furtherance of public service, provide, in Part XIII, the text of the footnote to its financial statements that describes these items. b If the organization elected, as permitted under SFAS 116 (ASC 958), to report in its revenue statement and balance sheet works of art, historical treasures, or other similar assets held for public exhibition, education, or research in furtherance of public service, provide the following amounts relating to these items: (i) Revenues included in Form 990, Part VIII, line 1 ~~~~~~~~~~~~~~~~~~~~~~~~~~~~ | $ (ii) Assets included in Form 990, Part X ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ | $ 2 If the organization received or held works of art, historical treasures, or other similar assets for financial gain, provide the following amounts required to be reported under SFAS 116 (ASC 958) relating to these items: a Revenues included in Form 990, Part VIII, line 1 ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ | $ b Assets included in Form 990, Part X ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ | $ LHA For Paperwork Reduction Act Notice, see the Instructions for Form 990. 332051 09-25-13
09481029 758275 3064.000
Schedule D (Form 990) 2013
22 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. 13-2735359 Page 2 Schedule D (Form 990) 2013 Part III Organizations Maintaining Collections of Art, Historical Treasures, or Other Similar Assets(continued) Using the organization's acquisition, accession, and other records, check any of the following that are a significant use of its collection items (check all that apply): a Public exhibition d Loan or exchange programs b Scholarly research e Other c Preservation for future generations 4 Provide a description of the organization's collections and explain how they further the organization's exempt purpose in Part XIII. 5 During the year, did the organization solicit or receive donations of art, historical treasures, or other similar assets to be sold to raise funds rather than to be maintained as part of the organization's collection? •••••••••••• Yes No Part IV Escrow and Custodial Arrangements. Complete if the organization answered "Yes" to Form 990, Part IV, line 9, or reported an amount on Form 990, Part X, line 21. 3
1a Is the organization an agent, trustee, custodian or other intermediary for contributions or other assets not included on Form 990, Part X? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ b If "Yes," explain the arrangement in Part XIII and complete the following table:
Yes
Amount Beginning balance ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 1c Additions during the year ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 1d Distributions during the year ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 1e Ending balance ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 1f Did the organization include an amount on Form 990, Part X, line 21? ~~~~~~~~~~~~~~~~~~~~~~~~~ Yes If "Yes," explain the arrangement in Part XIII. Check here if the explanation has been provided in Part XIII ••••••••••••• Part V Endowment Funds. Complete if the organization answered "Yes" to Form 990, Part IV, line 10. c d e f 2a b
1a b c d e f g 2 a b c 3a
b 4
No
No
(a) Current year (b) Prior year (c) Two years back (d) Three years back (e) Four years back 5,110,369. 4,996,307. 4,893,332. 4,203,539. 4,015,902. Beginning of year balance ~~~~~~~ 4,506. -1,000. 1,000. 29,404. 31,719. Contributions ~~~~~~~~~~~~~~ 756,885. 115,062. 101,975. 660,389. 155,918. Net investment earnings, gains, and losses Grants or scholarships ~~~~~~~~~ Other expenditures for facilities and programs ~~~~~~~~~~~~~ Administrative expenses ~~~~~~~~ 5,871,760. 5,110,369. 4,996,307. 4,893,332. 4,203,539. End of year balance ~~~~~~~~~~ Provide the estimated percentage of the current year end balance (line 1g, column (a)) held as: 40.97 Board designated or quasi-endowment | % 33.36 Permanent endowment | % 25.67 Temporarily restricted endowment | % The percentages in lines 2a, 2b, and 2c should equal 100%. Are there endowment funds not in the possession of the organization that are held and administered for the organization by: Yes No X (i) unrelated organizations ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 3a(i) X (ii) related organizations ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 3a(ii) If "Yes" to 3a(ii), are the related organizations listed as required on Schedule R? ~~~~~~~~~~~~~~~~~~~~~~ 3b Describe in Part XIII the intended uses of the organization's endowment funds.
Part VI
Land, Buildings, and Equipment. Complete if the organization answered "Yes" to Form 990, Part IV, line 11a. See Form 990, Part X, line 10. Description of property
(a) Cost or other basis (investment)
(b) Cost or other basis (other)
(c) Accumulated depreciation
(d) Book value
1a Land ~~~~~~~~~~~~~~~~~~~~ b Buildings ~~~~~~~~~~~~~~~~~~ c Leasehold improvements ~~~~~~~~~~ 98,544. 46,342. 52,202. d Equipment ~~~~~~~~~~~~~~~~~ e Other •••••••••••••••••••• 52,202. Total. Add lines 1a through 1e. (Column (d) must equal Form 990, Part X, column (B), line 10(c).) •••••••••••• | Schedule D (Form 990) 2013
332052 09-25-13
09481029 758275 3064.000
23 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Schedule D (Form 990) 2013 Part VII Investments - Other Securities.
13-2735359
Page 3
Complete if the organization answered "Yes" to Form 990, Part IV, line 11b. See Form 990, Part X, line 12. (a) Description of security or category (including name of security) (b) Book value (c) Method of valuation: Cost or end-of-year market value (1) Financial derivatives ~~~~~~~~~~~~~~~ (2) Closely-held equity interests ~~~~~~~~~~~ (3) Other (A) (B) (C) (D) (E) (F) (G) (H) Total. (Col. (b) must equal Form 990, Part X, col. (B) line 12.) |
Part VIII Investments - Program Related. Complete if the organization answered "Yes" to Form 990, Part IV, line 11c. See Form 990, Part X, line 13. (a) Description of investment (b) Book value (c) Method of valuation: Cost or end-of-year market value (1) (2) (3) (4) (5) (6) (7) (8) (9) Total. (Col. (b) must equal Form 990, Part X, col. (B) line 13.) |
Part IX
Other Assets. Complete if the organization answered "Yes" to Form 990, Part IV, line 11d. See Form 990, Part X, line 15. (a) Description
(b) Book value
(1) (2) (3) (4) (5) (6) (7) (8) (9) Total. (Column (b) must equal Form 990, Part X, col. (B) line 15.) •••••••••••••••••••••••••••• |
Part X
1.
Other Liabilities.
Complete if the organization answered "Yes" to Form 990, Part IV, line 11e or 11f. See Form 990, Part X, line 25. (a) Description of liability (b) Book value
(1) Federal income taxes (2) (3) (4) (5) (6) (7) (8) (9) Total. (Column (b) must equal Form 990, Part X, col. (B) line 25.) ••••• | 2. Liability for uncertain tax positions. In Part XIII, provide the text of the footnote to the organization's financial statements that reports the organization's liability for uncertain tax positions under FIN 48 (ASC 740). Check here if the text of the footnote has been provided in Part XIII X Schedule D (Form 990) 2013 332053 09-25-13
09481029 758275 3064.000
24 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. 13-2735359 Schedule D (Form 990) 2013 Part XI Reconciliation of Revenue per Audited Financial Statements With Revenue per Return. Complete if the organization answered "Yes" to Form 990, Part IV, line 12a. 1 2 a b c d e 3 4 a b c 5
Total revenue, gains, and other support per audited financial statements ~~~~~~~~~~~~~~~~~~~ 1 Amounts included on line 1 but not on Form 990, Part VIII, line 12: 580,259. Net unrealized gains on investments ~~~~~~~~~~~~~~~~~~~~~~ 2a Donated services and use of facilities ~~~~~~~~~~~~~~~~~~~~~~ 2b Recoveries of prior year grants ~~~~~~~~~~~~~~~~~~~~~~~~~ 2c Other (Describe in Part XIII.) ~~~~~~~~~~~~~~~~~~~~~~~~~~ 2d Add lines 2a through 2d ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 2e Subtract line 2e from line 1 ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 3 Amounts included on Form 990, Part VIII, line 12, but not on line 1: 26,328. Investment expenses not included on Form 990, Part VIII, line 7b ~~~~~~~~ 4a Other (Describe in Part XIII.) ~~~~~~~~~~~~~~~~~~~~~~~~~~ 4b Add lines 4a and 4b ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 4c Total revenue. Add lines 3 and 4c. (This must equal Form 990, Part I, line 12.) ••••••••••••••••• 5
1 2 a b c d e 3 4 a b c 5
Total expenses and losses per audited financial statements ~~~~~~~~~~~~~~~~~~~~~~~~~~ 1 Amounts included on line 1 but not on Form 990, Part IX, line 25: Donated services and use of facilities ~~~~~~~~~~~~~~~~~~~~~~ 2a Prior year adjustments ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 2b Other losses ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 2c Other (Describe in Part XIII.) ~~~~~~~~~~~~~~~~~~~~~~~~~~ 2d Add lines 2a through 2d ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 2e Subtract line 2e from line 1 ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 3 Amounts included on Form 990, Part IX, line 25, but not on line 1: 26,328. Investment expenses not included on Form 990, Part VIII, line 7b ~~~~~~~~ 4a Other (Describe in Part XIII.) ~~~~~~~~~~~~~~~~~~~~~~~~~~ 4b Add lines 4a and 4b ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 4c Total expenses. Add lines 3 and 4c. (This must equal Form 990, Part I, line 18.) •••••••••••••••• 5
Page 4
1,634,422.
580,259. 1,054,163.
26,328. 1,080,491. Part XII Reconciliation of Expenses per Audited Financial Statements With Expenses per Return. Complete if the organization answered "Yes" to Form 990, Part IV, line 12a.
914,033.
0. 914,033.
26,328. 940,361.
Part XIII Supplemental Information.
Provide the descriptions required for Part II, lines 3, 5, and 9; Part III, lines 1a and 4; Part IV, lines 1b and 2b; Part V, line 4; Part X, line 2; Part XI, lines 2d and 4b; and Part XII, lines 2d and 4b. Also complete this part to provide any additional information.
PART X, LINE 2: EXPLANATION: MANAGEMENT HAS REVIEWED THE TAX POSITIONS FOR EACH OF THE OPEN TAX YEARS (2010-2012) OR EXPECTED TO BE TAKEN IN THE FOUNDATION'S 2013 TAX RETURN AND HAS CONCLUDED THAT THERE ARE NO SIGNIFICANT UNCERTAIN TAX POSITIONS THAT WOULD REQUIRE RECOGNITION IN THE FINANCIAL STATEMENTS.
332054 09-25-13
09481029 758275 3064.000
Schedule D (Form 990) 2013
25 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
SCHEDULE F (Form 990)
Department of the Treasury Internal Revenue Service
Statement of Activities Outside the United States
| Complete if the organization answered "Yes" on Form 990, Part IV, line 14b, 15, or 16. | Attach to Form 990. | See separate instructions. | Information about Schedule F (Form 990) and its instructions is at www.irs.gov/form990.
Name of the organization
OMB No. 1545-0047
2013
Open to Public Inspection
Employer identification number
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. 13-2735359 Part I General Information on Activities Outside the United States. Complete if the organization answered "Yes" on 1
2 3
Form 990, Part IV, line 14b. For grantmakers. Does the organization maintain records to substantiate the amount of its grants and other assistance, the grantees' eligibility for the grants or assistance, and the selection criteria used to award the grants or assistance? ~~
Yes
X
No
For grantmakers. Describe in Part V the organization's procedures for monitoring the use of its grants and other assistance outside the United States. Activities per Region. (The following Part I, line 3 table can be duplicated if additional space is needed.) (a) Region (b) Number of (c) Number of (d) Activities conducted in region (e) If activity listed in (d) (f) Total employees, expenditures offices (by type) (e.g., fundraising, program is a program service, agents, and for and in the region services, investments, grants to describe specific type independent investments contractors recipients located in the region) of service(s) in region in region in region
SOUTH ASIA
0
0 GRANTS TO RECIPIENTS.
0 0 3 a Sub-total ~~~~~~ b Total from continuation 0 0 sheets to Part I ~~~ c Totals (add lines 3a 0 0 and 3b) •••••• LHA For Paperwork Reduction Act Notice, see the Instructions for Form 990. 332071 10-03-13
09481029 758275 3064.000
GRANTS FOR BENEFIT OF VELLORE CHRISTIAN MEDICAL COLLEGE.
304,455.
304,455. 0. 304,455. Schedule F (Form 990) 2013
26 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC.
13-2735359 Schedule F (Form 990) 2013 Part II Grants and Other Assistance to Organizations or Entities Outside the United States. Complete if the organization answered "Yes" on Form 990, Part IV, line 15, for any recipient who received more than $5,000. Part II can be duplicated if additional space is needed. 1 (a) Name of organization
(b) IRS code section and EIN (if applicable)
(c) Region
SOUTH ASIA
2 3
(g) Amount of (e) Amount (f) Manner of non-cash of cash grant cash disbursement assistance
(d) Purpose of grant
TO SUPPORT VELLORE CHRISTIAN MEDICAL COLLEGE IN INDIA.
211,418.CHECK, WIRE
(h) Description of non-cash assistance
PURCHASED SUPPLIES AND 93,037.MATERIALS.
Enter total number of recipient organizations listed above that are recognized as charities by the foreign country, recognized as tax-exempt by the IRS, or for which the grantee or counsel has provided a section 501(c)(3) equivalency letter ~~~~~~~~~~~~~~~~~~~~~~~ | Enter total number of other organizations or entities ••••••••••••••••••••••••••••••••••••••••••••• |
Page 2
(i) Method of valuation (book, FMV, appraisal, other)
RECEIPTS & COSTS
1 0 Schedule F (Form 990) 2013
332072 10-03-13
27
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC.
13-2735359 Schedule F (Form 990) 2013 Part III Grants and Other Assistance to Individuals Outside the United States. Complete if the organization answered "Yes" on Form 990, Part IV, line 16. Part III can be duplicated if additional space is needed. (c) Number of (d) Amount of (e) Manner of (f) Amount of (g) Description of (a) Type of grant or assistance (b) Region recipients cash grant cash disbursement non-cash non-cash assistance assistance
Page 3
(h) Method of valuation (book, FMV, appraisal, other)
Schedule F (Form 990) 2013 332073 10-03-13
28
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Schedule F (Form 990) 2013 Part IV Foreign Forms 1
2
3
4
5
6
13-2735359
Page 4
Was the organization a U.S. transferor of property to a foreign corporation during the tax year? If "Yes," the organization may be required to file Form 926, Return by a U.S. Transferor of Property to a Foreign Corporation (see Instructions for Form 926) ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~
Yes
X
No
Did the organization have an interest in a foreign trust during the tax year? If "Yes," the organization may be required to file Form 3520, Annual Return to Report Transactions with Foreign Trusts and Receipt of Certain Foreign Gifts, and/or Form 3520-A, Annual Information Return of Foreign Trust With a U.S. Owner (see Instructions for Forms 3520 and 3520-A) [[[[[[[[[[[[[[[[[[[[[[[[[[[[[[[[[[
Yes
X
No
Did the organization have an ownership interest in a foreign corporation during the tax year? If "Yes," the organization may be required to file Form 5471, Information Return of U.S. Persons With Respect To Certain Foreign Corporations. (see Instructions for Form 5471) ~~~~~~~~~~~~~~~~~~~~~~~~~~~
Yes
X
No
Was the organization a direct or indirect shareholder of a passive foreign investment company or a qualified electing fund during the tax year? If "Yes," the organization may be required to file Form 8621, Information Return by a Shareholder of a Passive Foreign Investment Company or Qualified Electing Fund. (see Instructions for Form 8621) ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~
Yes
X
No
Did the organization have an ownership interest in a foreign partnership during the tax year? If "Yes," the organization may be required to file Form 8865, Return of U.S. Persons With Respect To Certain Foreign Partnerships. (see Instructions for Form 8865) ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~
Yes
X
No
Did the organization have any operations in or related to any boycotting countries during the tax year? If "Yes," the organization may be required to file Form 5713, International Boycott Report. (see Instructions for Form 5713) ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~
Yes
X
No
Schedule F (Form 990) 2013
332074 10-03-13
09481029 758275 3064.000
29 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Schedule F (Form 990) 2013 Part V Supplemental Information
13-2735359
Page 5
Provide the information required by Part I, line 2 (monitoring of funds); Part I, line 3, column (f) (accounting method; amounts of investments vs. expenditures per region); Part II, line 1 (accounting method); Part III (accounting method); and Part III, column (c) (estimated number of recipients), as applicable. Also complete this part to provide any additional information.
PART I, LINE 2: EXPLANATION: ALL GRANT FUNDS HAVE A DESIGNATED USE THAT IS SPECIFIED IN THE LETTER OF DISTRIBUTION. THE ORGANIZATION RECEIVES AN ACKNOWLEDGEMENT OF THE RECEIPT OF THE FUNDS ALONG WITH ASSURANCE THAT THE MONEY WILL BE USED IN THAT MANNER. SINCE THE ORGANIZATION PROVIDES FUNDING TO ONLY ONE ORGANIZATION, THE CHRISTIAN MEDICAL COLLEGE (CMC) LOCATED IN VELLORE, INDIA, THE ORGANIZATION AND ITS DONORS FREQUENTLY HAVE CONTACT WITH THE DEPARTMENT RECIPIENTS OF FUNDING. FURTHERMORE, MANY OF THE GRANT PROGRAMS SUCH AS USAID'S ASHA PROGRAM HAVE STRINGENT REPORTING REQUIREMENTS INCLUDING SUBMISSION OF INDIVIDUAL RECEIPTS. FOR SCHOLARSHIP RECIPIENTS, THE ORGANIZATION RECEIVES NOTICE AND A BRIEF BIOGRAPHY FROM CMC OF THE INDIVIDUAL STUDENT WHO IS THE BENEFICIARY OF THE SCHOLARSHIP THAT IS THEN PROVIDED TO THE INDIVIDUAL DONOR. CMC STAFF WHO RECEIVE CONTINUING EDUCATION FUNDING FROM THE ORGANIZATION FOR STUDY ABROAD PROVIDE THE ORGANIZATION WITH A REPORT OF THE BENEFITS RECEIVED FROM THEIR INDIVIDUAL STUDY PROGRAM.
332075 10-03-13
09481029 758275 3064.000
Schedule F (Form 990) 2013
30 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
SCHEDULE G (Form 990 or 990-EZ)
Supplemental Information Regarding Fundraising or Gaming Activities
OMB No. 1545-0047
2013
Complete if the organization answered "Yes" to Form 990, Part IV, lines 17, 18, or 19, or if the organization entered more than $15,000 on Form 990-EZ, line 6a. Department of the Treasury Open To Public | Attach to Form 990 or Form 990-EZ. Internal Revenue Service Inspection | Information about Schedule G (Form 990 or 990-EZ) and its instructions is at www.irs.gov/form 990. Name of the organization VELLORE CHRISTIAN MEDICAL COLLEGE Employer identification number
FOUNDATION, INC.
Part I
13-2735359
Fundraising Activities. Complete if the organization answered "Yes" to Form 990, Part IV, line 17. Form 990-EZ filers are not required to complete this part.
1 Indicate whether the organization raised funds through any of the following activities. Check all that apply. a X Mail solicitations e X Solicitation of non-government grants b Internet and email solicitations f X Solicitation of government grants c Phone solicitations g Special fundraising events d X In-person solicitations 2 a Did the organization have a written or oral agreement with any individual (including officers, directors, trustees or X Yes key employees listed in Form 990, Part VII) or entity in connection with professional fundraising services? b If "Yes," list the ten highest paid individuals or entities (fundraisers) pursuant to agreements under which the fundraiser is to be compensated at least $5,000 by the organization. (i) Name and address of individual or entity (fundraiser)
COMMUNITY COUNSELING SERVICE CO, LLC - 461 5TH AVENUE, 3RD
(ii) Activity
TURNOVER PLANNING FOR INTRODUCTION OF NEW
(iii) Did fundraiser have custody or control of contributions? Yes
(v) Amount paid (iv) Gross receipts to (or retained by) fundraiser from activity listed in col. (i)
No
X
50,000.
No
(vi) Amount paid to (or retained by) organization
38,000.
50,000. 38,000. Total •••••••••••••••••••••••••••••••••••••• | 3 List all states in which the organization is registered or licensed to solicit contributions or has been notified it is exempt from registration or licensing.
12,000.
12,000.
NY
LHA For Paperwork Reduction Act Notice, see the Instructions for Form 990 or 990-EZ.
SEE PART IV FOR CONTINUATIONS
332081 09-12-13
09481029 758275 3064.000
Schedule G (Form 990 or 990-EZ) 2013
31 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
13-2735359 Page 2 Fundraising Events. Complete if the organization answered "Yes" to Form 990, Part IV, line 18, or reported more than $15,000
Schedule G (Form 990 or 990-EZ) 2013
Direct Expenses
Revenue
Part II
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC.
of fundraising event contributions and gross income on Form 990-EZ, lines 1 and 6b. List events with gross receipts greater than $5,000. (a) Event #1 (b) Event #2 (c) Other events (d) Total events (add col. (a) through col. (c)) (event type) (event type) (total number)
1
Gross receipts ~~~~~~~~~~~~~~
2
Less: Contributions ~~~~~~~~~~~
3
Gross income (line 1 minus line 2) ••••
4
Cash prizes ~~~~~~~~~~~~~~~
5
Noncash prizes ~~~~~~~~~~~~~
6
Rent/facility costs ~~~~~~~~~~~~
7
Food and beverages
8 9 10 11
Part
~~~~~~~~~~
Entertainment ~~~~~~~~~~~~~~ Other direct expenses ~~~~~~~~~~ Direct expense summary. Add lines 4 through 9 in column (d) ~~~~~~~~~~~~~~~~~~~~~~~~ | Net income summary. Subtract line 10 from line 3, column (d) •••••••••••••••••••••••• | III Gaming. Complete if the organization answered "Yes" to Form 990, Part IV, line 19, or reported more than
Direct Expenses
Revenue
$15,000 on Form 990-EZ, line 6a. (b) Pull tabs/instant bingo/progressive bingo
(a) Bingo
(d) Total gaming (add col. (a) through col. (c))
(c) Other gaming
1
Gross revenue ••••••••••••••
2
Cash prizes ~~~~~~~~~~~~~~~
3
Noncash prizes ~~~~~~~~~~~~~
4
Rent/facility costs ~~~~~~~~~~~~
5
Other direct expenses ••••••••••
6
Volunteer labor ~~~~~~~~~~~~~
7
Direct expense summary. Add lines 2 through 5 in column (d) ~~~~~~~~~~~~~~~~~~~~~~~~ |
8
Net gaming income summary. Subtract line 7 from line 1, column (d) ••••••••••••••••••••• |
Yes No
%
Yes No
%
Yes No
%
9 Enter the state(s) in which the organization operates gaming activities: a Is the organization licensed to operate gaming activities in each of these states? ~~~~~~~~~~~~~~~~~~~~ b If "No," explain:
10 a Were any of the organization's gaming licenses revoked, suspended or terminated during the tax year? ~~~~~~~~~ b If "Yes," explain:
332082 09-12-13
09481029 758275 3064.000
Yes
No
Yes
No
Schedule G (Form 990 or 990-EZ) 2013
32 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC.
13-2735359 Page 3 Schedule G (Form 990 or 990-EZ) 2013 11 Does the organization operate gaming activities with nonmembers?~~~~~~~~~~~~~~~~~~~~~~~~~~~ Yes No 12 Is the organization a grantor, beneficiary or trustee of a trust or a member of a partnership or other entity formed to administer charitable gaming? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ Yes No 13 Indicate the percentage of gaming activity operated in: a The organization's facility ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 13a % b An outside facility ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 13b % 14 Enter the name and address of the person who prepares the organization's gaming/special events books and records: Name | Address | 15 a Does the organization have a contract with a third party from whom the organization receives gaming revenue? ~~~~~~ b If "Yes," enter the amount of gaming revenue received by the organization | $ of gaming revenue retained by the third party | $ . c If "Yes," enter name and address of the third party:
Yes
No
and the amount
Name | Address | 16 Gaming manager information: Name | Gaming manager compensation | $ Description of services provided |
Director/officer
Employee
Independent contractor
17 Mandatory distributions: a Is the organization required under state law to make charitable distributions from the gaming proceeds to Yes No retain the state gaming license? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ b Enter the amount of distributions required under state law to be distributed to other exempt organizations or spent in the organization's own exempt activities during the tax year | $ Part IV Supplemental Information. Provide the explanations required by Part I, line 2b, columns (iii) and (v), and Part III, lines 9, 9b, 10b, 15b, 15c, 16, and 17b, as applicable. Also complete this part to provide any additional information (see instructions).
SCHEDULE G, PART I, LINE 2B, LIST OF TEN HIGHEST PAID FUNDRAISERS:
(I) NAME OF FUNDRAISER: COMMUNITY COUNSELING SERVICE CO, LLC (I) ADDRESS OF FUNDRAISER: 461 5TH AVENUE, 3RD FLOOR, NEW YORK, NY
10017
(II) ACTIVITY: TURNOVER PLANNING FOR INTRODUCTION OF NEW PRESIDENT.
332083 09-12-13
09481029 758275 3064.000
Schedule G (Form 990 or 990-EZ) 2013
33 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC. Schedule G (Form 990 or 990-EZ) Part IV Supplemental Information (continued)
332084 05-01-13
09481029 758275 3064.000
13-2735359
Page 4
Schedule G (Form 990 or 990-EZ)
34 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
SCHEDULE J (Form 990) Department of the Treasury Internal Revenue Service
Name of the organization
Part I
Compensation Information
OMB No. 1545-0047
2013
For certain Officers, Directors, Trustees, Key Employees, and Highest Compensated Employees | Complete if the organization answered "Yes" on Form 990, Part IV, line 23. Open to Public | Attach to Form 990. | See separate instructions. Inspection | Information about Schedule J (Form 990) and its instructions is at www.irs.gov/form990. VELLORE CHRISTIAN MEDICAL COLLEGE Employer identification number
FOUNDATION, INC. Questions Regarding Compensation
13-2735359
Yes
No
1a Check the appropriate box(es) if the organization provided any of the following to or for a person listed in Form 990, Part VII, Section A, line 1a. Complete Part III to provide any relevant information regarding these items. First-class or charter travel Housing allowance or residence for personal use Travel for companions Payments for business use of personal residence Tax indemnification and gross-up payments Health or social club dues or initiation fees Discretionary spending account Personal services (e.g., maid, chauffeur, chef) b If any of the boxes on line 1a are checked, did the organization follow a written policy regarding payment or reimbursement or provision of all of the expenses described above? If "No," complete Part III to explain ~~~~~~~~~~~ 2 Did the organization require substantiation prior to reimbursing or allowing expenses incurred by all directors, trustees, and officers, including the CEO/Executive Director, regarding the items checked in line 1a? ~~~~~~~~~~~~ 3
1b 2
Indicate which, if any, of the following the filing organization used to establish the compensation of the organization's CEO/Executive Director. Check all that apply. Do not check any boxes for methods used by a related organization to establish compensation of the CEO/Executive Director, but explain in Part III. X Compensation committee Written employment contract Independent compensation consultant Compensation survey or study X Approval by the board or compensation committee Form 990 of other organizations
During the year, did any person listed in Form 990, Part VII, Section A, line 1a, with respect to the filing organization or a related organization: a Receive a severance payment or change-of-control payment? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ b Participate in, or receive payment from, a supplemental nonqualified retirement plan? ~~~~~~~~~~~~~~~~~~~~ c Participate in, or receive payment from, an equity-based compensation arrangement?~~~~~~~~~~~~~~~~~~~~ If "Yes" to any of lines 4a-c, list the persons and provide the applicable amounts for each item in Part III.
4
4a 4b 4c
X X X
Only section 501(c)(3) and 501(c)(4) organizations must complete lines 5-9. For persons listed in Form 990, Part VII, Section A, line 1a, did the organization pay or accrue any compensation contingent on the revenues of: X 5a a The organization? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ X 5b b Any related organization? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ If "Yes" to line 5a or 5b, describe in Part III. 6 For persons listed in Form 990, Part VII, Section A, line 1a, did the organization pay or accrue any compensation contingent on the net earnings of: X 6a a The organization? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ X 6b b Any related organization? ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ If "Yes" to line 6a or 6b, describe in Part III. 7 For persons listed in Form 990, Part VII, Section A, line 1a, did the organization provide any non-fixed payments X 7 not described in lines 5 and 6? If "Yes," describe in Part III ~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~ 8 Were any amounts reported in Form 990, Part VII, paid or accrued pursuant to a contract that was subject to the X 8 initial contract exception described in Regulations section 53.4958-4(a)(3)? If "Yes," describe in Part III ~~~~~~~~~~~ 9 If "Yes" to line 8, did the organization also follow the rebuttable presumption procedure described in 9 Regulations section 53.4958-6(c)? ••••••••••••••••••••••••••••••••••••••••••••• LHA For Paperwork Reduction Act Notice, see the Instructions for Form 990. Schedule J (Form 990) 2013 5
332111 09-13-13
09481029 758275 3064.000
35 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC.
13-2735359 Schedule J (Form 990) 2013 Part II Officers, Directors, Trustees, Key Employees, and Highest Compensated Employees. Use duplicate copies if additional space is needed.
Page 2
For each individual whose compensation must be reported in Schedule J, report compensation from the organization on row (i) and from related organizations, described in the instructions, on row (ii). Do not list any individuals that are not listed on Form 990, Part VII. Note. The sum of columns (B)(i)-(iii) for each listed individual must equal the total amount of Form 990, Part VII, Section A, line 1a, applicable column (D) and (E) amounts for that individual. (B) Breakdown of W-2 and/or 1099-MISC compensation (i) Base compensation
(A) Name and Title
(1) KATHERINE GUENTHER PRESIDENT
332112 09-13-13
(i) (ii) (i) (ii) (i) (ii) (i) (ii) (i) (ii) (i) (ii) (i) (ii) (i) (ii) (i) (ii) (i) (ii) (i) (ii) (i) (ii) (i) (ii) (i) (ii) (i) (ii) (i) (ii)
150,000. 0.
(ii) Bonus & incentive compensation
(iii) Other reportable compensation
0. 0.
0. 0.
36
(C) Retirement and other deferred compensation
21,000. 0.
(D) Nontaxable benefits
26,247. 0.
(E) Total of columns (F) Compensation (B)(i)-(D) reported as deferred in prior Form 990
197,247. 0.
0. 0.
Schedule J (Form 990) 2013
Schedule J (Form 990) 2013 Part III Supplemental Information
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC.
13-2735359
Page 3
Provide the information, explanation, or descriptions required for Part I, lines 1a, 1b, 3, 4a, 4b, 4c, 5a, 5b, 6a, 6b, 7, and 8, and for Part II. Also complete this part for any additional information.
Schedule J (Form 990) 2013 332113 09-13-13
37
SCHEDULE O (Form 990 or 990-EZ)
Supplemental Information to Form 990 or 990-EZ Complete to provide information for responses to specific questions on
OMB No. 1545-0047
2013
Form 990 or 990-EZ or to provide any additional information. Open to Public | Attach to Form 990 or 990-EZ. Department of the Treasury Internal Revenue Service Inspection | Information about Schedule O (Form 990 or 990-EZ) and its instructions is at www.irs.gov/form990. VELLORE CHRISTIAN MEDICAL COLLEGE Name of the organization Employer identification number
FOUNDATION, INC.
13-2735359
FORM 990, PART I, LINE 1, DESCRIPTION OF ORGANIZATION MISSION: PROGRAMS OF VELLORE CHRISTIAN MEDICAL COLLEGE AND HOSPITAL IN INDIA.
FORM 990, PART III, LINE 1, DESCRIPTION OF ORGANIZATION MISSION:
WE DO THIS BY - HONORING IDA SCUDDER - THE PERSON AND HER WORK. - ENCOURAGING AND SUPPORTING RESEARCH ACTIVITY OF THE HIGHEST QUALITY DRIVEN BY HONESTY AND HIGH ETHICAL STANDARDS, DIRECTIONAL FOCUS AND TRANSLATIONAL IMPACT. - PROMOTING THE PROFESSIONAL DEVELOPMENT OF CMC WITH A FOCUS ON THE QUALITY, DELIVERY AND SAFETY OF HEALTH CARE.
FORM 990, PART VI, SECTION A, LINE 4: EXPLANATION: THERE WERE CHANGES MADE TO ARTICLE III SECTION 4 AND ARTICLE VII SECTION 2B OF THE BYLAWS. THE PRESENCE OF 20% OF VOTING MEMBERS OF THE CORPORATION, OR 20 MEMBERS OF SAME, WHICHEVER IS LESS, SHALL BE NECESSARY TO CONSTITUTE A QUORUM FOR THE TRANSACTION OF BUSINESS. THE PHILANTHROPIC ACTION COMMITTEE SHALL MAINTAIN THE CHARTER AND STRUCTURE FOR THE ANNUAL "DR. IDA S SCUDDER HUMANITARIAN ORATION & AWARD", AND MANAGE AND EXECUTE THE ORATION AT CMC, VELLORE THROUGH THE ORATION COMMITTEE.
FORM 990, PART VI, SECTION A, LINE 6: EXPLANATION: THE CORPORATION HAS MEMBERS WHO ELECT THE MEMBERS OF THE GOVERNING BODY.
LHA For Paperwork Reduction Act Notice, see the Instructions for Form 990 or 990-EZ. 332211 09-04-13
09481029 758275 3064.000
Schedule O (Form 990 or 990-EZ) (2013)
38 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
Schedule O (Form 990 or 990-EZ) (2013) Name of the organization VELLORE
CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC.
Page 2 Employer identification number
13-2735359
FORM 990, PART VI, SECTION A, LINE 7A: EXPLANATION: THE MEMBERS ARE THE ONLY ONES WHO CAN ELECT BOARD MEMBERS. THE BOARD ONCE BEEN APPOINTED BY THE CORPORATION THEN ELECTS LEADERSHIP.
FORM 990, PART VI, SECTION A, LINE 7B: EXPLANATION: THE BOARD OF DIRECTORS CANNOT INDEPENDENTLY AMEND THE BY-LAWS WITHOUT APPROVAL OF THE CORPORATION.
FORM 990, PART VI, SECTION B, LINE 11: EXPLANATION: THE FORM 990 IS PREPARED BASED ON INFORMATION IN THE AUDITED FINANCIAL STATEMENTS. THE AUDITED FINANCIAL STATEMENTS ARE REVIEWED BY THE FINANCE COMMITTEE OF THE BOARD OF DIRECTORS AND IS THEN PRESENTED TO THE FULL BOARD OF DIRECTORS AT THE ANNUAL FALL MEETING PRIOR TO FILING WITH THE IRS.
FORM 990, PART VI, SECTION B, LINE 12C: EXPLANATION: THE ORGANIZATION ENSURES THAT ALL EMPLOYEES AND BOARD MEMBERS ARE AWARE OF THE CONFLICT OF INTEREST POLICY AND THE CONSEQUENCES OF VIOLATING IT.
FORM 990, PART VI, SECTION B, LINE 15A: EXPLANATION: THE SALARY FOR THE PRESIDENT IS REVIEWED ANNUALLY BY THE PERSONNEL COMMITTEE OF THE BOARD OF DIRECTORS. RECOMMENDATIONS BY THE PERSONNEL COMMITTEE ARE THEN PRESENTED EITHER TO THE FULL BOARD OF DIRECTORS OR THE EXECUTIVE COMMITTEE OF THE BOARD OF DIRECTORS FOR AUTHORIZATION BY MOTION AND VOTE. THE BOARD OF DIRECTORS TYPICALLY MEETS EIGHT TIMES A YEAR; THE EXECUTIVE COMMITTEE IS AUTHORIZED TO ACT ON BEHALF OF THE BOARD OF DIRECTORS. MINUTES OF MEETINGS OF THE EXECUTIVE COMMITTEE 332212 09-04-13
09481029 758275 3064.000
Schedule O (Form 990 or 990-EZ) (2013)
39 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
Schedule O (Form 990 or 990-EZ) (2013) Name of the organization VELLORE
CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC.
Page 2 Employer identification number
13-2735359
ARE FORWARDED TO THE FULL MEMBERSHIP OF THE BOARD OF DIRECTORS.
FORM 990, PART VI, SECTION C, LINE 19: EXPLANATION: THE ORGANIZATION'S GOVERNING DOCUMENTS AND AUDITED FINANCIAL STATEMENTS ARE MADE AVAILABLE UPON REQUEST. A FINANCIAL REPORT, BASED ON THE AUDITED FINANCIAL STATEMENTS, IS INCLUDED IN THE ANNUAL REPORT WHICH IS AVAILABLE ON THE ORGANIZATION'S WEBSITE.
FORM 990, PART XI, LINE 9, CHANGES IN NET ASSETS: UNREALIZED LOSS ON REMAINDER TRUSTS
332212 09-04-13
09481029 758275 3064.000
889.
Schedule O (Form 990 or 990-EZ) (2013)
40 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001
Form 8868 (Rev. 1-2014) ¥ If you are filing for an Additional (Not Automatic) 3-Month Extension, complete only Part II and check this box ~~~~~~~~~~ | Note. Only complete Part II if you have already been granted an automatic 3-month extension on a previously filed Form 8868. ¥ If you are filing for an Automatic 3-Month Extension, complete only Part I (on page 1).
Part II
Type or print File by the due date for filing your return. See instructions.
Additional (Not Automatic) 3-Month Extension of Time. Only file the original (no copies needed).
Name of exempt organization or other filer, see instructions.
VELLORE CHRISTIAN MEDICAL COLLEGE FOUNDATION, INC.
Enter filer's identifying number, see instructions Employer identification number (EIN) or
Number, street, and room or suite no. If a P.O. box, see instructions.
475 RIVERSIDE DRIVE, SUITE 725
13-2735359 Social security number (SSN)
City, town or post office, state, and ZIP code. For a foreign address, see instructions.
NEW YORK, NY
10115
Enter the Return code for the return that this application is for (file a separate application for each return) ~~~~~~~~~~~~~~~~~ Application Return Application Is For Code Is For Form 990 or Form 990-EZ 01 Form 990-BL 02 Form 1041-A Form 4720 (individual) 03 Form 4720 (other than individual) Form 990-PF 04 Form 5227 Form 990-T (sec. 401(a) or 408(a) trust) 05 Form 6069 Form 990-T (trust other than above) 06 Form 8870 STOP! Do not complete Part II if you were not already granted an automatic 3-month extension on a previously filed Form 8868. ¥
Page 2
X
0 1 Return Code 08 09 10 11 12
TEJAL SHAH The books are in the care of | 475 RIVERSIDE DRIVE, SUITE 725 - NEW YORK, NY 10115 Telephone No. | 212-870-2640 Fax No. |
¥ If the organization does not have an office or place of business in the United States, check this box ~~~~~~~~~~~~~~~~ | ¥ If this is for a Group Return, enter the organization's four digit Group Exemption Number (GEN) . If this is for the whole group, check this box | . If it is for part of the group, check this box | and attach a list with the names and EINs of all members the extension is for. NOVEMBER 15, 2014. 4 I request an additional 3-month extension of time until 2013 5 For calendar year , or other tax year beginning , and ending . 6 If the tax year entered in line 5 is for less than 12 months, check reason: Initial return Final return Change in accounting period 7 State in detail why you need the extension
ADDITIONAL TIME IS REQUIRED IN ORDER TO PREPARE A COMPLETE AND ACCURATE RETURN.
If this application is for Forms 990-BL, 990-PF, 990-T, 4720, or 6069, enter the tentative tax, less any nonrefundable credits. See instructions. b If this application is for Forms 990-PF, 990-T, 4720, or 6069, enter any refundable credits and estimated tax payments made. Include any prior year overpayment allowed as a credit and any amount paid previously with Form 8868. c Balance due. Subtract line 8b from line 8a. Include your payment with this form, if required, by using EFTPS (Electronic Federal Tax Payment System). See instructions.
8a
Signature and Verification must be completed for Part II only.
8a
$
0.
8b
$
0.
8c
$
0.
Under penalties of perjury, I declare that I have examined this form, including accompanying schedules and statements, and to the best of my knowledge and belief, it is true, correct, and complete, and that I am authorized to prepare this form. Signature |
Title |
DIRECTOR OF NONPROFIT TAX
Date | Form 8868 (Rev. 1-2014)
323842 12-31-13
09481029 758275 3064.000
41 2013.04000 VELLORE CHRISTIAN MEDICAL C 3064_001