02 Welcome to VAM A message from the SVS president
06 TCAR
Data demonstrates durable long-term outcomes with few reinterventions
10 Vascular Workforce
How can vascular surgery build a workforce ready for future patient needs?
16 PAD
Research supports conservative approach to claudication in elderly patients
www.vascularspecialistonline.com
DEEP VEIN ARTERIALIZATION CHALLENGES NOTION OF ‘NO-OPTION’ CLTI
By Maria Gifford
“Patients previously considered ‘no-option’ may no longer truly be without options,” said Anahita Dua, MD, associate professor at Harvard Medical School and a vascular surgeon at Massachusetts General Hospital. That assertion sums up the central finding of an analysis comparing deep vein arterialization (DVA) with the current standard of care for nooption chronic limb-threatening ischemia (CLTI) which Dua presented during the Women’s Section session on Thursday. No-option CLTI represents the most severe end of the peripheral artery disease spectrum, encompassing patients who have exhausted conventional revascularization options and face extremely high rates of major amputation and death. Historically, once classified as no-option, clinical conversations shifted from limb salvage toward amputation planning. DVA offers an alternative by routing oxygenated arterial blood retrograde through the venous system to perfuse ischemic
foot tissue, bypassing the absence of viable distal arterial targets entirely.
“What makes DVA so important is that it creates a pathway to perfuse tissue in patients who otherwise have no distal arterial targets available for conventional revascularization,” said Dua. “In many ways, it transforms a previously unsalvageable limb into one with a realistic opportunity for healing and preservation.”
The study compared outcomes from the PROMISE trials with those from the CLariTI registry, a prospective observational study reflecting the natural history and standardof-care management of no-option CLTI patients. At one year, limb salvage rates reached approximately 71% in the DVA cohort versus 50% in the standard-of-care cohort.
Starting Friday at 6:30 a.m. is the Arab American Vascular Surgeons Section, highlighting how Arab American vascular surgeons contribute to improving patient care, training, research and global collaboration. Plenary Session 5 follows directly after at 8:00 a.m. in Ballroom B on the third floor. At 10:00 a.m. is Plenary Session 6. Linda Harris, MD, will then introduce the presidential address at 11:00 a.m., which will be given by Keith Calligaro, MD. Later in the afternoon, Hall D plays host to the Trainee Recruitment and Networking Fair at 3:30 p.m., presented by SVS in collaboration with the Association of Program Directors in Vascular Surgery (APDVS), offering trainees the opportunity to connect directly with vascular surgery residency and fellowship programs.
SVS members will convene for the annual Business Meeting on the third floor in Ballroom A at 5:15 p.m.
Don’t miss the opportunity to connect with industry colleagues in the Exhibit Hall, which is open from 9:30 a.m.-2:00 p.m. Make sure to also check out some hands-on learning at the Wound Care Pavilion and Touchpoint @ VAM.
Saturday morning highlights include Plenary Session 7 taking place in Ballroom A from 7:009:30 a.m. The Wesley S. Moore Distinguished Lecture follows at 9:30 a.m., which will see Peter Schneider, MD, discussing the future of carotid disease management after the CREST-2 trial.
Later that morning, the Poster Championship will run from 10:15-11:15 a.m. and the day will end with Plenary Session 8 from 11:15 a.m.-12:30 p.m.
Medical Editor Malachi Sheahan III, MD
Associate Medical Editors
Bernadette Aulivola, MD | O. William Brown, MD | Elliot L. Chaikof, MD, PhD | Carlo Dall’Olmo, MD | Alan M. Dietzek MD, RPVI, FACS | John F. Eidt, MD | Robert Fitridge, MD | Dennis R. Gable, MD | Linda Harris, MD | Krishna Jain, MD | Larry Kraiss, MD | Joann Lohr, MD | James McKinsey, MD | Joseph Mills, MD | Erica L. Mitchell, MD, MEd, FACS | Leila Mureebe, MD | Frank Pomposelli, MD | David Rigberg, MD | Clifford Sales, MD | Bhagwan Satiani, MD | Larry Scher, MD | Marc Schermerhorn, MD | Murray L. Shames, MD | Niten Singh, MD | Frank J. Veith, MD | Robert Eugene Zierler, MD Resident/Fellow Editor
Letters to the editor vascularspecialist@vascularsociety.org
Published by the Society for Vascular Surgery
WELCOME TO VAM: A MESSAGE FROM THE PRESIDENT
At VAM26, we have an opportunity to reflect on another year of collaboration, progress and dedication to advancing vascular care. My sincere thanks to the SVS executive board, staff and all other volunteers on committees and task forces for a very productive year. Together, your efforts continue to strengthen our society, support innovation, foster education and improve care for patients everywhere.
SVS external issues
CREST-2: The SVS addressed the controversial results of this study in a commentary: Aburahma A, Schermerhorn M, Calligaro KD. J Vasc Surg 2026;83:971-973.
AHA/ACC PULMONARY EMBOLISM GUIDELINE UPDATE:
In a discussion with AHA/ACC guideline leadership, SVS leadership clearly voiced our displeasure with their process. They informed us that SVS was not deliberately excluded, they have accelerated their next Pulmonary Embolism Guideline Update to 2027 and they will invite the SVS to participate. They sincerely apologized and pledged to include the SVS in all future guidelines dealing with vascular disease.
INTER-SOCIETY GUIDELINE MANUSCRIPTS: I asked Matthew Eagleton, MD, to chair a task force to develop an Intersociety Memorandum of Understanding (MOU) regarding guidelines for joint manuscripts initially with SCAI, SIR and SVM.
SVS, CARDIOLOGY, RADIOLOGY, AND VASCULAR MEDICINE LEADERSHIP MEETING: SVS leadership met with Cardiology (SCAI), Radiology (SIR) and Vascular Medicine (SVM) leadership to address shared issues and have continued bi-monthly dialogues.
SVS intrinsic issues
INTERNAL REVIEW OF SVS EXECUTIVE BOARD (EB): For the first time, the EB completed surveys of EB members to identify areas of improvement regarding overall board functioning and individual EB members, along with the Executive Director.
EXTERNAL REVIEW OF FUTURE SVS STRATEGIC
Vascular Specialist is the official newspaper of the Society for Vascular Surgery and provides the vascular specialist with timely and relevant news and commentary about clinical developments and about the impact of healthcare policy. The ideas and opinions expressed in Vascular Specialist do not necessarily reflect those of the Society. The Society for Vascular Surgery will not assume responsibility for damages, loss, or claims of any kind arising from or related to the information contained in this publication, including any claims related to the products, drugs, or services, or the quality or endorsement of advertised products or services, mentioned herein. | The Society for Vascular Surgery headquarters is located at 9400 W. Higgins Road, Suite 315, Rosemont, IL 60018. |
ALIGNMENT: For the first time, an external consultant was hired to provide a process to conduct a comprehensive evaluation of SVS programs with the goal to contain costs for members (dues, VAM registration fees). Thus far, SVS staff and the EB reviewed 20 SVS programs and will sunset three. The EB will convene in July to evaluate the staff’s review of 60 other programs.
SVS EXECUTIVE DIRECTOR (ED) TRANSITION PLAN: For the first time, SVS leadership, the ED and staff created a comprehensive 47-page document clearly delineating a transition plan for the ED that was approved by the Executive Board.
ETHICS VIOLATION OF SVS EXPERT WITNESS TESTIMONY: The Executive Board updated the SVS Disciplinary Policy for Expert Witness Testimony by a member who was deemed to provide fraudulent testimony.
INCREASING OUR VISIBILITY: Our branding efforts continued with Megan Tracci, MD and Megan Marcinko spearheading our SVS Advocacy Conference in Washington, D.C., on Sep. 14-16, 2026. The meeting was attended by SVS leadership and 50 vascular surgeons.
ACS/SVS VASCULAR VERIFICATION PROGRAM: Through the hard work of Tony Sidawy, Clem Darling, Bill Shutz, Dennis Gable and Anil Hingorani, there are now 12 accredited programs, 30 total applications with 21 committed applications, 19 site visits completed, 5 sites in corrective action and 65 hot leads.
RE-ALIGNING FUNCTIONS OF THE SVS STRATEGIC BOARD OF DIRECTORS (SBOD): SVS President-elect Linda Harris led a working group which suggested sunsetting the current SBOD and instead creating: 1.) Advisory Council of Vascular Surgery Societies and 2.) Executive Board Strategic Planning Committee. There will be a bylaws referendum included in the election ballot for ratification in June 2026.
OPTIMIZING COLLABORATION ACROSS SVS COUNCILS: SVS Vice-President Andy Schanzer has been leading meetings of the five SVS Council Chairs to address strategic priorities.
SVS SECTIONS: SVS Vice-President Schanzer reported the recommendations of a working group to clarify and re-define the role of sections.
SVS SENIOR SECTION (PROVISIONAL): Enrico Ascher, MD, chair, has overseen many useful projects during this initial year.
VASCULAR SURGERY BOARD MODEL: The EB voted to continue with the current Federated Vascular Surgery Board model. A working group chaired by Dennis Gable, MD, presented recommendations to establish a potential preparedness plan for an application for a free-standing board, which will be discussed by the EB in July.
VASCULAR SPECIALIST: SVS began self-publishing Vascular Specialist in February. SVS Secretary Mal Sheahan continues as editor-in-chief and SVS members as assistant editors.
CMS REIMBURSEMENTS: Through the efforts of the SVS Coding Committee and RUC/CPT advisors, CMS proposed to accept the physician work recommendations for all 46 new lower extremity codes. Vascular Surgery MVP (MIPS Value Pathway) was also included in the proposed rule, which will reduce the reporting burden and improve payments for vascular surgeons. My thanks to Evan Lipsitz (QPMC), David Han (Coding/RUC), Joe Hourani (GRC-PAC), our Advocacy, Clinical Practice and Quality Councils, Megan Marcinko (SVS Director of Public Affairs) and Carrie McGraw (SVS Manager, Quality Improvement and Practice).
CLINICAL PRACTICE GUIDELINES (CPGS): Britt Tonnesson, MD (chair, Document Oversight Committee) has been instrumental in stream-lining production of CPGs.
I want to thank SVS Executive Director Ken Slaw and his staff for their help and dedication.
KEITH CALLIGARO, MD
DEEP VEIN ARTERIALIZATION CHALLENGES NOTION OF
‘NO-OPTION’ CLTI
continued from page 1
Amputation-free survival was also significantly improved, as were wound healing trajectories, with many patients progressing from nonhealing wounds toward outcomes Dua describes as historically unlikely.
“The most striking finding was the magnitude of benefit observed with DVA compared with standard care,” said Dua. “That consistency across prospective trials and real-world practice is incredibly encouraging and suggests this is not an isolated signal but a therapeutic advance for no-option CLTI patients.”
Major amputation in this population carries serious consequences, including loss of independence, recurrent hospitalizations and high mortality, making even incremental gains in limb salvage clinically important. Dua argued that DVA’s benefit must be weighed against all of those realities, not simply the technical outcome of the procedure itself. “The procedure is not simply about saving a limb anatomically,” she said. “If we can safely reduce amputations in this population, the impact extends far beyond the operating room.”
CEA
CAROTID
“There is still tremendous opportunity to refine patient selection and improve durability and continued evaluation will help establish DVA as a durable standard within modern limb preservation programs.”
ANAHITA DUA, MD
Dua said the study also raises a timely question about sequencing.
Traditionally reserved as a last resort, DVA’s strong performance prompts reconsideration of whether earlier intervention, specifically in rest pain patients before tissue loss becomes irreversible, could improve outcomes further. Success also requires surrounding infrastructure, including coordinated wound care, infection management, anticoagulation, offloading and multidisciplinary follow-up.
Dua said further research into wound-healing biology, microvascular remodeling after DVA and optimal antithrombotic strategies for maintaining long-term patency is needed. Identifying perfusion-based or imaging biomarkers to sharpen patient selection is another priority, alongside
ENDARTERECTOMY
TIED TO LOWER STROKE, MORTALITY RATES THAN STENTING
By Killian Meara
Carotid endarterectomy (CEA) was associated with significantly lower longterm stroke and mortality compared to carotid artery stenting (CAS) in patients with asymptomatic carotid artery disease, according to a new real-world analysis. The study, which is being presented during Saturday’s Plenary Session 7 (7:00-9:30 a.m.), compared outcomes between patients undergoing CEA and CAS for asymptomatic carotid stenosis and evaluated stroke, mortality and the combined outcome of stroke or death at multiple time points extending to five years.
Data was gathered from TriNetX, a large, international electronic health
expanded real-world data across broader populations and health care systems.
“The next step is to better define which patients benefit most, when intervention should occur and how we optimize perioperative and postprocedural management,” said Dua. “There is still tremendous opportunity to refine patient selection and improve durability and continued evaluation will help establish DVA as a durable standard within modern limb preservation programs.”
For a population that has long had few options, Dua said those possibilities represent a fundamental shift in what the disease trajectory can look like.
“For many of these patients, DVA is an opportunity to preserve independence, mobility and quality of life when amputation once seemed inevitable,” she said.
record data set that aggregates longitudinal real-world data from multiple institutions.
The study included more than 100,000 patients with asymptomatic carotid artery disease who underwent either CEA or CAS between January 2005 and January 2025 in the United States. To reduce treatment bias, investigators performed a one-to-one propensity score–matched analysis.
“The key finding in our study was that CEA consistently demonstrated lower stroke rates compared to CAS at every time point,” said Anthony Chau, MD, senior author on the study. “Additionally, the composite outcome of stroke or death significantly favored CEA at all the time intervals.”
While early outcomes were similar between procedures, CEA demonstrated a statistically significant survival benefit at three years. “Overall, the data suggests a more durable long-term advantage of CEA over CAS in asymptomatic patients,” said Chau.
Chau said the results suggest procedural choice may have important implications well beyond the perioperative period.
“Our findings suggest that in appropriately selected asymptomatic patients, CEA may
FROM THE EDITOR
The unofficial vascular surgeon’s guide to Boston
Welcome to Boston! As you gather here for another outstanding VAM, I thought it only fair to provide a few curated local suggestions from your Boston colleagues (who assure me these are far better than anything from my own residency-era memories). Special thanks to Sunita Srivastava, Matt Eagleton, Keith Ozaki and Jeff Siracuse for the recommendations. And also to the vascular faculty at my alma mater BI Deaconess, who kept tradition alive by ignoring all my emails.
Start your day at Tatte or Flour, although Dunkin is mandatory at least once, if only for cultural literacy. When hunger evolves from “I could eat” to “This is now a clinical issue,” go directly to the North End. Regina Pizza (the original — do not freelance here) or Santarpio’s are both local institutions.
If your RVUs have treated you well, Boston offers Sorellina, Mistral, Select Oyster Bar and Saltie Girl. Add Woods Hill Pier 4 (waterfront views), Row 34 (dependable seafood), or Contessa (rooftop views). Need atmosphere? Try Yvonne’s or Mariel. Bogie’s Place brings steak and the quiet confidence of somewhere that doesn’t need a sign.
For those on a resident salary (or unable to acquire an industry benefactor), GRE.co, Luke’s Lobster Shack, Mike’s Diner and the Eataly food hall provide reliable returns on limited capital.
Traveling with family? The Duck Tour and Boston Tea Party Museum offer equal parts history and chaos.
When touring the city remember these streets predate the invention of the internal combustion engine. Boston distances are measured in time, elevation change and regret. If you get lost (you will), just commit to it. The city rewards confidence, even when misplaced. This is, after all, where I met my wife.
be the preferred intervention when we consider long-term stroke prevention and survival as our primary goals,” he said. “Although perioperative outcomes may be relatively comparable, the divergence in outcomes over time indicates that the procedural choice actually has very meaningful long-term consequences.”
According to Chau, the findings may also help inform conversations with patients when deciding between treatment options. “When counseling patients, it’s really important to emphasize that while both procedures are overall safe in the short term, CEA appears to offer a small yet consistent long-term benefit in reducing stroke risk and improving survival,” he said. “This allows for more nuanced discussion that balances shortterm recovery considerations with longterm outcomes.”
While the TriNetX database allows for greater capture of long-term outcomes data, Chau said that it does not give as much detail on procedural precision like the Vascular Quality Initiative (VQI). That’s why one of the study’s key limitations is that the CAS cohort included both transfemoral and
transcarotid stenting approaches, which Chau said could influence outcomes and may not reflect results of either procedure in isolation.
The study reflects broader realworld outcomes across a large patient population, which Chau said may complement findings from randomized trials. “While clinical trials provide level one evidence, they’re fairly highly selected,” he said. “It’s hard to generalize clinical trial data to real-world practice. But our data suggests that when we’re optimizing patient selection for CEA versus CAS, CEA could really improve long-term neurologic and survival outcomes at the population level.”
He added that the data support continued refinement of guidelines and shared decision-making strategies as clinicians weigh intervention choices. “In asymptomatic carotid disease, CEA does provide a consistent and meaningful long-term advantage over CAS in reducing both stroke and improving survival,” said Chau. “Despite some similar short-term outcomes, the long-term outcomes are where it really diverges.”
STUDY EXPLORES WHEN AAA SURVEILLANCE MAY NO LONGER BENEFIT OLDER PATIENTS
By Killian Meara
New research suggests that surveillance for small abdominal aortic aneurysms (AAA) may not always provide meaningful benefit in older patients, particularly those with significant comorbidities. The data is set to be presented during Plenary Session 5 (8:009:30 a.m.) by Sowmya Mangipudi, MD, MSc.
The study examined whether there may be a point at which continued AAA surveillance is unlikely to change outcomes because patients are far more likely to die from other causes before the aneurysm progresses to a size requiring intervention.
“The question of this paper is really getting at when to end AAA surveillance, if ever,” said Mangipudi, first author on the study and a resident physician at the University of California San Francisco. “There aren’t really great guidelines around which patients it makes sense to stop surveillance for. The goal of this paper was to try to generate highquality evidence that might be able to help us inform guidelines going forward.”
The analysis drew data from Kaiser
Permanente’s Northern California Regional Thoracic Aortic Aneurysm Surveillance Program, which has tracked arterial aneurysms since 2007 across 19 medical centers serving roughly five million patients. Investigators evaluated over 10,600 patients aged 65 years and older with AAA or ectatic aorta.
Using a validated large language model from a previous study, the researchers extracted maximal aneurysm diameters from radiology reports and analyzed patient outcomes over time. Primary outcomes included death, aneurysm progression to an operable size and aneurysm repair. Predictive modeling was then used to determine which patients had a greater than 90% likelihood of dying before their aneurysm progressed or required surgery.
The data showed women older than 85 with aneurysms smaller than 3.5 cm and men over 80 with aneurysms smaller than 3.5 cm had a 90% or greater chance that their first event was death. In patients with higher comorbidity burdens, there was a 90% or greater chance of death prior to reaching operative size at 75 years
of age or older for men with AAA 2.7 to 3.4 cm, 85 years or older for men with AAA under 4 cm and 85 years or older for women with AAA 2.7 to 3.4 cm.
“While we calculated this for the 20th and the 80th percentile, you could hypothetically calculate this for any percentile comorbidity in the cohort,” said Mangipudi. “The idea is that you could look at these tables and say, ‘I have an 85-year-old patient and they have a low comorbidity burden and their starting AAA scan size is 3.2 cm. Do I need to continue to recommend professional imaging every three years?’”
Sowmya Mangipudi, MD, MSc
with?’ If you’re anxious and you feel like you need to continue to advance, that is absolutely fine.”
The study also raises questions about the broader burden of imaging in elderly patients who are unlikely to ever require intervention. Mangipudi said the findings could help reduce unnecessary testing, referrals and patient anxiety while allowing clinicians to better tailor surveillance strategies based on overall health status rather than aneurysm size alone.
Mangipudi said the findings are not intended to establish rigid stopping rules, but rather to support individualized decisions between physicians and patients. “We’re hoping this will be a shared decisionmaking tool between surgeons and patients to be able to really look at these scales and say, ‘What level of risk are we both comfortable
“Whoever your patient is, there may be a safe point at which you can stop surveillance for their AAA,” said Mangipudi. “Based on how sick they are and the intuition that surgeons already use to make some of these decisions, we hope that this will be an evidence-based method to have that conversation with patients. A lot of people are already doing it, so hopefully this will just give them more confidence.”
“The goal of this paper was to try to generate high-quality evidence that might be able to help us inform guidelines going forward.”
SOWMYA MANGIPUDI, MD, MSC
Structured exercise after acute DVT may reduce long-term complications
By Killian Meara
New research being presented at Saturday’s Plenary Session 7 (7:00-9:30 a.m.) will show how structured aerobic exercise combined with standard anticoagulation in patients with acute lower extremity deep vein thrombosis (DVT) may help significantly reduce the risk of developing post-thrombotic syndrome (PTS). The study was funded by the Veterans Affairs Research and Development Department.
“We all understand and appreciate the most important short-term consequence of acute lower extremity DVT, which is pulmonary embolism,” said Brajesh Lal, MD, senior author on the study. “We’ve learned a lot about how to treat DVT in order to prevent pulmonary embolism. Increasingly, we’ve become aware that the long-term consequences of DVT in the form of PTS are very important and can lead to a lot of morbidity.”
Research estimates that PTS impacts 25% to 50% of patients within two years of DVT and can cause chronic pain, leg ulcers and severe disability. Several studies have evaluated endovascular interventions aimed at preventing PTS, but Lal noted they are primarily indicated in a small number of patients with severe DVT. “The vast majority of DVTs that occur are not in that category,” he said. “We don’t really have anything other than anticoagulation to prevent those long-term complications and we know that does not help much.”
For the study, 102 patients with acute lower extremity DVT within the past 30 days randomly received standard anticoagulation or anticoagulation combined with aerobic exercise. The exercise consisted of 30 minutes on a treadmill each day for three months. Patients were encouraged to exercise at roughly 50% of their
maximum tolerated effort.
Using the Villalta scale to measure PTS severity, the study found significantly lower average scores in the exercise group. Importantly, no patients in the exercise arm developed moderate or severe PTS, compared to roughly 15% of patients treated with anticoagulation alone.
“My hope is that these results provide reassurance to all physicians, but in particular non-vascular surgeons, that ambulating patients with DVT is not harmful and in fact is therapeutically beneficial.”
BRAJESH
LAL, MD
Lal said the findings challenge long-standing concerns about ambulation after DVT. “We’ve come a long way in our understanding of DVT,” he said. “Twenty years ago, if somebody developed a DVT, the traditional approach was that they were put on bed rest for anywhere from three days to a couple of weeks. Even after we realized that bed rest is not absolutely necessary, there was still a great deal of reticence in ambulating these patients to any major degree.”
According to Lal, vascular surgeons have generally become more comfortable encouraging early ambulation after DVT over the last decade, though that hesitation still persists in other specialties. “People worry about a risk of dislodging clots and causing pulmonary emboli
if you ambulate patients too much,” he said. “This study confirms that we need to ambulate our patients after DVT. The more consistent and sustained the ambulation, the better the long-term outcomes are going to be.”
Lal suggested that the intervention could be incorporated relatively easily into routine care because of its simplicity and low cost. While reimbursement for exercise programs remains limited for this particular indication, he said the study provides a practical framework clinicians can implement even now.
“My hope is that these results provide reassurance to all physicians, but in particular non-vascular surgeons, that ambulating patients with DVT is not harmful and in fact is therapeutically beneficial,” he said. “We need to engage in spreading the word so that we can begin to incorporate structured exercise as a standard adjunct to anticoagulation or an endovenous intervention that we may offer these patients.”
Flixene Vascular Graft
The Right Graft for AV Access
Designed for getting it right
The right graft for long lasting durability and proven reliability
The right graft for safe graft placement
The right graft for suturability and handling
The right graft for early cannulation
TCAR TCAR demonstrates durable longterm outcomes with few reinterventions
By Maria Gifford
Across more than 1,000 transcarotid artery revascularization (TCAR) procedures performed over eight years at a single high-volume institution, a recent study found only 12 patients required reintervention — a 1.1% rate that speaks to the durability of TCAR. The data also showed those reinterventions had a 100% technical success rate that speaks equally to the capacity of experienced teams to manage failure when it does occur.
TCAR received FDA approval in 2015 and has since seen rapid adoption for managing carotid artery stenosis, particularly in patients at elevated surgical risk. While its outcomes are well reported, data on what happens when TCAR fails and how best to address it has remained limited. The current study was designed to fill that gap, providing one of the largest single-center analyses of post-TCAR reintervention to date.
“TCAR has been increasingly utilized in the management of carotid artery disease and it’s important for physicians
to understand how to manage TCAR failure during followup,” said Venkata Vineeth Vaddavalli, MBBS, MS, a vascular surgery resident in the Department of Cardiothoracic and Vascular Surgery at the University of Texas Health Science Center at Houston, who presented the study during Thursday’s Plenary Session 3. “We retrospectively reviewed the indications for reintervention and the management strategies used on a case-by-case basis.”
The 1,086-patient cohort was medically complex, with comorbidities including coronary artery disease in 44%, diabetes mellitus in 45.1% and active smoking in 18.4%. Median age was 74.8 years and 30.7% of patients were symptomatic preoperatively. Technical success of TCAR reached 98.3%, with 30-day rates of ipsilateral stroke, myocardial infarction and mortality of 1.7%, 0.3% and 0.8%, respectively. Freedom from ipsilateral stroke at one, three and five years was 97.6%, 96.4% and 95.9% and overall survival at those intervals was 96.1%, 92.6% and 90.3%.
Among the 12 patients who required reintervention, instent restenosis greater than 70% was the most common indication, accounting for eight cases. The remaining cases involved common carotid artery stenosis proximal to a patent stent, a crushed stent and dissection causing stent stenosis. Two-thirds of reinterventions were managed endovascularly. All 12 reintervention cases were technically successful. “The reintervention rate after TCAR is low and reinterventions can be managed successfully either with open or endovascular techniques based on individual anatomy and risk factors,”
“We would like to direct future research toward identifying the risk factors associated with restenosis and reintervention following TCAR.”
VENKATA VINEETH VADDAVALLI, MBBS, MS
INDUSTRY@VAM
Pilling
Remington
Rooke
said Vaddavalli.
Vaddavalli said the results make a clear case for flexibility over protocol. Both endovascular and open strategies produced good outcomes when matched to each patient’s anatomy and risk profile and the study found no single technique universally superior — a finding that reinforces the value of a well-rounded technical skill set at centers where TCAR is regularly performed.
“Although the rate of reintervention is very low, the increasing number of TCAR procedures being performed highlights the importance for physicians at high-volume and tertiary care centers to be familiar with techniques for managing failed TCARs,” said Vaddavalli.
Beyond technical management, the study points to the role of patient compliance in sustaining TCAR’s longterm benefits. Smoking cessation, antiplatelet therapy and statin regimens are cited as essential to durable outcomes. These factors require ongoing reinforcement well after the index procedure.
Vaddavalli said that due to there being only 12 reintervention cases across the cohort, drawing firm conclusions about specific risk factors for restenosis was not possible. The low event rate, while itself a reflection of TCAR’s effectiveness, constrained the statistical analysis. “We would like to direct future research toward identifying the risk factors associated with restenosis and reintervention following TCAR,” he said. “Future multiinstitutional studies or studies with larger cohorts may help further delineate these risk factors.”
For centers where TCAR volume continues to grow, the study offers both reassurance and a practical charge: Understand the procedure’s failure modes and be prepared to manage them. “Performing TCAR in patients with suitable anatomy according to the instructions for use is associated with good long-term outcomes and only a small proportion of patients require reintervention during followup,” said Vaddavalli.
Stryker
SurgiTel 711
Exhibitor
Get done faster.
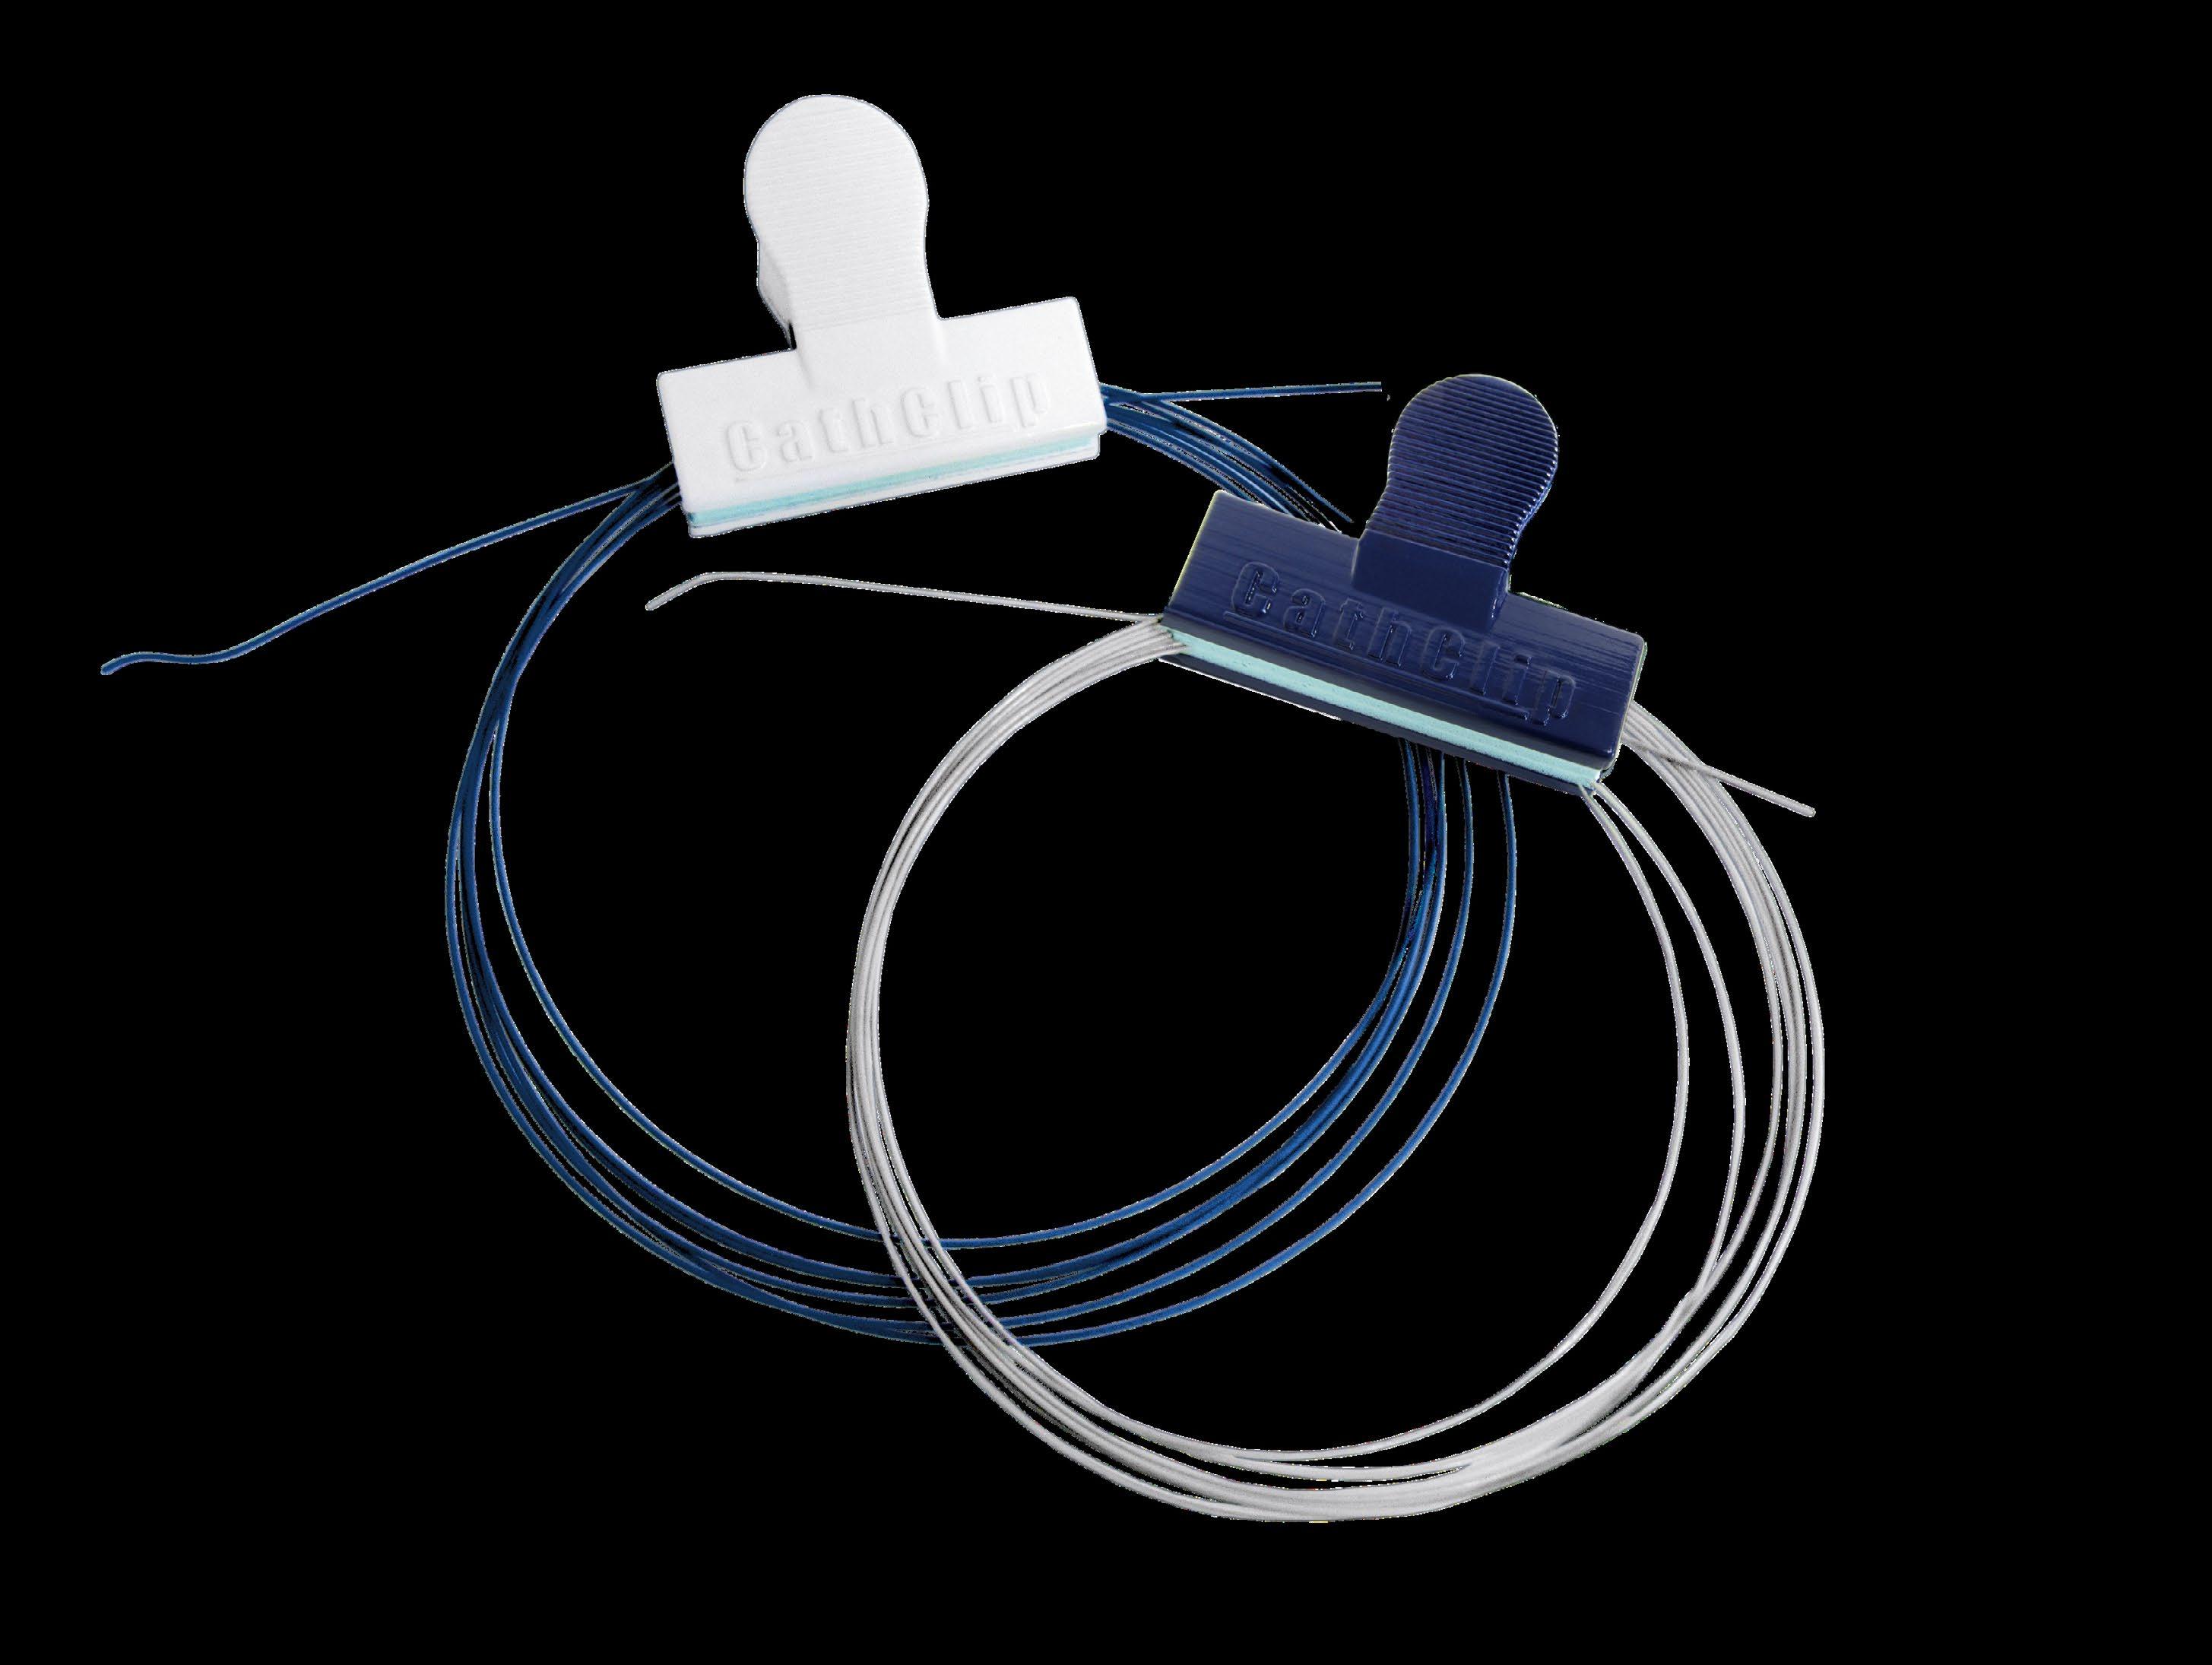
CathClip securely and gently holds any flexible elongated medical device - from the stiffest guidewires to the most fragile catheters and everything in between - with just a simple, easy clip. Reliable and consistent, CathClip reduces procedure times and helps avoid duplicate (replacement) devices.
Used in a variety of settings, from the largest health systems to independent surgery centers, CathClip can be ordered in stand-alone sterile pouches or incorporated into your procedure packs. CathClip pays for itself in material cost savings alone, with additional productivity and safety benefits. Have you tried CathClip yet?
To learn more, see where CathClip is used, and request it for your procedures, please visit us at CathClip.com.
How do vascular surgeons and other similar specialties come together for the benefit of the patient? That is the main question behind a session being given by Caitlin Hicks, MD, associate professor of surgery at Johns Hopkins School of Medicine, during “Leadership Corner: Turf Battles in Vascular Surgery” (3:30-5:00 p.m.). Vascular Specialist caught up with Hicks ahead of the presentation to discuss the topic’s importance in today’s health care landscape.
What is the background of this session?
Caitlin Hicks, MD: I’ve done a lot of research in the space looking at appropriateness of care or value-based care, specifically in peripheral vascular disease management. There’s been a lot of debate that has come up as a result of that, of whether or not one specialty or another is providing better or worse care. This talk is centered around how do we come together and how do we provide holistic care without doing the thing we tend to do, which is pointing fingers at other similar specialties that are all taking care of the same disease processes.
What are the main points of the session?
Hicks: It’s not us or them. How do we get a seat at the table and remove cardiology? That’s not the goal. The talk will be centered around how do we come together as a multispecialty physician group to reach a consensus on the best course of management for patients and how can we do it together? I’ll be pulling in lessons from BEST-CLI, which had a lot of groups that had multi-specialty teams, including specifically cardiology and vascular surgery. Then other examples in other disease processes, like PE, where there’s a lot of multispecialty involvement.
The key things I’ll be touching on is that it’s important for the society to have a seat at the table. All of the societies need to be coming together. We tend to do things very siloed. We do our own guidelines and the ACC [American College of Cardiology] does their own guidelines and nobody really talks to each other. What needs to happen to be effective, and I know that the SVS [Society for Vascular Surgery] leadership is working on this, is to try to come up with a way of doing these sort of larger documents where we have inclusion across the specialty spectrum so that we’re not having isolated
PRACTICE
‘IT’S NOT US VERSUS THEM’: RETHINKING MULTIDISCIPLINARY COLLABORATION IN VASCULAR CARE VASCULAR
By Killian Meara
guidelines that say different things.
The other thing is having a presence in the literature. I’ve made a big point in the last couple of years to publish in our vascular literature, but not just the vascular literature, because I think when you publish there, you’re just speaking to each other. We should try and publish in journals that reach a slightly different audience. If I’m trying to talk about PAD and I think cardiologists should be part of the conversation, then publishing some of the work in journals that have a cardiology readership can be very helpful. Another thing which I still need to do better at is to have presence at meetings. It’s not like vascular surgeons are only at vascular meetings and cardiologists are only at cardiologist meetings and there’s no crosstalk. But I think we need to do a better job as physicians of being cognizant of how we go to meetings and learn from each other. What are they doing that we can bring to our practice? What are we doing that the other specialties should be thinking about in theirs?
What was the driving force behind the session?
Hicks: What I’ve observed is that there’s a really fundamentally different way of thought processes around the treatment of PAD, depending on the specialty. We have cardiologists at Hopkins that treat PAD and they do a great job. They’re great technical surgeons. We just think about the disease process a little bit differently. Especially now in the setting of BEST-CLI, where we know that some people are better off getting open bypass and some people are perfectly good candidates to get an endo first strategy, having more dialogue is really helpful. Me and the cardiologist at Hopkins have really started over the last couple of years sharing patients. Just starting that dialogue, even if it’s just a one-on-one relationship, is the beginning of that multi-specialty care.
How important is cross-specialty collaboration?
Hicks: Talking amongst each other is ultimately for the benefit of the patient. The goal is to take care of the patient in the best way that we possibly can. We’re stronger together as opposed to isolated entities. It’s been shown in the diabetic foot ulcer space time and time again that multidisciplinary teams are much more effective in providing good outcomes than single specialty teams. The same is true
for patients with CLTI or claudication. It really deserves multidisciplinary management. There was the attempt at an individualized board certification by ACC last year that was ultimately unsuccessful. The SVS got very upset about that. What we need to do is come together and ask why they want that. How can we help? Does it make sense for us to have a specialty certification in treating PAD? In the work that I’ve done around appropriate care in the PAD space, vascular surgeons are not all doing excellent care. It’s not a single specialty problem. Do we need to have better training? I get a lot of patients referred from outside. When I look at what they’ve had as work up to that date, I’m like, “Where is this study? These things are missing.”
But that’s just not part of the paradigm of the person that referred them. I will send people out and they’ll text me asking “Did you do X, Y, or Z?” I’ll say, “No, that’s not really part of our standard workup.” Everyone has nuances in their personal practice but understanding what the minimum standards would be and trying to have conversations to ultimately funnel patients to the right treatment paradigms.
What’s the key takeaway?
Hicks: The key takeaway is it’s not us versus them. It’s us with them. How do we come together to provide the best care for the patient?
Patients with long complex SFA disease face treatment tradeoffs, and some have no desirable options.
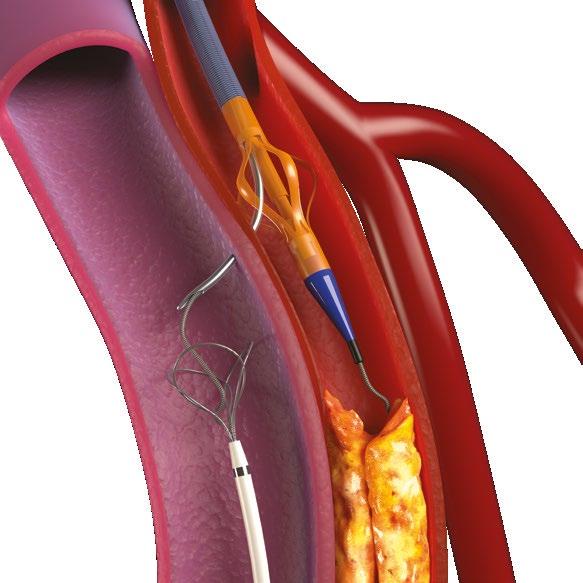
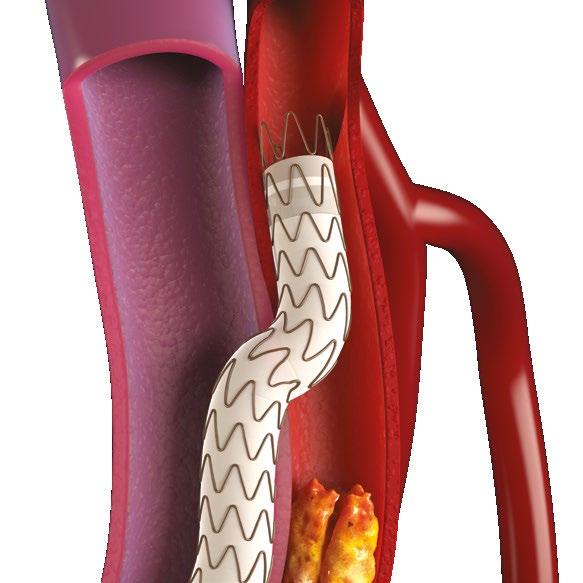
PTAB with the DETOUR™ System is the first-ever fully percutaneous transmural arterial bypass (PTAB) therapy to effectively bypass long femoropopliteal lesions.
PTAB with the DETOUR System
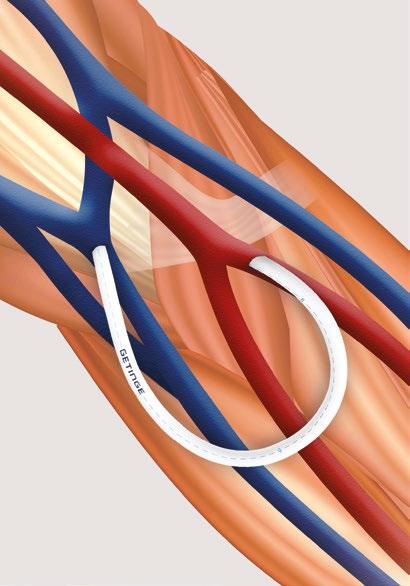
Under fluoroscopic guidance, the DETOUR System creates a femoropopliteal bypass routed through the femoral vein, delivering unobstructed flow from the superficial femoral artery (SFA) to the popliteal artery.
The ENDOCROSS™ Device enables guidewire delivery from artery to adjacent vein and vein to adjacent artery
The TORUS™ Stent Graft is deployed starting in the artery distal to the disease, working proximally to “detour” the entire blockage
Expand
Options for Complex PAD with PTAB
Scan to learn more
Shaping the vascular workforce of tomorrow
By Killian Meara
“I have been a staunch supporter of thinking ambitiously about how we maintain what should be a viable and thriving workforce that doesn’t just address capacity of surgical support but also training for what our patients need — not just our patients of today, but our patients 20 and 30 years from now,” said Dawn Coleman, chief of the Division of Vascular and Endovascular Surgery at Duke University.
That’s the central message of a presentation examining how vascular surgery can prepare for growing patient demand while ensuring the specialty remains attractive and sustainable for future generations of surgeons, which Coleman will deliver during the “Sub-specialization in Vascular Surgery: An Evolution for Advanced Care or Fragmentation of the Specialty” session (2:00-3:30 p.m.).
The discussion comes as vascular surgery faces a unique combination of challenges: an aging population requiring increasingly complex vascular care, geographic gaps in access to specialists and a need to recruit and retain enough surgeons to meet future demand.
While workforce shortages are a concern across health care, Coleman argued that vascular surgery faces particular pressures because of the specialty’s broad scope and
around-the-clock responsibilities. “We pride ourselves and feel so much value in being needed and responding,” she said. “But in the same breath, it is exhausting.”
Over the past two decades, integrated vascular surgery residency programs have helped address some of those challenges. Coleman said the training model has increased the number of trainees entering the field and expanded recruitment opportunities. It has also helped attract a more diverse group of applicants by drawing from a broader candidate pool that better reflects the patient populations vascular surgeons serve.
Still, significant workforce gaps remain, particularly in rural communities where access to vascular surgeons can be limited. “A huge area of need that is going to be a challenge for us is in the rural and community space,” said Coleman. “We’re going to see continued challenges in certain areas that will compromise access to vascular surgeons that can provide comprehensive care.”
Addressing those shortages will require more than simply training additional surgeons, Coleman argued. It will also require rethinking how the specialty recruits and supports future physicians.
Coleman said one priority should be exposing students to vascular surgery earlier in their medical education. “Students only know what they know,” she said. “Many people seem to not even understand the concept of what vascular surgery is. Early exposure is important.”
The presentation will also highlight changing motivations among younger physicians. Coleman said many trainees are increasingly interested in limb preservation, health equity and caring for underserved populations. “More and more I hear, ‘I want to save limbs. I want to take care of underserved patients,’” she said. “There’s this thread of service that feels a little bit different, and frankly, that’s what we need.”
Coleman also called for greater flexibility within training programs while maintaining the rigorous
standards required of vascular surgeons. Accommodating family responsibilities and evolving career goals, she argued, will be important for attracting and retaining talented trainees. “Just because I did something one way does not mean it should or has to be that way for somebody else,” she said. “It’s not the hardship Olympics.”
The presentation will ultimately focus less on workforce shortages themselves and more on the specialty’s opportunity to shape its future. “If we care about our patients, we’re going to care about sustaining a really healthy workforce for them,” said Coleman. “I think we have to be more intentional about that.”
Coleman also highlighted ongoing efforts through the Association of Program Directors in Vascular Surgery’s Vascular Forward Workforce Initiative, which is exploring approaches to recruitment, training and retention. Together, those efforts aim to ensure future patients have access to the vascular surgeons they will increasingly need in the decades ahead.
“We have to be careful in how we create a narrative,” said Coleman. “We all love our job. I love my job. I would do this over and over again. The rebranding and the valuation efforts that we are prioritizing right now as a specialty trickle over to training and they’re really important. We need to support those things. I would also encourage everybody to be intentional in a way that truly curates a collaborative work environment that is patient focused and that we retain a mindset of curiosity, and importantly, flexibility.”
Thank You SVS Industry Alliance Partners!
The Society for Vascular Surgery would like to thank the following companies for their support of the 2026 Vascular Annual Meeting and participation in the SVS Industry Alliance Program.
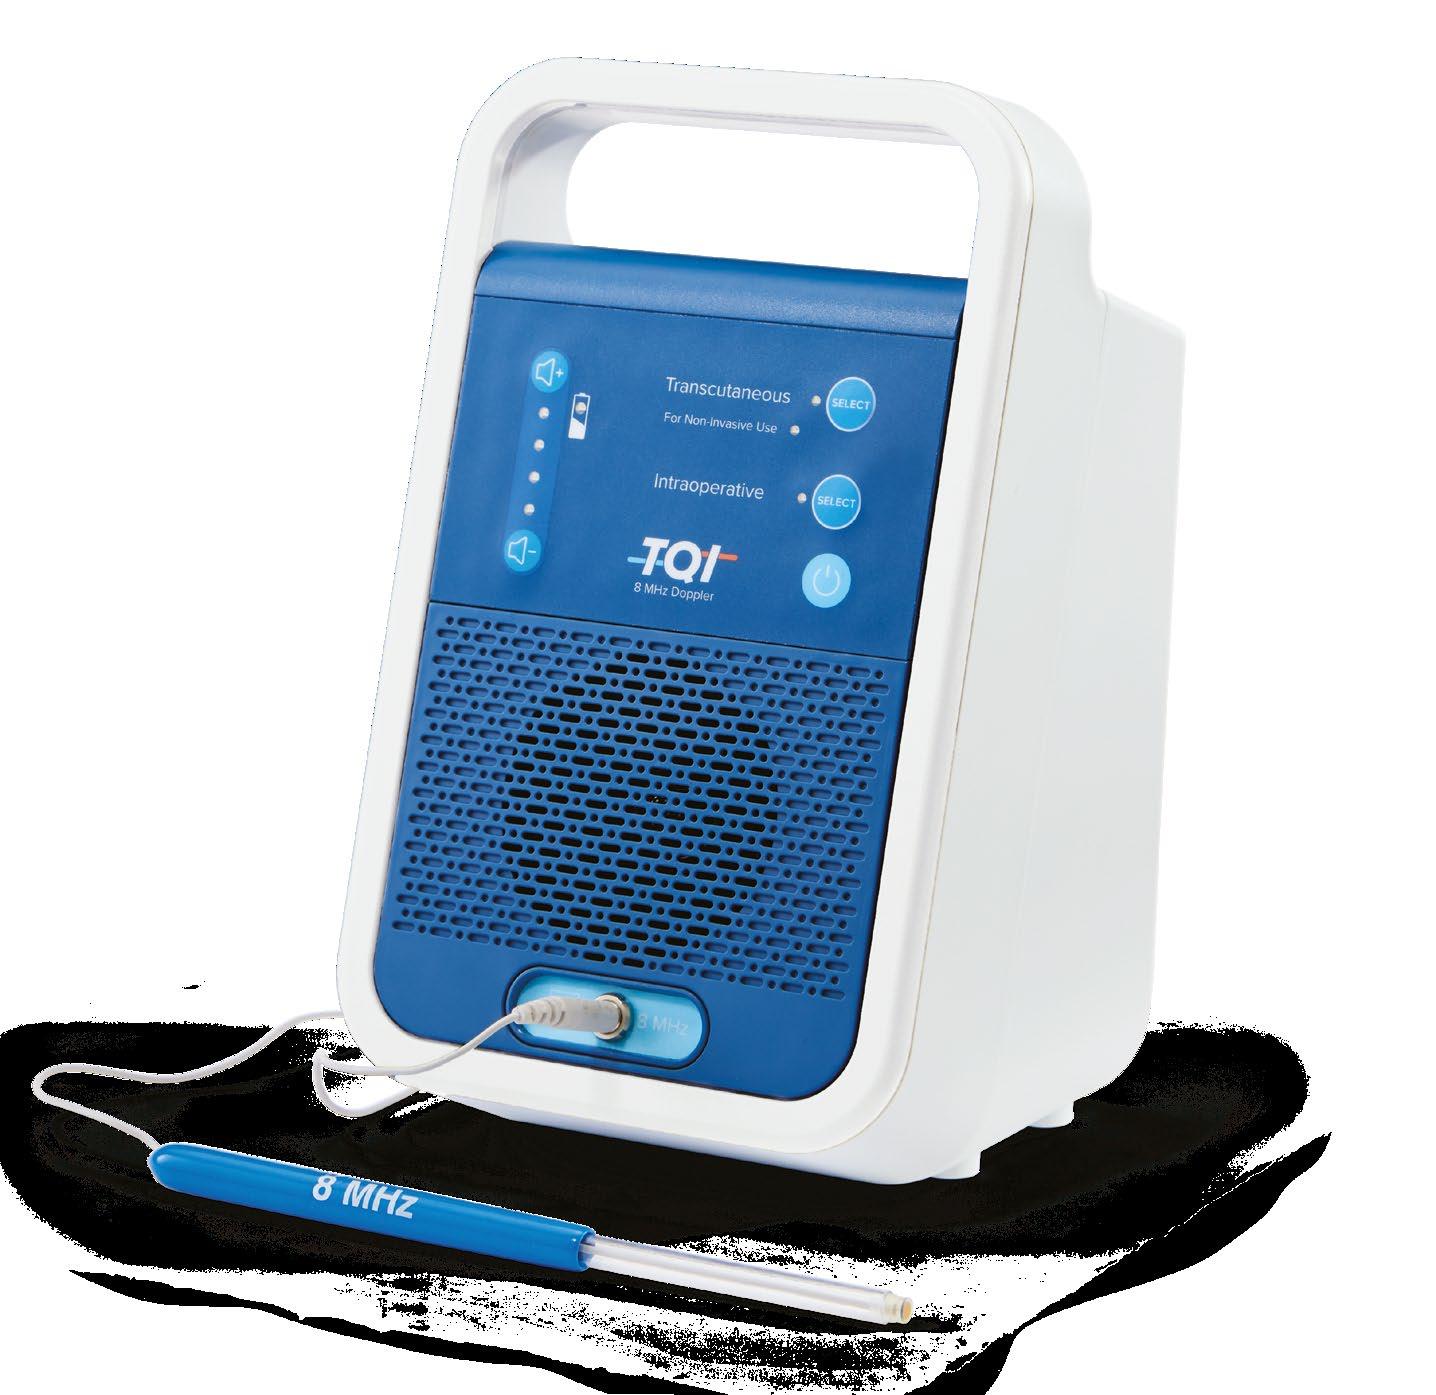
Confidence in THE Doppler that Works Surgical Doppler System
“Immediate confirmation of technical success.”
– Dr. McGinigle, Vascular Surgeon at University of North Carolina at Chapel Hill
TRUST
Single-use probe predictably works every time
QUALITY
Sterile probe is ready to use & reduces cross contamination
Unequal Access, unequal outcomes: Addressing disparities in acute limb ischemia
By Killian Meara
Although unequal access to care is contributing to persistent disparities in acute limb ischemia (ALI), there is a lot that surgeons can do to improve it. That’s the sentiment of Katharine McGinigle, MD, associate professor of surgery at UNC School of Medicine, who will deliver a presentation during “Modern Management and Controversies in Acute Limb Ischemia” (3:30-5:00 p.m.). McGinigle spoke with Vascular Specialist ahead of the session to discuss how clinicians can make an impact.
What is the background of this session?
Katharine McGinigle, MD: In everything we do in vascular surgery, it’s important to think about how we’re diagnosing the problem, treating it and following it long term due to a variety of factors. There may be completely reasonable differences in the way we deliver care to certain patients. It’s important to evaluate that to make sure that there are no unintended differences in care that end up disproportionately causing bad outcomes or delayed diagnosis, especially in peripheral artery disease [PAD]. The disparities can be really complex and interwoven. ALI brings that to a head because you have an emergency condition layered on top of a lot of long-term systemic barriers and challenges that we’ve been facing.
What are the main points of the session?
McGinigle: The disparity signal in ALI is consistent and reproducible. There is not a lot of literature about ALI in comparison to other vascular pathologies, but data from multiple data sources like the VQI, NSQIP and Medicare claims consistently show there’s differential rates of time to intervention. Although these are all retrospective studies, these disparities persist after adjusting for all of the comorbidities and disease severity. There’s some clinical complexity that plays in, but it’s not simply that. There’s structural drivers that are preventing equitable outcomes in ALI. Patients in rural areas have significantly less favorable outcomes. The “time is tissue” mantra that applies so effectively to stroke and heart attack doesn’t really seem to have the same panache for ALI. Rural patients tend to face critical delays in reaching vascular centers. Those are immutable things oftentimes, but there’s clearly improvements that can be made. In addition to geography, there’s some well reported systemic barriers that cause a higher risk factor burden for Black and Hispanic patients. Things like diabetes, hypertension, renal disease and progression of PAD. For Black patients specifically, it’s been shown they have a higher risk of ALI. They’re also significantly less likely to receive revascularization and have higher primary amputation rates.
Females also have some disparities. Females with ALI tend to be misdiagnosed, have longer time to diagnosis and time to intervention. They are presenting sicker with more advanced ischemia. Although they are less
likely than men to have AFib, they are more likely to have an embolic event because they’re less likely to get the appropriate medical treatment. There’s a lot of multifactorial drivers causing this later and more advanced presentation in women and that obviously has impacts on our surgical outcomes.
What can be done to fill those treatment gaps?
McGinigle: Most of the evidence is database driven retrospective research that has limited granularity. But there are a few multicenter case series, one of which I was happy to participate in that has just been published in the Journal of Vascular Surgery. Even with the granularity about clinical presentation and severity of other comorbidities, it’s hard to measure ALI because it’s so heterogeneous. Data on social determinants of health and distance from medical centers is taken from administrative data and racial and ethnic categories are often collapsed all within group variation that we don’t really measure. It all comes down to not being overwhelmed by all the things making patients sick and thinking about when that patient hits the door, what can you do at a clinical level? It’s worth it for every group to sit down and think about their decision-making frameworks. Who comes in and gets put on a heparin drip versus who gets rushed to the endo suite or the operating room? Why do you choose one intervention versus another? Which types of patients don’t even get offered a revascularization attempt and go straight to amputation? Create a care pathway so that trainees are more likely to get a structurally competent clinical pathway that also helps speed up the time from the door to revascularization. Doing audits to look at time from the initial event to the emergency department would be great to evaluate. All of those institutional level things should be audited and measured. We should strive to improve all of that because as you improve care for everybody, some of the unwarranted care variation will automatically go away.
What’s the key takeaway?
McGinigle: The take home message is that the timeline of getting a patient to your operating room, the decision making about what kind of operation you’re going to perform, system factors like insurance coverage and follow-up care, are all areas where we can make improvements. Just like the continuous quality improvement we do, there’s a lot we can look at individually to make sure we are treating everybody equally and that we are giving everybody the opportunity to experience that same high level of clinical expertise.
Anything else you wanted to share?
McGinigle: Some of my medical students and a team of qualitative researchers I work with have interviewed patients who suffered from ALI. The concept was to ask patients what an ideal recovery from ALI looked like. They also interviewed surgeons. Surgeons thought that being alive and having a limb was the goal. But patients had a more nuanced perspective about having a highly functional limb that was pain-free and being able to mitigate the mental health impact from having a medical emergency. All of the disparities that play into patients coming to the hospital and the way they get treated also impact their recovery. We haven’t moved through the research enough to figure out if there’s different geographic, sex or race and ethnicity differences in postoperative expectations but I think that’s a crucial point. ALI is an emergency that needs to get treated, but patients oftentimes have chronic disability related to it. Being thoughtful about offering postoperative care equally and giving people access to support is also really important but it’s often forgotten about in the setting of an emergency.
THROUGH THE LENS
ADVANCES IN MEDICAL MANAGEMENT COULD REDEFINE PAD CARE
By Maria Gifford
“Peripheral arterial disease [PAD] should no longer be viewed simply as a problem of arterial obstruction requiring procedural intervention,” said Mohamed Zayed, MD, PhD, associate professor of Surgery and Radiology at Washington University School of Medicine. That assertion cuts to the heart of a presentation making the case for fundamental rethinking of how PAD is diagnosed, treated and managed — and where medicine, not surgery, may ultimately prove the more powerful long-term tool.
According to Zayed, the argument for change begins with a recognition that PAD has long been underserved. Despite carrying substantial risks of myocardial infarction, stroke, amputation and death, the disease remains profoundly underdiagnosed and undertreated, with many patients presenting late in the disease course. That gap, Zayed argues, is partly a consequence of how the field has historically framed PAD as a “plumbing problem” rather than a systemic one.
“PAD is a systemic cardiometabolic and inflammatory disease that requires early diagnosis, aggressive medical therapy and comprehensive longitudinal management,” said Zayed, who presented during Thursday’s Hot Topics session. “The future of PAD care will depend on our ability to integrate advanced intervention with biology-driven medical therapies that prevent disease progression, reduce cardiovascular and limb-related complications and improve both survival and quality of life.”
The presentation reviewed an expanding class of pharmacologic and biologic therapies, including advances in lipid-lowering agents, antithrombotic strategies, GLP1 receptor agonists and anti-inflammatory compounds, each showing capacity to reduce major adverse limb events, functional decline and amputation risk. What sets these therapies apart is their mechanism: Rather than restoring blood flow mechanically, they target the biological drivers of disease progression directly.
“Many newer therapies appear to provide benefits that extend beyond traditional lipid lowering or glucose control,” said Zayed. “Modulation of inflammation, endothelial biology and metabolic signaling may represent major therapeutic opportunities for improving long-term PAD outcomes.”
That reframing carries direct implications for how revascularization fits into PAD care. Procedural intervention remains critically important, but Zayed argues it cannot address the systemic atherosclerotic instability and metabolic dysfunction that drive many of the worst outcomes. He said medical therapy and procedural care are complementary and the challenge is ensuring both receive equal clinical emphasis.
“Procedural intervention alone is insufficient,” said Zayed. “Durable improvements in patient outcomes require aggressive optimization of systemic medical therapy both before and after revascularization.”
The presentation also outlined a framework Zayed calls precision vascular medicine, in which biomarkers, advanced imaging and individualized risk profiling guide therapy selection for specific patients rather than applying a uniform protocol. This approach reflects a broader evolution in how the field understands PAD, treating thrombosis, endothelial dysfunction and metabolic dysregulation as distinct and addressable targets rather than byproducts of a single obstructive process.
Realizing those goals will also require structural changes in care delivery. According to Zayed, managing systemic disease across multiple biological domains calls for teams spanning
“Modulation of inflammation, endothelial biology and metabolic signaling may represent major therapeutic opportunities for improving long-term PAD outcomes.”
MOHAMED ZAYED, MD, PHD
vascular surgery, cardiology, endocrinology, primary care and preventive medicine, with implications not only for outcomes but for health system costs tied to repeated hospitalization, intervention and limb loss.
“Earlier and more aggressive medical management has the potential to reduce amputations, myocardial infarction, stroke and cardiovascular mortality in a population that historically experiences very poor outcomes,” said Zayed. “Beyond survival, these therapies may also preserve mobility, functional independence and quality of life in patients who often experience progressive disability and frailty.”
Zayed calls for PAD-specific clinical trials that go beyond traditional cardiovascular endpoints to capture limb outcomes, walking performance and quality of life, alongside investment in earlier detection tools, including blood-based biomarkers, artificial intelligence-enabled screening and advanced imaging capable of identifying disease before irreversible tissue injury occurs.
“We need improved strategies for earlier detection of PAD, particularly in high-risk populations such as patients with diabetes, chronic kidney disease and metabolic syndrome,” said Zayed. “Research into precision medicine approaches that integrate biomarkers, genomics, proteomics and imaging may ultimately allow clinicians to tailor therapies to the biological profile of individual patients and improve therapeutic effectiveness.”
SCHEDULE AT-A-GLANCE: FRIDAY AND SATURDAY
Friday, June 12, 2026
6:00 a.m. - 4:00 p.m. ET Registration
6:00 a.m. - 5:00 p.m. ET Speaker Ready Room
6:30 a.m. - 8:00 a.m. ET General Surgery Resident/Medical Student Session: Mock Interviews
CC, Second Level, Pre-function Hall C
6:30 a.m. - 8:00 a.m. ET S3: From Culture to Care: Arab Americans and Vascular Surgery (Arab American Vascular Surgeons Section (AAVSS)) Hynes CC, Third Level, Room 309
6:30 a.m. - 8:00 a.m. ET S4: Persistent Problems and Possible Solutions for the Outpatient Vascular Practice (SAVC Section)
6:30 a.m. - 8:00 a.m. ET S5: Advancing Pediatric Vascular Care – Innovation, Integration and Impact (Pediatric Vascular Care Section (SPVC)) Hynes CC, Third Level, Room 304
6:30 a.m. - 8:00 a.m. ET S6: A Lid for Every Pot, Finding Your Niche in Vascular Surgery (YS Section)
8:00 a.m. - 9:30 a.m. ET P5: Plenary Session 5
9:00 a.m. - 5:00 p.m. ET Crossroads@VAM
9:00 a.m. - 5:00 p.m. ET SVS Central @ VAM
9:30 a.m. - 10:00 a.m. ET Vascular Live: Endologix Presents: Rethinking the Route: PTAB with DETOUR for Challenging SFA Cases – A deep dive look into the DETOUR™ clinical evidence, patient selection guidelines and procedural tips for a successful procedure
p.m. - 2:00 p.m. ET Lunch Break with the Exhibitors
12:10 p.m. - 12:35 p.m. ET Vascular Live: Abbott Presents: One Platform, Multiple Lesions. Redefining the Treatment of Complex Calcified Disease with Diamondback 360 Exchangeable
2:00 p.m. - 3:30 p.m. ET C12: Pelvic Venous Disease in Practice: Case-Based Insights Beyond Tips and Tricks
2:00 p.m. - 3:30 p.m. ET C13: Spine Access Surgery: How I Do It, Tips, and Pitfalls
2:00 p.m. - 3:30 p.m. ET C14: Real Talk- Textbook Versus Practice: Forearm Dialysis Access
2:00 p.m. - 3:30 p.m. ET C15: Sub-specialization in Vascular Surgery: An Evolution for Advanced Care or Fragmentation of the Specialty
2:00 p.m. - 3:30 p.m. ET Penumbra Vascular Face Off: The Race to Reperfusion
3:00 p.m. - 4:30 p.m. ET Leadership Development Program Kick-off and Orientation (Invitation Only)
3:30 p.m. - 5:00 p.m. ET C16: Modern Management and Controversies in Acute Limb Ischemia (ALI)
3:30 p.m. - 5:00 p.m. ET C17: Thoracic Outlet Syndrome: Modern Day Challenges Require Contemporary Solutions
3:30 p.m. - 5:00 p.m. ET C18: Management of the Complex Hemodialysis Access Patient
3:30 p.m. - 5:00 p.m. ET C19: Leadership Corner: Turf Battles in Vascular Surgery
3:30 p.m. - 5:00 p.m. ET SVS-APDVS-VESS Trainee Recruitment and Networking Fair
CC, Third Level, Ballroom A
Second
Hall D 5:15 p.m.- 6:15 p.m. ET Member Business Meeting (Members Only)
Saturday, June 13, 2026
6:30 a.m. - 12:30 p.m. ET Speaker Ready Room
7:00 a.m. - 9:30 a.m. ET Continental Breakfast in Plenary
Ballroom A 7:00 a.m. - 9:30 a.m. ET P7: Plenary 7/Late Breaking Abstracts
7:00 a.m. - 1:00 p.m. ET Registration
9:30 a.m. - 10:00 a.m. ET Wesley S. Moore Distinguished Lecture
A 10:00 a.m. - 10:15 a.m. ET Coffee Break
Third
Ballroom Pre-Function 10:15 a.m. - 11:15 a.m. ET Poster Championship
CC, Third Level, Ballroom A 11:15 a.m. - 12:30 p.m. ET P8: Plenary Session 8
Data support conservative approach to claudication in elderly patients
By Maria Gifford
Claudication rarely takes a limb. But in patients over 80, the attempt to treat it surgically may take something just as important. New data, presented Thursday by Jeffrey Siracuse, MD, makes the case that for octogenarians with intermittent claudication, the risks of invasive revascularization routinely exceed its benefits.
The clinical tension at the center of the presentation is not new, but the scale of data supporting it is. Managing claudication in octogenarians has long required balancing symptom relief against procedural risk and that balance has historically been difficult to assess without large-scale outcomes data specific to this age group. Siracuse’s analysis used registry data to examine exactly that question, with findings that raise serious concerns about how frequently the surgical option is being chosen.
“Interventions for claudication in the elderly are high-risk with often diminishing returns,” said Siracuse, professor and chief of the Division of Vascular and Endovascular Surgery at Boston University. “Preserving mobility with conservative management should be balanced with risk for intervention.”
The data show that octogenarians face significantly higher 30-day mortality rates and increased access-site complications compared with younger patient cohorts. One year after an intervention, elderly patients demonstrate a markedly lower likelihood of remaining independently ambulatory, a finding that strikes at the core of what surgical treatment for claudication is supposed to achieve. If the goal is preserving
functional independence, a procedure that undermines it fails on its own terms.
“We need to judge procedural success by durability and improved functional status, not just a patent vessel,” said Siracuse. “Teams must engage in robust shared decisionmaking with patients, transparently weighing marginal symptom relief against the very real risks of permanent functional decline and perioperative complications.”
Beyond the outcomes data, the presentation also highlights a procedural timing concern that many elderly patients are undergoing invasive intervention before exhausting noninvasive options. Supervised exercise therapy and optimal medical management remain underutilized in this population, yet both carry substantially lower risk profiles than surgery and have established efficacy in improving claudication symptoms and walking performance.
“For older patients, surgery should be a last resort rather than a first-line treatment,” said Siracuse. “Claudication rarely leads to limb loss and the risk of complications makes conservative management the safest standard of care in most cases.”
The Society for Vascular Surgery (SVS) has published criteria specifically addressing when surgical intervention is warranted in claudication patients and Siracuse frames adherence to those guidelines as both a clinical and ethical obligation. Treating a patient who has not yet attempted supervised exercise or optimized medical therapy represents a missed opportunity to achieve symptom relief without
exposing an elderly patient to the mortality and complication risks that registry data now quantify.
“Surgeons should follow the SVS criteria and reserve surgery only for those who have failed conservative management and are likely to benefit,” said Siracuse.
Siracuse said comparative studies focused specifically on frail elderly patients that measure supervised exercise against intervention on functional outcomes, not simply vessel patency, are needed. He also pointed to the rise of outpatient procedure centers as an area warranting scrutiny, noting that research should examine whether that setting is contributing to a higher frequency of procedures in patients who might be better served by conservative care first.
The broader message, Siracuse says, is one of recalibration — not an argument against surgery, but a call to apply it where evidence supports genuine benefit rather than where it’s technically possible.
“Care should be individualized,” said Siracuse. “The goal is durable functional improvement and preserved independence, not a patent vessel, and achieving that requires honest conversations with patients about what the data actually show for their age group.”
SVS PAC, the Society’s political action committee, has long functioned as a foundational element of SVS’ advocacy efforts. On behalf of the SVS Executive Board and the Advocacy & Policy Council leadership, we extend a special thanks to these individuals for their long-term support of SVS PAC.
In the coming months, be on the look for a new profile series featuring some of these SVS advocacy leaders to learn about their experiences and perspectives relating to advocacy engagement on why every SVS member should be supporting SVS PAC.
Babak Abai, MD 10+
Ali F Aburahma, MD 10+
Francesco A Aiello, MD MBA 10+
Bernadette Aulivola, MD 15+
J. Dennis Baker, MD 10+
John Blebea, MD MBA 10+
Ruth L Bush, MD JD MPH 10+
Keith D Calligaro, MD 10+ $10,000+
Kristofer Charlton-Ouw, MD 10+
Dawn M Coleman, MD 10+ $10,000+
Carlo A Dall'olmo, MD 10+
Ronald L Dalman, MD 15+
Michael C Dalsing, MD 20+
R C Darling, MD 10+
David H Deaton, MD 10+
Randall Rich Demartino, MD 15+
Ralph W Denatale, MD 10+
Matthew J Eagleton, MD 15+
Rumi Faizer, MD 10+
Robert J Feezor, MD 10+
Julie Ann Freischlag, MD 10+
$10,000+
$10,000+
$10,000+
Dennis R Gable, MD 10+ $10,000+
Scott A Garner, MD 10+ $10,000+
Matthew G Garoufalis, DPM 10+
Patrick Geraghty, MD 10+
Philip P Goodney, MD 10+
Raul J Guzman, MD 10+
Vivienne J Halpern, MD 10+ $15,000+
David C Han, MD 10+
Kirk A Hance, MD 10+
Sachinder S Hans, MD 10+
Linda M Harris, MD 10+
Mounir J Haurani, MD 10+
Anil P Hingorani, MD 15+
Stephen J Hoenig, MD 15+
Jeffrey Jim, MD MPHS 10+
Brad L Johnson, MD 10+
Larry Wayne Kraiss, MD 15+
Timothy F Kresowik, MD 10+
Peter F Lawrence, MD 10+
Jason T Lee, MD 10+
Benjamin M. Lerner, MD 10+
Evan C Lipsitz, MD MBA 10+
Sean P Lyden, MD 15+
Robert G Molnar, MD
Raghu L Motaganahalli, MD
Leila Mureebe, MD
F Neville, MD
J Ozsvath, MD
E Parodi, MD
Darren B Schneider, MD
Murray L Shames, MD
Paula K Shireman, MD
William P Shutze, MD
Anton N Sidawy, MD MPH
J Sideman, MD
Jessica Simons, MD MPH
Matthew R Smeds, MD
J Smolock, MD
Sunita D Srivastava, MD
Gale L Tang, MD
Kevin E Taubman, MD
Robert K Thompson, MD
Boulos Toursarkissian, MD
Margaret C Tracci, MD JD
Gilbert R Upchurch Jr.
Grace J Wang
Vivienne J Halpern
Karen Woo
C. Raymond Workman
Robert M Zwolak
RETHINKING ANTIPLATELET AND ANTICOAGULANT USE IN PAD AFTER AQUATIC
By Killian Meara
During Thursday’s Hot Topics session, John Curci, MD, an associate professor of surgery at Washington University School of Medicine, discussed the changing landscape of long-term antiplatelet and anticoagulant use in the management of peripheral artery disease (PAD) in light of results from the AQUATIC trial.
The AQUATIC trial evaluated whether adding aspirin to direct oral anticoagulants improved cardiovascular and limb-related outcomes in high-risk vascular patients or if they actually increased bleeding risk without providing sufficient meaningful benefit.
Researchers enrolled over 800 patients across 51 institutions in France, focusing on those with advanced atherosclerotic disease, including PAD, carotid disease and coronary artery disease. All patients were being treated with long-term anticoagulation therapy, most commonly to reduce cardioembolic risk of atrial fibrillation.
Patients were randomized to continue aspirin therapy or receive a placebo in addition to their anticoagulant regimen.
Results showed that bleeding complications were more common in patients taking aspirin and anticoagulants, which Curci said was expected. “What wasn’t so obvious before the trial was that the patients who were on both an aspirin and a direct oral anticoagulant had more arterial occlusive events, either emboli, strokes, heart attacks or needed leg intervention than those on oral anticoagulation alone,” he said. “This was a remarkable finding.”
The mortality findings were particularly striking, Curci said. All-cause mortality reached 13.4% in patients who continued aspirin, compared to 8.4% in patients receiving placebo. This was among the reasons that the trial was stopped early for safety reasons.
VS@VAM BRIEFS
Compiled by Killian Meara
INNOVATION IN ACTION: HANDS-ON LEARNING AT VAM
EXPERIENCE INNOVATION IN ACTION AT VAM26 WITH TWO IMMERSIVE, hands-on learning destinations in the Exhibit Hall.
New this year, the Wound Care Pavilion offers attendees the chance to explore practical wound care techniques alongside expert faculty and industry partners. Building on concepts from the Wound Care Curriculum Online Module, the pavilion features interactive demonstrations focused on debridement, dressing and oxygen therapy, as well as opportunities to test products and engage directly with specialists. Open to all VAM26 attendees with no registration required, the pavilion will be open from 9:30 a.m.–2 p.m. in the Exhibit Hall.
Attendees can also step into the popular Touchpoint: Hands-On Simulation Lab, a dynamic space designed for interactive learning and live demonstrations of the latest vascular surgery devices, technologies and techniques. Featuring rotating 30-minute sessions from 9:30 a.m.-2 p.m., the SIM Lab allows participants to gain practical experience at their own pace — no pre-registration needed. Whether trying new tools or exploring emerging innovations, this high-energy experience is a must-visit for anyone looking to get hands-on at VAM26.
CATCH THE LAST DAY OF THE CAREER FAIR
DON’T MISS THE FINAL DAYOF THE CAREER FAIR TODAY FROM 9:30 a.m. to 2 p.m. on the second floor in Hall D, a prime destination for those seeking opportunities in vascular surgery. The Career Fair is complimentary for conference attendees and provides an effective opportunity for vascular surgery professionals to meet with potential employers in person.
The Career Fair can also help attendees build their professional networks through continued conversations with organization representatives after the event.
Access the 2026 SVS Career Fair Featured Employers Guide, which contains information on all the organizations recruiting vascular surgery professionals during and after the Career Fair. The guide offers attendees the opportunity to browse open positions, access career resources and establish connections to advance their careers.
Curci said the data has direct implications for long-term medical management in PAD patients, particularly as surgeons increasingly manage complex antiplatelet and anticoagulant regimens.“If a patient requires direct oral anticoagulation therapy, the addition of aspirin does not provide any additional benefit to reduce the risk of future coronary or lower extremity vascular events.”
The findings also raise broader questions about how antithrombotic strategies should be tailored across different conditions. Curci said that cerebrovascular disease may respond differently to anticoagulants and
antiplatelet therapies than coronary or lower extremity disease, suggesting future studies may need to evaluate these outcomes separately.
The study did not enroll patients who had a coronary intervention within six months prior to enrollment which leaves unanswered questions surrounding perioperative antithrombotic management, according to Curci. “For our PAD patients, we need to develop better evidence about antiplatelet and anticoagulant therapies in the periprocedural period to determine what is optimal, both in safety and in reducing the risks of future events.”
GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surfacea
Consult Instructions for Use eifu.goremedical.com
Refer to Instructions for Use at eifu.goremedical.com for a complete description of all applicable indications, warnings, precautions and contraindications for the markets where this product is available.
INDICATIONS FOR USE IN THE U.S.: The GORE® VIABAHN® Endoprosthesis with Heparin
Bioactive Surface is indicated for improving blood flow in patients with symptomatic peripheral arterial disease in superficial femoral artery de novo and restenotic lesions up to 270 mm in length with reference vessel diameters ranging from 4.0 – 7.5 mm. The GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surface is indicated for improving blood flow in patients with symptomatic peripheral arterial disease in superficial femoral artery in-stent restenotic lesions up to 270 mm in length with reference vessel diameters ranging from 4.0 – 6.5 mm. The GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surface is indicated for improving blood flow in patients with symptomatic peripheral arterial disease in iliac artery lesions up to 80 mm in length with reference vessel diameters ranging from 4.0 – 12 mm. The GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surface is also indicated for the treatment of stenosis or thrombotic occlusion at the venous anastomosis of synthetic arteriovenous (AV) access grafts. CONTRAINDICATIONS: The GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surface is contraindicated for non-compliant lesions where full expansion of an angioplasty balloon catheter was not achieved during pre-dilatation, or where lesions cannot be dilated sufficiently to allow passage of the delivery system. Do not use the GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surface in patients with known hypersensitivity to heparin, including those patients who have had a previous incident of Heparin-Induced Thrombocytopenia (HIT) type II.
GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surfacea,b
Evan Brownie, MD Murray, Utah
TRUSTED BY THOSE WHO TREAT COMPLEX CASES
Sharon Kiang, MD Loma Linda, California
Becker, MD Erie, Pennsylvania
In complex cases, experience and evidence make all the difference. Proven across SFA lesions with average lengths of 24 cm and 87% TASC C or D, the VIABAHN® Device demonstrated excellent patency and durability with 76% 5-year freedom from target lesion revascularization.1 Discover how practicing physicians apply these results to guide treatment of SFA disease. Watch the videos.
W. L. Gore & Associates, Inc. Flagstaff, Arizona 86004 goremedical.com
a As used by Gore, Heparin Bioactive Surface refers to Gore’s proprietary CBAS® Heparin Surface.
b Also referred to as the GORE® VIABAHN® Endoprosthesis with PROPATEN Bioactive Surface in some regions.
1. Iida O, Ohki T, Soga Y, et al. Five-year outcomes of the GORE VIABAHN Endoprosthesis for the treatment of complex femoropopliteal lesions from a Japanese post-market surveillance study. Vascular Medicine 2024;29(4):416-423
Please see accompanying prescribing information in this journal.
Products listed may not be available in all markets.