Journal of the Irish Dental Association


First tooth, first visit, zero cavities




EDITOR Professor Leo F.A. Stassen FRCS (I) FDSRCS MA FTCD FFSEM FFDRCSI FICD
DEPUTY EDITOR Dr Dermot Canavan BDentSc MGDS(Edin) MS(UCalif)
EDITORIAL BOARD Dr Iseult Bouarroudj BDS NUI
Dr Deirdre Coffey BDentSc Dip PCD(RCSI) MFD(RCSI)
Dr Michael Crowe BSc BDentSc DPDS (Bristol)
Dr Padhraig Fleming BDentSc (Hons) MSc PhD MOrth RCS FDS (Orth) RCS FHEA
Dr Peter Harrison BDentSc MFD DChDent
Dr Joe Hennessy Ba BDentSc MFD (RCSI)
DClinDent (TCD) MOrth (RCSEd) FFD (RCSI)
Dr Mark Kelly BA BDentSc
Professor Christopher D. Lynch BDS PhD MFDRCSI FDS (RestDent) RCSI FACD FHEA
Dr David McReynolds BA BDentSC MFDS RCSEd
Dr Ioannis Polyzois DMD PhD MDentCh MMedSc
Dr Ciara Scott BDS MFD MDentCh MOrth FFD (RCSI)

IDA PRESIDENT Dr PJ Byrne IDA CHIEF EXECUTIVE Fintan Hourihan CO-ORDINATOR Fionnuala O’Brien

See page 85
The Journal of the Irish Dental Association is the official publication of the Irish Dental Association The opinions expressed in the Journal are, however, those of the authors and cannot be construed as reflecting the Association’s views The editor reserves the right to edit all copy submitted to the Journal Publication of an advertisement does not necessarily imply that the IDA agrees with or supports the claims therein
For advice to authors, please see: www dentist ie/resources/jida/authors jsp
Published on behalf of the IDA by Think Media, 537 NCR, Dublin 1 T: +353 1 856 1166 www thinkmedia ie
MANAGING EDITOR Ann-Marie Hardiman ann-marie@thinkmedia ie JOURNALIST AND SUB-EDITOR Colm Quinn colm@thinkmedia ie ADVERTISING Paul O’Grady paul@thinkmedia ie DESIGN/LAYOUT Tony Byrne, Tom Cullen, Niamh Short


Total average net circulation 01/01/16 to 31/12/16: 3,227 copies per issue Circulated to all registered dentists in the Republic of Ireland and Northern Ireland



Pr o g r e s s i s p o s s i b l e
The DTBS is being improved, with credit due to our negotiating team, while we can look forward to a superb Annual Conference in Kilkenny.

The mood of relations between Government and the dental profession since the savage cuts to the State’s dental schemes has been dire The High Court may have found that the Government acted legally in its unilateral action to make the cuts, but that’s not to say they acted ethically or fairly Dentists felt aggrieved to the point of betrayal When the cuts were imposed, we felt that we were no longer partners in the provision of oral healthcare to the population; the Government made us feel that we were the underpaid and undervalued minions of an uncaring, unknowing State They may be strong words, but they reflect the very deep frustration of dental professionals at not being allowed to provide proper care for their patients This frustration spilled out at many meetings of the Association over recent years
It is this background that has made the progress made by our negotiating team at the table with officials from the Department of Social Protection so surprising The Association’s team of Drs Clodagh McAllister, John Nolan, Kieran O’Connor and Tom Rodgers, along with our executives Fintan Hourihan and Roisín Farrelly, has made it clear to members that they have experienced genuine engagement by the Department officials and believe significant progress has been made
Hard evidence of that progress was the extension of the Dental Treatment Benefits Scheme (DTBS) to cover the self-employed, which commenced last m o n t h F r o m O c t o b e r 2 0 1 7 ,
reintroduced for all eligible patients as a once annually closed grant-in-aid treatment The fee payable will be increased to ¤42 and the dentist will also be able to charge the patient up to ¤15 as an additional co-payment The protracted periodontal treatment will be reintroduced for certain patients Financial Emergency Measures in the Public Interest (FEMPI) cuts to the examination fee will be unwound as part of this process Full details can be read in the Members’ News section on page 85 The real message though is that, after years of deep frustration for us and pain for our patients, some
progress is being made Despite all the challenges of recent years, progress is possible and our negotiating team is making a difference
This is a bumper edition of the Journal There are several reasons, but the single biggest factor is the preview of the Annual Conference in Kilkenny in May The mixture of hands-on courses, scientific lectures, trade show, general presentations and social activity is compelling Readers will get all the details they need in this edition, along with a strong recommendation to attend If you need a little encouragement, there is no better introduction than our interview with Professor Peter Butler who will deliver the Journal lecture at the Conference Professor Butler’s work in facial reconstruction is world renowned and, of course, his late father Norman was one of our colleagues and Dean of the Dublin Dental School and Hospital
We are grateful to Drs Kirsten FitzGerald and Brett Duane and their colleagues, Drs Eleanor McGovern and Aifric Ní Chaollaí, for their two papers addressing the issue of infant oral health They stress the benefits of a visit to the dentist in the first year of life and present a review of evidence that demonstrates that such an early visit yields lasting dividends
Rotation of Editorial Board membership is very important for the development of the Journal – and I will return to this topic in the next edition For this edition one of our new Board members, Dr David McReynolds, has provided a detailed clinical feature on the use of a diagnostic method that can aid the operating dentist when multiple teeth or localised segments of the mouth require crowns Meanwhile, Dr Susie Sanderson of Dental Protection reminds us of our role in minimising the spread of antimicrobial resistance – we can’t just leave it up to the medical doctors

Dr PJ Byrne IDA President

IDA staff, officers and members have been working hard to plan the Association's future strategy

I was invited by the Canadian Dental Association to attend its Pacific Dental Conference in Vancouver in March (above) I met with the President, Dr Randall Croutze, President Elect Dr Larry Levin, and Executive Director Mr Claude Paul Boivin, and members of the Board I also had several interactions with Dr John O’Keeffe, Director, Knowledge Networks, and Canadian Dental Association, who was extremely helpful in setting up meetings and links for me Our thanks to John, who is a Dublin graduate from 1980 and a great ambassador for Ireland in Canada The quality of the scientific presentations was superb and the only difficulty was in making choices in terms of what to attend The hospitality of the Canadian Dental Association was outstanding and they were very complimentary of the quality and character of the Irish graduates who have gone to work in Canada via the reciprocal arrangements that came into being a few years ago We have a lot to learn from our mutual interactions
Strategic Council of the IDA think tank
Following the Board Executive and Council meetings on March 31, I organised a special meeting of the Council to look at many of the challenges that face us in our organisation I am delighted to say that the Council and officers of the B o a r d e n
representatives from the branches We had three main points for discussion: 1 CPD and its delivery nationally, regionally and locally; 2 branch structures; and, 3 communications with our membership I have to compliment all those who attended on a very lively and open discussion, and also on the multiplicity of concrete suggestions and ideas that flowed from the meeting I appreciate greatly the frank interactions and straight talking, in a very constructive and positive way, that occurred
Each of the 25 members around the table contributed at least three focused ideas and suggestions, which are being collated by our secretariat and will be very helpful in framing the way ahead for the next number of years I must give my appreciation to our CEO Fintan Hourihan, our assistant CEO Elaine Hughes, our Communications/Employment Officer Roisín Farrelly, and Dr Garry Heavey, Chair of the IDA CPD Committee, who all made short presentations, and our CPD events administrator Gráinne McQuaid I am very grateful to all of those involved for giving up their Saturday
Young and newly qualified graduates
As I discussed in my conference speeches in Galway last year I am very keen to
obtain early engagement with our undergraduate students in the dental schools These students are the lifeblood of the Association and every encouragement should be given to them to join Also, for newly qualified graduates we are going to increase the number of support documents available in order to help guide them through the first critical years of practice, which can be a daunting time This also applies to graduates coming from abroad or returning to Ireland following graduation abroad I had the opportunity to speak to the Cork graduates at their prize giving in UCC just before Christmas and also recently to the Dublin graduates, when they invited me to present on clinical photography in aid of their “DOVE” overseas initiative I look forward to seeing many more young undergraduates and newly qualified graduates attending our meetings and conferences
Sympathies
I would like both personally and on behalf of the Irish Dental Association to extend my condolences to Dr Celine Fenlon on the recent passing of her husband, Dr Billy Fenlon Our thoughts and sympathies are with Celine and her family I would also like to extend our sympathies to our CEO Fintan Hourihan on the recent loss of his mother
ASC Kilkenny
I encourage all members to attend our Annual Scientific Conference from May 11-13 in the Lyrath Hotel, Kilkenny There is an extremely exciting line-up of pre-conference courses, a very strong scientific programme and a number of workshops for both dentists and the dental team I would like to wish the President Elect Dr Robin Foyle every success with the meeting and I would ask our membership to support him in every way possible over his upcoming term as President Robin has been a stalwart of the Dental Association over so many years and I have no doubt that he will have a hugely successful Presidency
Thank you
I would like to extend my sincere thanks to the Officers of the Board of the Irish Dental Association, the members of the Council of the Irish Dental Union, the staff and members of the Irish Dental Association and my own staff for their support to me during my term as President I really appreciate the courtesy and support I experienced during my term It has been a pleasure to serve as President of the Irish Dental Association
Dear Editor,
Many thanks for publishing my letter in the JIDA in January 2017 My thanks also to Drs Hal Duncan and Padraig O'Reachtagain for replying with their letters in the February/March 2017 edition
In Dr O'Reachtagain's case, could the treatment be claimed for as "lancing an abscess"?
In reply to Dr Duncan, I must respectfully disagree that a similar amount of pus drainage through a tooth can be obtained with a suction tip or a syringe compared to that obtained by closed mouth suction Closed mouth suction is much more powerful, effective and quick
I was writing with a busy general dental practice in mind, where a few times per week, prompt professional treatment of acute pain or infection is rightly expected Patients must be "squeezed in" Drainage and a further appointment is preferable to antibiotics and a further appointment But the treatment must
The inaugural Oral & Maxillofacial Surgery Study Day, incorporating Ireland and Northern Ireland, was held at the RCSI on February 3 The study day covered many topics in oral and maxillofacial surgery, clinical audits and innovative research There was a focus on quality of healthcare, and a frank discussion on the management of oral and maxillofacial cases took place
All oral and maxillofacial units were represented, including St James’s Hospital, the Dublin Dental University Hospital, Galway University Hospital, Limerick University Hospital, Cork University Hospital, The Ulster Hospital and Altnagelvin Hospital Private practitioners from the Ulster Independent Clinic and the Mater Private Hospital, Cork, were also in attendance
Interesting talks were presented on the topics of the delivery of maxillofacial care in Dublin, facial infection rates in Northern Ireland, quality improvement in maxillofacial care and medicine-related osteonecrosis of the jaw A very interactive session was held on diagnostic and management dilemmas encountered in practice A frank discussion ensued between all clinicians in relation to the problems presented
Prizes were awarded for the best presentations given by NCHDs and the recipients were Dr Chris Wright from Altnagelvin Hospital on his presentation on 'BCC excision margins', and Dr David McGoldrick of St James’s Hospital for
APRIL
25 North Munster Branch meeting
Clinical quick tips: practical tips for everyday practice and AGM
MAY
11-13 Irish Dental Association
Lyrath Hotel, Kilkenny Annual Scientific Meeting
18 Irish Society of Dentistry for Children Portlaoise Heritage Hotel, Town Centre, Portlaoise Annual Scientific Meeting More details to follow so save the date
be simple and quick; otherwise, because of time constraints, it won't be used
Usually drainage can be got quickly by opening the chamber – often without local anaesthetic – and sucking
While I agree with Dr Duncan that endodontic treatment itself should be done under rubber dam, if some filing is needed to help drainage it could not be called real endodontic treatment: it is more akin to "lancing an abscess" One can tie a length of dental floss to the file for safety Protection of the airway is paramount of course, and contamination must be minimised with cotton rolls or other barriers and use of the surgery aspirator
If the cavity is then closed, cross-contamination must be minimal, and is irrelevant if extraction is planned
In addition to reducing antibiotic use, this treatment has the advantage of taking the emergency away so that decisions about the fate of the tooth can be calmly decided later
Yours sincerely,
Dr Frank McCrea

his paper entitled 'Significance of neutrophil to lymphocyte ratio as a prognostic aid in cancer and in particular its relationship to mouth cancer '
The organisers plan to hold this meeting on an annual basis, and would like to thank sponsors GS Medical, KD Surgical, Techno Surgical and Zimmer Biomet for their support
JUNE
23 Irish Society for Disability and Oral Health Marker Hotel, Dublin 2 Annual Conference – ‘Dental anxiety and phobia’
SEPTEMBER
15-16 IDENTEX Citywest Hotel, Dublin
OCTOBER
12-13 HSE Group of the IDA Hotel Kilkenny, Kilkenny Annual Seminar
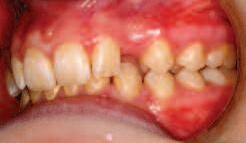
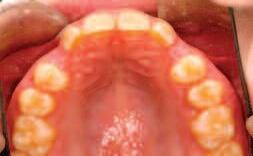
A 12-year-old girl presented complaining about ‘ gaps in front teeth’ On examination, the maxillary canines where found to be unerupted
1 Name three clinical processes you would carry out prior to radiographic examination that would help ascertain the position of the maxillary canines
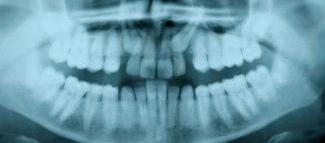
Radiographic tests consisted of a maxillary anterior occlusal and an orthopantomograph (OPG)
2 Name the technique used to radiographically locate an unerupted tooth?
3 What other radiographs can be used for this technique?
4 Where does this technique suggest the maxillary left and right canines are?
Answers on page 112

Your practice
Doyle Mahon has been appointed as the preferred insurance provider of the IDA The company states that in the first six weeks of its new scheme for IDA members and their staff, it has delivered savings in 98% of cases quoted on The company said it is delighted to have been selected as the approved general insurance provider to he members of the IDA What does this mean for you and your practice?
The company states its cover is made to measure with its tailored practice insurance policy, where dentists can obtain and pay for only the cover they
The HSE Group Annual Seminar will head to the sunny south east and the city of Kilkenny this year The event will take place on Thursday and Friday, October 12 and 13 at the Hotel Kilkenny A wide range of speakers will present
The Irish Dental Association, in conjunction with Wrigley Company Foundation, is delighted to announc range of dental support grants to fund worthwhile o healthcare projects around the country Applications ha been submitted and the winning applicants will b announced over the next few weeks
This is the second year of the initiative and last year fiv
need Doyle Mahon states that it has made savings for IDA members of 2025%, and up to 50% in some cases The company’s policies can include buildings, contents, liabilities, stock cover and more It offers a range of standard covers, including DAS Legal Expenses covered as standard It states that its policies are exclusively with A-rated insurers
Affinity scheme
There is an affinity scheme for the company’s dental clients, which offers significant discounts across all types of insurance the company provides, including: n home; n motor; and, n property owners’ insurance
on various topics over the two days with a full trade show present on Thursday This event is a must for any dentist employed by the HSE Put the dates in your diary now!


ery worthy oral healthcare projects were funded through he scheme ental support grants are available to help fund specific ommunity service projects with a focus on improving oral alth and educating participants in this area Up to seven ojects across the country will be funded, with one project eiving funding of ¤15,000, three receiving ¤5,000 and ee receiving ¤2,500 scheme was open to all IDA members to apply

For the fourth year running, the Irish Dental Association will partner with the Irish Dental Trade Association (IDTA) and will run hands-on courses, workshops and lectures as part of IDENTEX Over 60 trade stands will be present over Friday and Saturday, September 15 and 16, which members of the dental profession can visit free of charge To register for the IDENTEX trade show, log on to www idta eu More details on courses, including how to book, will be available shortly
The Annual Conference returns to the City of Tribes and the ever-popular Radisson Hotel in Galway in 2018 The event takes place from April 26-28
A practical hands-on course will take place on Friday, May 26 at the Clayton Hotel, Leopardstown, presented by Dr Pat Cleary, a specialist endodontist based in Dublin Places are limited so early booking is advised and bookings can be made through IDA House

(1986-2016)
Quintess Denta is hosting a full-day course ‘Introducing the Neodent implant system’ on Friday, April 21 in Belfast Castle Neodent was established over 20 years ago and is currently present in more than 20 countries Quintess Denta states there is an incredible line-up of speakers, all with years of implantology experience, including Dr Joe Bhatt, who is a specialist in prosthodontics and oral surgery, and John Wibberley, an expert in implantology with a passion for dental technology Apart from educational talks, there will be a hands-on element, which will give delegates the opportunity to see the benefits of the Neodent system first hand There is also a focus on digital workflow and the future of technology used in the dental industry The course is free but spaces are limited If you would like to attend, contact Quintess Denta online or by phone
The South Eastern Branch recently had a very successful Annual Scientific Day at the Tower Hotel, Waterford A full trade show was present and over 50 delegates were in attendance There were some very interesting topics discussed on the day, including surgical extractions, endodontics, trauma, and facial pain
n Leading provider of advanced CAD/CAM and 5+1 Axis Milling using Zirkonzahn and Sirona technology.
n E-Max, Zirconia, PFM & simple to complex implant solutions
n We accept and process both conventional and digital impressions.
n We offer a reliable 5 days-a-week service with daily telephone and on-site support to our clients
Eastpoint Business Park • Dublin Road • Loughrea • Co Galway Tel: 091-880


announce the Awards
INSET: The 2016 winner, Dr Daniel Collins, with Dr Marie O’Neill and, right, Eilis Tobin of GSK, who sponsor the event
Will you be Ireland's Sensitive Dentist of the Year 2017? The gala awards ceremony will take place at the glamorous Concert Hall at Dublin’s RDS on Saturday December 2 next Make sure you are nominated!
Any patient can nominate their dentist for the Award either online at www sensodynesensitivedentist ie, or on the postcards available from GSK at their stand in Kilkenny at the Annual Conference
This year we are delighted to announce that we will once again have a second award for Sensitive Dental Team of the Year


Pioneering surgeon Professor Peter Butler will address the IDA's Annual Conference in May. He spoke to the Journal about his cutting-edge work in facial reconstruction.

Peter Butler sees his career as very much part of a continuum that goes back through the centuries as extraordinary surgeons have attempted to achieve a 'normal' appearance for patients suffering congenital illnesses, and for those who were victims of terrible trauma He mentions the Italian surgeon Gaspare Tagliacozzi, who carried out nasal reconstructions in the 1500s, and a visit to the Queen Victoria Hospital in East Grinstead as a junior doctor, which had a significant impact on his own interest in the subject In East Grinstead during and after World War II, Sir Archibald McIndoe carried on the extraordinary work begun by his cousin Sir Harold Gillies during World War I, using tubed pedicles (a reconstructive technique in which the skin and soft tissue is formed into a tubular pedicle and moved from the source to the target site by anchoring at both ends, significantly reducing infection) to rebuild the faces of badly wounded and burned soldiers The techniques and technology are better these days, but the processes are essentially the same: "At that time, the outcomes took a long time, but we ' re better at moving tissues now "
These days, as Professor of Plastic and Reconstructive Surgery at the Royal Free Hospital and University College London (UCL), Peter works to advance his specialty case by case: "We take on cases where there isn't a solution, in conditions where there isn't really a treatment option"
Many of his patients suffer from scleroderma, a chronic autoimmune condition that causes thickening or hardening of the skin and internal organs Peter sees patients who have developed a condition called microstomia, where tissues around the mouth tighten until the patient cannot speak properly, or access dental care The immunosuppressive drugs these patients take make them d
reconstructive methodology: "We've come up with an intervention which we ' ve found reverses the fibrosis so they get back oral continence – their speech improves, tissues feel less tight and the dentist can do dental work"
Peter's other large caseload consists of patients who are post resection for head and neck cancer He has developed treatments in secondary facial r e c o

treatment, but still have significant disfigurement and d
reconstruction that's left them with a large hole in their face, or where the tissue used – because it has been taken from the abdomen or back – is very different to facial skin It's pigmented differently, it doesn’t move,
socially isolated than they were before I use all of our techniques to modify their own tissues and import tissues to reconstruct the defect so that they get a more normal-looking face
experience another painful and debilitating problem, a fibrosis or scarring that restricts movement of the mouth and neck This time, Peter s solution involves stem cells: "We've developed a stem cell therapy, which we now do using ultrasound-guided needle into the affected tissues, and we ' ve found significant reversal of the radiotherapy damage
This therapy is forming a major strand of Peter's research, another significant aspect of his work: "We're trying to figure out why and how this works, because obviously it would lead on to a new drug development We already have a human effect, so that's a big advantage The disadvantage is that we have to reverse engineer it to find out why it works"
Science fiction into science fact
Some years ago, extraordinary images emerged of a mouse with an ear growing from its back Peter was part of the group that carried out this work, and tissue engineering remains a vital part of his research into better reconstructive techniques: "We've just won an award for an ear reconstructive methodology using that technology and we have a potential clinical trial to start using a p o l y m e r - b a s e d r e c o n s t r u c t i v e m e t h o d o l o g y W e ' r e a l s o l o o k i n g a t a combination of that with tissue engineering and prefabrication to recreate jaws and mandibles, as well as the central aesthetic unit – the nose and the nasal ethmoid
“ E v e n m i n o r d i s f i g u r e m e n t c a n c a u s e s i g n i f i c a n t p s y
a par tner ship; I usually get the psychologist to see the patient with me so that we work together with the patient, and then the psychology unit helps me to determine when we do the
inter vention.”
"We've already done cases where we ' ve reconstructed mandibles in the leg
This is an established technique but we ' ve moved it on a bit to make mucosa as well as bone We're working with dentists, using preoperative planning, constructing the implants in the fibula before we transfer them into the mouth Before, you would bring the fibula up into the mouth and then, when everything settled down about six months later, you would come back and put the implants in it We've now worked out that you can do the whole lot in the leg before it s transferred
Peter is married to the journalist and broadcaster Annabel Heseltine, and they have four children: twins Mungo and Isabella (14), Rafferty (13) and Monty (10) Peter returns to Ireland every few months to visit family His father Norman passed away in January 2016, but with his now-retired mum and a brother and sister still based in Dublin, there s always plenty to come home to He also tries to get home for the occasional rugby match, although that's not possible this year When he has time away from work, he has an unlikely hobby – salmon fishing: "I particularly like spey casting It s like doing yoga or a mantra – you get totally absorbed There s an art to it and you get a lot of practice because you have to cast every two to three steps Precision is key – and you can see the results of your work pretty instantaneously"
This is a significant advance in terms of the patient's dental rehabilitation: "When we transferred [the bone] before, we detached it from its blood supply and re-attached it in the neck, which is a pretty standard technique, but the flap of skin we brought with it was extremely thick and it was very difficult to get the abutment to work Now we don't even transfer the skin We prefabricate the mucosa in the leg, as well as having the implant in the bone, before we transfer"
This extraordinary and complex surgery is done in collaboration with dentists and maxillofacial surgeons, and Peter says it's the combination of all three skillsets that makes it possible The team has used this approach in two cases so far, and is about to carry out a total nasal reconstruction using the techniques learned: "Each technique gives you a thought process as to other techniques Each one builds on the other, which is the way I like surgery to evolve"
Mind over matter
Of course, at the centre of these revolutionary techniques are the patients, many of whom have been through many surgeries and are still suffering the mental distress and social exclusion caused by facial disfigurement Peter is acutely aware of this, and has built an embedded psychological service into his unit: "We have three psychologists now and when I started off we had none Even minor disfigurement can cause significant psychological distress It's a partnership; I usually get the psychologist to see the patient with me so that we work together with the patient, and then the psychology unit helps me to determine when we do the intervention"
It's also about managing patients' expectations of life after surgery: "Every time you do anything to somebody's face they go through a period of readjustment in regards to their self-identity, and everybody is different in how we handle this It s very important to work out who fits in a high-risk or a lowrisk category, or where the intervention might help"
All about the face
Peter is perhaps best known for his work in the area of facial transplantation He was first surgeon to write about the possibility of full facial transplantation in The Lancet in 2002, and received ethical approval for the procedure in 2006, but while transplants have taken place in other countries, no suitable case has arisen in the UK Peter is still very much involved, but acknowledges
Peter s mother Ursula is a retired pharmacist, while his late father, Norman, was an eminent dentist and Dean of the School of Dentistry in TCD However, it was his mother's brother, a doctor, who inspired him on his own career path He completed his initial studies at the Royal College of Surgeons in Ireland in 1987, followed by internships at the Richmond and Beaumont Hospitals in Dublin, and surgical training in Dublin and Drogheda He had already developed a strong interest in plastic surgery and facial reconstruction, and travelled to Harvard to complete a fellowship, followed by some time back in Dublin before he made the move to London, where he has worked ever since
that the road has been anything but straightforward: "We had a live programme for two years, but out of about 120 potential donors for the recipients we only got three offers, none of which matched It became increasingly obvious that it was going to be very difficult to deliver something like this in the UK"
One major issue is an understandable reluctance on the part of families to donate facial tissue Research by Peter’s team has shown that for internal organs, even where a patient has previously registered as a donor, families gave consent for donation in only 50% of cases When it comes to facial and corneal tissue, the numbers are far lower: 10% at most Another significant issue is immunosuppression, which is known to shorten patients' lives, and for which no satisfactory solution has yet been found: "We haven't given up We have two patients still interested, but the difficulty for me is if I make them live patients in a process, will I get them a donor?"
Peter is philosophical about the experience, which included some fairly intense media attention, and robust discussions about the ethics of the operation: "I suppose I should have been [disappointed] but I wasn't I ran into quite powerful individuals in the surgical field who tried to stop it, but I equally ran into other quite well-known figures who were supportive I also did lots of radio and television, and the different points of view were very interesting None of them were wrong – they were just different It was a very interesting experience"
Of course, the long process has also been difficult for those patients who w i s h e d t o b e c a n d i d a t e s f o r t h e s u r g e
developments in techniques and technology, his team has been able to help many of them: "For patients where half or three-quarters of their face has been damaged, we have applied the reconstructive techniques I now use in the head and neck cancer patients We've got them involved with a group called Changing Faces, and have worked hard to support them, and so a lot of people I originally thought would be candidates have decided not to because they got on so well in the other things we ' ve put in place That's a good result"
And the research goes on, not just in the UK, but with partners all over the world: "Obviously the biggest challenge is to tissue engineer a face, which I still think is quite difficult because facial skin is so difficult, but we can reconstruct mucosa, cartilage, bone, fat tissue, muscle – we can do quite a lot I do a lot of collaborative work with institutions in the United States and Europe – we collaborate quite freely"
Working almost entirely within the NHS, Peter gets referrals from all over the UK, and occasionally further afield This means that patients can wait up to a year to see him, and he admits that waiting lists and limited resources are an ongoing issue Another surgeon might pine for more time, money or resources, but for Peter, necessity is the mother of invention: "I always find a way around a problem Sure, I ve gone to some research institutions in the US where they have such beautiful facilities in comparison to what we have, and it would be great to be so well resourced We achieve quite a lot on a very small budget I wouldn't mind if I had the facilities they do and the resources to go with it, but you use what you ve got in front of you
"The one thing I loved about Harvard was the can-do attitude, that failure is part of a process, not the end point, whereas unfortunately on this side of the pond if you fail you ' re in trouble"
He knows that not progressing to full facial transplant in the UK would be
seen by some as a failure, but he sees the good that has come and continues to come from the work: "I now attract very bright students because of the previous work, and that's really interesting – building the next generation of surgeons "
reconstructive surgery, which explores all of the different approaches, including facial transplantation, tissue engineering, nanotechnology and stem cell therapy, that could potentially be applied to a reconstructive process The work they do is potentially for replacement of any tissue, but for Peter it's all about the face and always has been: "I find it really amazing It's an amazing organ I keep coming back to it I go off and do other areas but always come back to the face"
The reasons for this fascination go right back to the beginning of his career:
"Throughout my journey, the most impacting patients I've met are the ones that have had significant facial injuries and what they've had to go through, and also how poor the end point is with the methodologies we have available I came across a patient when I was training as an SHO in St James's in Dublin who had a pan-facial burn – the whole face had gone, and the chest and a bit of the hand He had scar tissue that was dragging down his lips so he dribbled all the time, and he couldn't look up because his neck had contracted He was 19: he wanted to go to university, get married The techniques that we had at the time, which are actually techniques that we still use – skin grafts and flaps – really weren't going to restore him to normal
"There's a massive unmet need When you walk out the door in the morning, when we look at anybody, we look at the face first It's the first thing, unfortunately, that society judges you by It's a real tough one for the patient with facial disfigurement to walk out the door"
This determination to meet the unmet need of facially disfigured patients is what continues to drive him to take not so much a step-by-step approach as what he calls " a multi-faceted attack", coming at the problem from a number of angles: "Even facial transplant doesn't meet the need The idea was to replace like with like and it's still not quite there"
He will continue to attack the problems, and to develop the next generation of new technologies, until he can meet all of his patients' needs: "Unless you do it you'll never know"
Peter's team has just received an endowment that will enable them to move substantially forward with a project that brings all of these research interests together, the Charles Wolfson Centre for Reconstructive Surgery: "The idea is to try and bring together all the surgical disciplines in reconstructive surgery –plastics, maxillofacial, breast, a whole range of reconstructive techniques –and improve them, to produce clinical trials and evidence around the intervention of these new techniques"
Ann-Marie Hardiman
Managing Editor
with Think
Media,
with an interest in further education and CPD

Dentists have a large role to play in minimising the spread of antimicrobial resistance and can’t leave it up to medical doctors and vets to tackle the issue
Antimicrobial resistance (AMR) must surely be a subject that is now familiar to us all It is considered such an urgent threat to human health because there is an emerging risk to all mankind Because of the increasing ineffectiveness of antimicrobial drugs, common and life-threatening infections will become more difficult to treat successfully, with a significant potential for surgical and medical interventions to become impossible
It’s tempting to dismiss AMR as a problem driven primarily by agriculture and
Dr Susie Sanderson
OBE BDS FDSRCS(Eng) FFGDP(UK) LLM
Susie works for Dental Protection as a Dento-legal Adviser She will speak at the IDA Conference 2017

general medical practice In fact, in Europe and across the world, a “ one health” approach to appropriate antibiotic use is being promoted, recognising the intimate relationships between human and animal health Significant bodies such as the World Health Organisation and the European Commission, along with national governments,1 are driving strategic collaborations between human and animal healthcare professionals and the public 2
Why is it dentistry’s problem?
It turns out, counterintuitively perhaps, that primary care dentistry is a significant player, responsible for up to 10% of antibiotic prescribing in Europe Arguably dentistry, consequently, has a duty to view AMR with an honest and critical eye In Ireland, evidence-based guidance developed by the Dental Antibiotic Stewardship Working Group, a subcommittee of the Strategy for the control of Antimicrobial Resistance in Ireland (SARI) National Committee, is available to assist with the indications for the prescribing of antimicrobials 3 The choice of antibiotic is largely made on empirical terms in dentistry, and the
first- and second-line recommendations in published guidance are made with the risks of AMR in mind Guidelines are there to augment clinical judgement but a prudent practitioner would make sure that they were able to justify prescribing outside published guidelines, particularly in the event of a subsequently raised concern about their care of a patient
Relatively recent research in Wales looking at primary care dentistry revealed that it was likely that between 70 and 81% of prescribing did not follow published recommendations The reasons were described as multifactorial, some needing further investigation Indeed, in dentistry, we have notable challenges to responsible prescribing Unfortunately, many of our patients will ask us to prescribe antibiotics inappropriately Dental pain is primarily an inflammatory condition and usually best treated by a clinical intervention supported with effective analgesia Consequently, being offered the more appropriate options of, for example, an extraction or extirpation of an inflamed pulp may not go down so well with treatment-averse individuals
Planning for the unpredictable
Equally, our own experience tells us that patients frequently present with dental pain as an unscheduled emergency during a busy day, with little time available to provide the correct clinical intervention Unfortunately, tempting though it is when there is no time to provide the right care, we know that issuing an antibiotic prescription will not cure a hyperaemic pulp and the patient will be on the doorstep the following day after a sleepless night with no relief from their pain The cycle of unscheduled attendance is perpetuated as a constant disruption to the day’s organisation We really do need to take the time to listen, investigate, make the diagnosis, communicate effectively to secure valid consent for appropriate treatment and then carry it out That’s a long list of things to do when there is only five minutes between other patients to achieve it! But this is surely the best example of a situation where “do it once, do it right” is the mantra that creates winners all round
Use audit to advantage
An audit and feedback approach to raising awareness of appropriate prescribing and improving compliance with guidelines has been found to be successful in centres in the UK 4 5 A suitably designed audit6 will also provide data on the frequency with which patients present on an unscheduled basis with a condition that requires a clinical intervention and the nature of that intervention These details can inform the structure of an appointment system that can factor into the clinician’s schedule a suitable opportunity for the investigation of a diagnosis and active treatment without the risk of wasted surgery time
It’s difficult to imagine a world without effective antibiotics – on average, they add 20 years to each person’s life The serious risk, however, of a postantibiotic era is not the stuff of science fiction Regulatory bodies and litigation lawyers are paying far more attention to our prescribing practices, so it’s in everyone’s interests to get them right Most importantly, mixed messages are
We can counter the rise of antimicrobial resistance by: n surveillance – of, for example, prescribing patterns, emerging resistance; n prevention of infection; n preserving effectiveness of existing drugs; and, n promotion of new antimicrobial agents and diagnostic technologies
not helpful We can help our medical and veterinary colleagues to reinforce their strapline: “antibiotics don’t cure coughs, colds and sore throats”, although it would be good if our patients’ doctors also follow our version: “antibiotics don’t cure toothache”, which has a certain ring to it!
References
1 UK government five-year plan, 2013-2018 Available from: https://www gov uk/ government/uploads/system/uploads/attachment data/file/244058/20130902 U K 5 year AMR strategy pdf
2 European Commission five-year plan, 2011 Available from: http://ec europa eu/ dgs/health food-safety/docs/communication amr 2011 748 en pdf
3 D e n t a l A n t i b i o t i c S t e w a r d s h i p W o r k i n g G r o u p A
http://www hse ie/eng/services/list /2/gp/Antibiotic-Prescribing/Conditions-andTreatments/Dental/ Accessed March 2017
4 Prior, M , et al Evaluating an audit and feedback intervention for reducing antibiotic prescribing behaviour in general dental practice (the RAPiD trial): a partial factorial cluster randomised trial protocol Implement Sci 2014; 24; 9: 50
5 RAPiD audit and feedback trial summary (Healthcare Improvement Scotland third annual symposium) Available from: http://www healthcareimprovementscotland org/ news and events/events/3rd annual research symposium/poster 7 aspx
6 http://www fgdp org uk/publications/antibiotic-stewardship ashx; www bda org/amr

Dental Care Ireland, an Irish-owned dental group, has acquired 11 dental practices nationwide since 2015 Founded by Colm Davitt, former CEO of Euromedic Ireland, and his brother, dentist Dr Kieran Davitt, the group states that its aim is to acquire long-established, trusted and high-quality dental practices, with a view to helping them reach their full potential and ensuring a high-level service for patients
The company states that its business model frees principal dentists from administrative burden, allowing them to focus on clinical dentistry Dental Care Ireland upgrades the practices’ facilities and technology, and provides administrative support The business model may be of interest to dentists in the latter stages of their careers
Colm Davitt, Chief Executive, said: “What sets us apart is the fact that all of our dentists are established, local practitioners with loyal patient bases We add to that level of quality by ensuring the latest facilities for patients, introducing new services and providing added convenience in terms of both local access and better opening hours”
Following a review of its 2016 claims, Omega Financial Management has announced that 16 66% of its dentist clients became unwell and received an illness benefit last year to cover their lost income Proportionately speaking, this rate is a lot higher than the GP/consultant group average, where one in eight of the company’s clients made a claim in 2016 Dentists are the company’s largest day one income protection policy holder group As a predominantly self-employed profession, most dentists are not entitled to State illness cover, so there are no safety nets if faced with a few weeks, months or longer out of work Income protection can ensure a replacement income Many take it out as a precaution, assuming that they are unlikely to ever need it
The breakdown of illnesses shows that about half of all dentists’ claims related to short-term conditions such as infections, viruses and gastrointestinal illnesses Ranging from one day to a few weeks, these types of claims can occur multiple times over the course of the year, particularly given the close proximity to patients during cold and flu season Overall, this can add up to a month or more in lost income
The ability to predict the future direction of investment markets is important for pension providers. However, the reality is that nobody has perfect foresight and unexpected events such as the election of Donald Trump and Brexit can happen
Market returns are out of dentists’ control but you do have some control over the amount you will pay in fees to providers to manage your pension, and these can make a real difference to returns over time All else being equal, the lower the fees are, the higher your return will be. Before making any pension commitments, find out how much you will be paying
Paul King of the Irish Dentists’ Approved Retirement Savings scheme said: “We are not simply advocating picking the lowest cost investments We are saying that paying attention to fees is important and it is something that can have a real impact on investment outcomes”

Musculoskeletal conditions accounted for 21% of all claims, with back pain/issues forming the majority of complaints in this category In some circumstances, these cases resolved within a week or two; however, a number were severe enough to keep dentists from work for a couple of months or more
Accidents and broken limbs account for 10% of dental claims, with a variety of fractures keeping claimants out of work for up to three months Figure 1 shows a breakdown of claims by category
Dental claimant profiles
Some 59% of Omega’s dental claimants last year were female The company s a i
pregnancy-related conditions The average age of a dental claimant was 41, more or less in line with the total average age of 40
The company states that 100% of its day one income protection claims were paid and that this has been the case every year since the policy was introduced in Ireland It goes on to state that claimants were paid on a weekly basis until such time that they could return to work, and that this was all on the basis that they submitted a one-page claims form
Table 1 shows a sample of dental claims the provider received in 2016, their duration and benefits paid


Kilkenny is home to the 2017 IDA Annual Conference and here we outline some of the speakers and topics which will be on offer in the Marble City

This year’s IDA Annual Conference takes place from May 11-13 at the Lyrath Hotel, Kilkenny The Conference is entitled ‘Satisfy Your Curiosity’ and features many opportunities to do just that
There will be new features and old favourites Delegates will see the new Dental Hub, which will feature short 15-minute lectures designed to allow them to quickly pick up a skill to bring back to their practice
As usual, parallel sessions will run on the Friday and Saturday offering a wide range of topics to suit anyone’s interest or area of practice The separate nurses’ programme returns this year and will take place on Saturday Dental hygienists are welcome to attend any of the sessions on Friday and Saturday
The events commence with the Pre-Conference Programme on the Thursday, and wouldn’t be complete without a packed social programme and a bustling trade show
The IDU Annual General Meeting will take place at 6 00pm on Thursday, directly followed by that of the IDA
Pre-Conference Programme
The Pre-Conference Programme on Thursday is almost as packed as the Conference days It will feature a hands-on course from Dr James Kessler and full-day lectures from periodontist Dr Kirk Pasquinelli and endodontist Dr Stephen Buchanan Dr Kessler will guide delegates on planning and delivering
Colm Quinn Journalist with Think Media

predictable bonded-ceramic restorations Dr Pasquinelli will look at the aesthetics of the periodontium, while Dr Buchanan will speak on how in endodontics, everything has changed except the anatomy
There will also be a number of half-day clinical workshops designed to help dentists make sure they are ready if an inspector comes to the door These will run in the morning and the afternoon and will cover the topics of: infection prevention and control; water quality including amalgam separators; health and safety at work, sharps regulations; and, radiation licensing There will also be the opportunity to attend a workshop in medical emergencies
Lecture programme
There will be two programmes running simultaneously on Friday and Saturday, with a whole host of topics and speakers to choose from Kicking things off on Friday, James Kessler will look at new restorative materials through the lens of proven principles John Walsh will explore whether interceptive orthodontic treatment is worthwhile Kirk Pasquinelli will share his tips on how to make an implant-supported crown look like a real tooth
Former IDA President Anne Twomey hopes to prepare dentists for the dental tsunami in nursing homes, while outgoing President PJ Byrne will give an update on IDA governance
The dental team programme will take place from 2 00pm-3 30pm before both programmes join together for the last two lectures of the day
Raj Rattan will give his ten critical success factors in general dental practice, which will be followed by a talk by world-renowned surgeon Peter Butler about the fascinating world of facial reconstruction
Everything starts all over again at 10 00am on Saturday Eleanor McGovern will talk about the benefits of the first dental visit taking place when the first tooth appears Pat Ormond will give advice on what to look for when trying to spot oral cancer Just before lunch, nutritionist Modi Mwatsama will present on the options available for reducing our sugar intake
Thursday, May 11
Dr Stephen Buchanan
T
California to deliver a full-day lecture on the art of endodontics He will explain how that n o m a t t e r w h a t n e w t e c h n o l o g y i s introduced, the anatomy of the tooth will never change and the principles of treatment remain the same The lecture will feature HD videos of Dr Buchanan’s real-life procedures

In the afternoon, Stephen Buchanan will examine what new technology is available in endodontics Both programmes will again merge at the end of Saturday for the final lecture of the Conference on the transition to full dentures, delivered by Ed Cotter
Henry Schein Ireland states that not only can digitisation help to make the practice of dentistry more streamlined and hence more cost and time effective, it can also make it more exciting

The company said that: “Through all our combined years in the dental world we have seen some incredible changes and challenges that as an industry we have overcome together Recently it has been highlighted that another industrial revolution is taking place: the digitisation of our industry”
Continuing, the company said dentistry has a new challenge on its hands: “The continual advances of CAD/CAM, 3D OPGs, chairside milling and digital impressions will once again challenge us all to look at what is best not only for the patient but also for the dental practice”
The company believes it is uniquely placed to offer help, guidance and support to anyone who is ready to embrace digitisation
10 00am – 10 45am Social media and the dental practice Dental Protection
10 45am – 11 15am TEA/COFFEE
11 15am – 12 00pm
Assisting the oral surgeon
Justin Moloney
12 00pm – 12 45pm Infection control
Siobhan Carrigan
12 45pm – 1 45pm LUNCH
1 45pm – 2 30pm
2 30pm – 3 30pm
Behavioural management and the role of the dental nurse
John Walsh
Dealing with the older patient
Anne Twomey

Dental Hub
A new feature of the Conference this year is the Dental Hub The idea is that short, informal educational sessions will be given where delegates can sit in and learn some practical ideas in a short space of time Delegates can pop into whatever 15-minute session they want, picking from a wide choice
FRIDAY
10 30am – 10 45am 5 top tips for maintaining equipment
11 30am – 11 45am Oral hygiene tips for your patients
12 15pm – 12 30pm Amalgam separation - Minamata
12 45pm – 1 00pm Handpiece maintenance
DMI is launching a new product guide at IDA Annual Conference 2017 The company states that it is the largest and most comprehensive to date, and that the new layout and index make it easier for dentists to fin the products they need
According to the company, the guide includes a f
SATURDAY
10 30am – 10 45am Hand hygiene in dentistry
11 30am – 11 45am What should be included in my emergency drug kit?
12 15pm – 12 30pm Dental Protection presentation
2 00pm – 2 15pm An oral cancer exam
2 45pm – 3 00pm Getting the most from your intra-oral x-rays


ge of the latest consumable products from ding manufacturers DMI states that a de range of dental equipment covering very aspect of a dentist’s requirements can e found in the publication

A free copy of the DMI product guide is available from the company Visit DMI at the IDA Annual Conference

Friday, May 12
Prof. Peter Butler

Renowned surgeon Professor Peter Butler will take delegates into the fascinating world of facial reconstruction He will speak about what is possible now and how that is being pushed even further all the time

NSK states that its new Ti-Max Z Air turbine series includes one of the most powerful air turbines available to dental professionals, the Z900L The company goes on to say the device has a small head positioned at an optimal angle to improve operational visibility and access
One dentist, Patrick Rea of the Sandown Dental and Implant Clinic, Belfast, was loaned the turbine for a ten-day trial in his surgery and said: “This gave

For a demo of the benefits of the restorative digital ecosystem, please visit our stand B10 & B11 at the IDA Conference or contact Marie Amond on 086 8261210 www.itero.com
Social programme
As usual, there will be a wide social programme on offer for delegates to mingle, network and compete The President’s Golf Competition will take place on Thursday, May 11 from 12 noon Anyone due to attend a
Wednesday afternoon

me the opportunity to see how the turbine handled in my own environment and I was very impressed as it performed well in a variety of clinical situations, was lightweight and easy to handle even for lengthy periods of time I have now purchased several”
NSK is offering an extended three-year warranty on the range To find out more and view the range of offers available, visit the NSK stand


Don't miss…
Saturday, May 13
Modi Mwatsama
T
w a y policy and advocacy can reduce ou sugar intake She will look at th drivers of consumption and trend h
some of the opportunities for an
outline some recent success in the UK

Conference delegates, accompanying persons and all trade exhibitors are welcome to play but only registered delegates are eligible to play for the President’s Prize Green fees are ¤65 per person
After all the putts are sunk, back at the Lyrath the trade show opening party will be officially opened by newly-inaugurated IDA President, Dr Robin Foyle at 8 00pm All delegates and trade sponsors are invited to intend, with fun, music and drinks for all
The black-tie Annual Dinner will take place on Friday at 7 00pm A drinks reception will start the evening, with dinner and entertainment following Tickets are ¤85 and are available from IDA House All dental team members, trade members and friends are welcome to attend
Dr Joe Moloney Award
The winner of the Dr Joe Moloney Award is chosen by delegates, who nominate and vote for their favourite lecturer at the Conference The award is kindly sponsored by the Dental Health Foundation and will be selected on the final day of the Conference
Dr Tony Costello Memorial Award

Last year DDUH students Claire McGleenon (left) and Safoora Shahab received the Costello Medal from Dr PJ Byrne, President of the IDA
This is Irish dental students’ chance to showcase what fresh thinking they have to offer the profession Each of the three dental schools can enter a team of two people to give a table demonstration or poster presentation of not more than ten minutes The IDA will provide a grant for each demonstration


Dentsply Sirona has added two new products to its range The company says it will soon be bringing Celtra Press, a high-strength, glass, zirconia-reinforced lithium silicate material to the Irish market
It states that the product is good aesthetically: “Th
crystalline structure and high glass content, provides
properties” Celtra Press ingots, Celtra Ceram, and Celtra Press Investment material will be available later t year
Septodont states that its introduction of Biodentine to the UK dental market in 2009 helped to boost the emergence of minimally invasive dentistry Using similar technology, BioRoot RCS was launched in 2016 to aid situations where root canal treatment is the only option The company states that the patented tricalcium silicate technology means that both products have outstanding sealing properties with no shrinkage, antimicrobial properties, and that they promote cell regeneration
According to the company, in the case of Biodentine, this means that more

From left: Anthony Markowski; Thomas Brosnan; and, Terence Houlihan of Promed celebrate the win
Kerry-based medical company Promed was officially recognised as one of the best workplaces in Ireland in February 2017 Great Place to Work publishes three lists each year: one for large workplaces, one for medium-sized companies and one for small workplaces Promed came out on top in the small workplaces category The company previously achieved first place in 2015 Companies are assessed based on employee surveys and a ‘culture audit’ carried out by Great Place to Work
The company also has another new product available for dentists Atlantis CustomBase is a solution for patient-specific, single-tooth restorations The company states that the product eliminates “the time needed for waxing, casting and grinding, increasing predictability of the final outcome and ultimately helping to improve efficiency and profitability”
Dentsply also states: “CustomBase solutions offer technicians total peace of mind should there ever be a problem as all crowns and abutments are covered by a comprehensive Atlantis 10-year warranty and expert customer support”
teeth can be saved as it supports pulp healing and trigg dentine mineralisation It goes on to state that Bioroot RCS gives a superior seal, without the need to use warm techniques, and that the release of calcium h y d r o x i d e p r e v e n t s b a c t e r i a l
manufacturer also states that BioRoot RCS support peri-apical healing, thus reducing the risk of RCT failure
To find out more about these two products, as well as Septodont’s anaesthetics and needlestick injury prevention device, Ultra Safety Plus, visit Septodont at the IDA Conference

And a great guy to work for… med has appointed a w managing director, ry Russell (left) and es that his appointm n
lthcare career has spanned 20 years and he s Promed directly from Boston, USA, where
Surgical, and led it as its chief executive for r eight years
vious to this he worked for Johnson & nson and Boston Scientific Promed states he will continue to build on its reputation within the primary care sector He said one of his main goals will be to bring his key learnings from the international healthcare market to the Irish primary care sector
Commenting, he said: “Patients, health providers and industry leaders cannot wait for the kind of primary healthcare system we all wish to see Irish patients deserve the same level of care as those in North America, Sweden, Holland and other such world-class providers”

GOLD SPONSOR
G1 GSK
G3 DMI
G4 Colgate
SILVER SPONSOR
S3+S4 Swordfish Medical
S5 Dentsply Sirona
S6 Johnson and Johnson
S7 Dentawealth
S8 Coltene
S9 Wrigley
BRONZE SPONSOR
B1 Henry Schein
B2 Pamex Ltd
B3 Southern Cross Dental
B4 Cerezen
B5 Medaccount Services
B6 Zirkonzahn
B7 Nobel Biocare
B8 Zimmer Biomet
B10+B11 Promed
Coltene states it is investing in its team by recruiting Nichol O’Keeffe as its first Territory Manager for Ireland and Northern Ireland Based in Dublin, Nicholas will give technica support and introduce the latest products and services by Coltene to dental practices, dental schools, laboratories and dental retailers all over Ireland Nick previously covered th Leinster and south east selling the Kin range of oral hyg products and should be a familiar face to many practices Allen, the new Coltene Count


market, commented: “This is a great achievement for Coltene to finally have grown our business reland to support a full-time colleague This can only elp to provide better support and communication for tists in Ireland I wish Nick every success in his new role ltene”
As you will be aware, in the 2017 Budget the Minister for Social Protection Dr Leo Varadkar announced his wish to extend the PRSI Dental Scheme (DTBS) to the self-employed, including farmers, from the end of March, and to return the scale and polish to all existing PRSI-eligible patients from October 2017
Following the Budget announcement, the IDA negotiating team has held a number of meetings with officials from the Department of Social Protection
We have found the discussions to be generally positive in nature and have welcomed the level of genuine engagement shown by the Department We believe significant progress has been made
Following a meeting held on March 9, 2017, the following was agreed:
n The DTBS scheme will be extended to cover the self-employed from March 27, 2017 This means that from March 27, self-employed persons with the required PRSI contributions will be eligible for a free annual examination under the scheme
n The self-employed are a new cohort of patient under the scheme and, as such, existing contract holders can opt in or opt out of treating them Letters from the Department of Social Protection have issued to DTBS contractors inviting them to opt in to treat the self-employed If a dentist wishes to treat the self-employed under their DTBS contract they should fill in, sign and return the form that will be attached to the letter If a dentist does not want to treat the self-employed they should not return the form In such circumstances, the dentist can continue to treat their current cohort of patients under the DTBS scheme as normal
n Dentists will be able to check the eligibility of self-employed patients for the annual examination in the normal way, i e , by phoning or emailing the treatment benefits section
n From October 2017, the scale and polish treatment will be reintroduced for
all eligible patients, as a once annually closed grant-in-aid treatment item The fee payable will be increased to ¤42 and the dentist will also be able to charge the patient up to ¤15 as an additional co-payment
n From October 2017, where it is deemed clinically necessary, i e , in the case of patients with pockets over 3 5mm, the protracted periodontal treatment will also be re-introduced and the ¤42 fee will go towards the cost of the protracted gum treatment on a once annual basis In the case of the protracted periodontal treatment, the dentist will be able to charge whatever total fee is required depending on the nature and length of treatment needed (open grant-in-aid)
n Financial Emergency Measures in the Public Interest (FEMPI) cuts to the examination fee will be unwound as part of the overall process of unwinding FEMPI
n The Minister will seek to reintroduce further elements of the scheme from 2018 onwards
n The Department of Social Protection will engage in a consultation process with the IDA over the coming months to review the DTBS contract These talks will also address the possible introduction of online claim processing and checking of entitlement, as well as the future indexation of fees
IDA negotiating team
Drs Clodagh McAllister, John Nolan, Kieran O’Connor and Tom Rodgers, Mr Fintan Hourihan, and Ms Roisín Farrelly
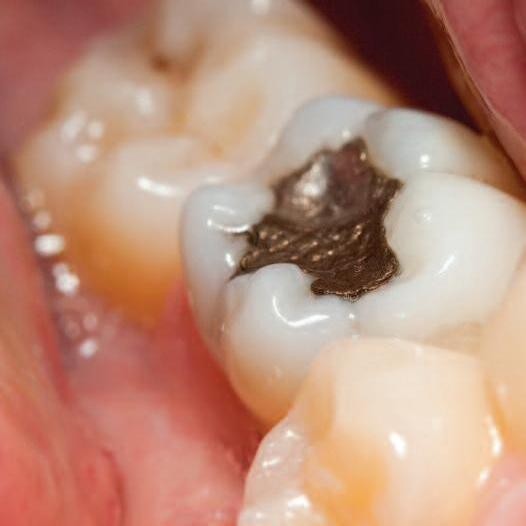
The European Union is in the process of ratifying the Minamata Convention on Mercury As part of this process, on March 14, 2017, the European Parliament approved a new legally binding Regulation on Mercury, which has a number of implications for the use of dental amalgam
The new Regulation will impose a ban on the placement of new dental amalgam restorations in children under 15 years of age and in pregnant and breastfeeding women from July 2018, except when strictly deemed necessary by the practitioner As yet, those parameters have not been established
The requirement for all dental practices to have an amalgam
s e p a r a t o r , o f a c c e p t a b l e
s t a n d a r d [ E N I S O
1 1 1 4 3 : 2 0 0 8 ] , w i l l b e mandatory throughout the EU
They have been required under Irish law since S I 126 of 2011 and this was underpinned by
t h e D e n t a l C o u n c i l i n 2 0 1 5
(Code of Practice Relating to
I n f e c t i o n P r e v e n t i o n a n d
Control, 2015, paragraph 4 2 2)
No decision has been taken about the eventual phasing out of dental amalgam

However, it is hoped by the EU institutions that this will take place by 2030 As a means of achieving this objective each Member State must have a national plan in place by July 1, 2019 to set out the measures they intend to implement to reduce the use of dental amalgam
The IDA has written to the HSE on foot of letters sent by the HSE to DTSS contractors asking that dentists supply a number of documents as a matter of urgency We have advised the HSE that there is no contractual obligation on dentists holding DTSS contracts to provide the information requested (covering professional indemnity cover, Dental Council registration, radiograph licence, and employer's and public liability provisions) to the HSE
The HSE has responded, stating: “The details being requested of DTSS contractors are, in the HSE's view, appropriate, proportionate and comprehended within the terms of the DTSS contract and constitute, by any reasonable standard, a very minimum ask in terms of compliance assurance on the part of contractors who are providing a publicly-funded service to eligible patients on behalf of the HSE under a contract for service arrangement
“From a public interest and patient safety perspective, the HSE cannot waive this mandatory requirement and in circumstances where DTSS contractors refuse to meet this contractual obligation the HSE will be left with very little option other than to invoke the mechanisms and processes within the contract for dealing with such material breaches”
The IDA’s advice remains that dentists are not obliged to provide the documents listed in the letter from the HSE, and the Association will offer assistance to any member who faces any sanction as threatened by the HSE
Last November, the IDA Council approved a position statement on dental amalgam acknowledging that mercury and its organic compounds are a significant environmental and health threat, but asserting that dental amalgam has a l
dental and scientific community The IDA supports the continued use of
Dental amalgam is a predictable and effective restorative material The IDA, in c
phasing down of dental amalgam as outlined in the Minamata Convention, but is calling on the Government and the dental community to prioritise prevention, oral health promotion, education and research
Infection pr evention and contr ol –new section of IDA members’ website
We are delighted to launch a new section of the IDA website on infection prevention and control (IPC) The new IPC section is available on the members’ area of the website under 'Best Practice'
As members will know, dental practices are obliged by the Dental Council to establish and maintain an IPC policy following the publication of the Dental Council’s Code of Practice Relating to: Infection Prevention and Control, April 2015
Members can now download a series of templates covering protocols, commission/validation regimes/testing, audit and governance as an aid to establishing the IPC policy for their practice The templates are generic and should be adapted for your own practice
The new section has been developed by the Quality and Patient Safety Committee and we would like to thank all members of the Committee for the hard work that has gone into a great new resource for members
The Association will continue to develop further templates and ensure that the present template remains accurate and contemporaneous
The Practitioner Health Matters Programme's annual report shows that it is helping health professionals who have mental health and substance misuse problems
The Practitioner Health Matters Programme (PHMP) has published its annual report for 2015-2016, and figures show that a number of practitioners, including dentists, have accessed and benefited from the Programme
The PHMP was launched in September 2015, and is a strictly confidential service which provides support and appropriate medical care for practitioners in Ireland who may be going through a difficult time with stress, mental health difficulties, or who may have an alcohol or drug misuse problem Doctors, dentists and pharmacists can access the service, which is endorsed by the regulatory bodies of the three professions and supported by the Irish Dental Association, the Irish Medical Organisation, the Irish Pharmaceutical Union and the professional training bodies, as well as by the HSE
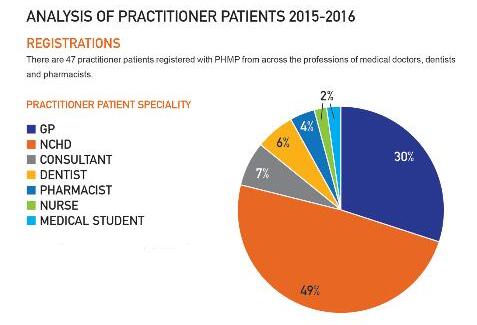
During 2015-2016, 47 practitioner patients registered with the PHMP from across the three professions The majority were medical doctors, but three dentists and three pharmacists also registered
Age and gender
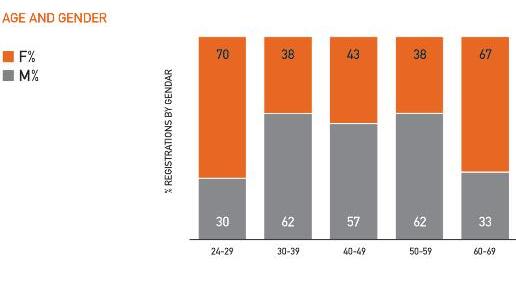
The largest numbers of registrations were represented in the age groups 30-39 (n=13) and 50-59 (n=13), with the fewest practitioner patients in the 60-69 age group (n=3)
Female practitioners represented just under half of the total registered practitioner patients (n=23) Numbers of females were greater than their male counterparts in both the youngest and oldest age groups; in the 24-29 and 6069 groups they represented 70% and 67%, respectively, of practitioners The 24-29 age group also represented the greatest individual numbers of female practitioners in one group (n=8)
Presenting problems
Thirty practitioners had a single presenting problem at registration, while 17 had more than one problem on presentation Substance misuse was the most common stand-alone presenting problem (n=15) followed by anxiety (n=6) and depression (n=4) Where practitioners presented with a combination of issues, depression was the most common presentation (n=13) followed by anxiety (n=10)
Results
Over half of all practitioner patients registered on the Programme have continued working in their professions and, with the support provided by the PHMP, did not need to take time off work Six were required to stop working for a period of time but have now either returned or are returning to work in the near future Seven patients are not currently working; of these, one has retired and the others are deemed unfit for practice and are under ongoing review
After the first year in operation, the PHMP is confident that it has made a difference and has offered practitioners an option in terms of addressing their health difficulties in confidence Feedback from the practitioners who have attended the programme so far is positive and highlights in particular the fact that the PHMP can provide them with additional time, which generic services may not have available to them
Contact with the PHMP can be made via the confidential email address or the d
www practitionerhealth ie Practitioners may self-refer or can be referred by others such as a concerned family member, a colleague or their GP Referrals can also be made by a professional training body or by the practitioner’s employer At all times confidentiality is of paramount importance
Contracts of employment are beneficial to both parties, and can settle many issues that arise.

When members ring me with HR queries I often ask them: what does the employee’s contract state or what does the employment contract say about the issue? Sometimes, however, the response I get is that the employee/employees in question do not have contracts of employment
Practice owners need to be aware that under the terms of the Employment (Information) Acts (1994-2001), employers are required to provide employees with a written statement setting out certain terms and conditions of employment within two months of commencing employment Generally, this written statement takes the form of a contract of employment
The following information must be included in the contract:
1 Full name of the employer and the employee
2 Address of the employer in the State
3 Place of work, or a statement that the employee is required or permitted to work at various places
4 Job title or a description of the nature of the work
5 Date of commencement of the employment
6 In the case of temporary contracts, the expected duration of the contract or, if for a fixed term, the date on which the contract expires
7 Rate of pay or method of calculating pay, e g , ¤12 per hour, or a certain fee per patient seen
8 Pay reference period, e g , fortnightly or monthly
9 Details of how often remuneration is paid, e g , weekly, monthly, together with confirmation that an employee may request written details of his/her hourly rate of pay
10 Terms and conditions relating to hours of work (including overtime)
11 Details of rest periods and breaks
Roisín Farrelly Employment and Communications Officer

12 Terms and conditions relating to paid leave
13 Terms and conditions relating to incapacity for work due to sickness or injury
14 Terms and conditions relating to pension schemes, if applicable
15 Notice period to be given and received by the employer
Other information that is often included in a contract of employment includes:
1 Information on the length of any probationary period
2 Commitments on flexibility/interchangeability
3 Information on lay-off/redundancy/short-time working conditions
4 Details of grievance and disciplinary procedures
6 Other practice rules or policies
7 Details of any deductions from pay
8 Normal retirement age
9 Confidentiality/non-compete clause
The employer is obliged to keep a copy of the contract during the period when the employee is working for them and for one year after termination of the employment Pro forma contracts of employment for dental surgery assistants, hygienists and associates are available to download from the Members’ section of the IDA website
Terms and conditions as set down in a contract of employment, including working hours and remuneration, cannot be varied without the consent of the employee If you feel it is necessary to change an existing employee’s terms and conditions you should:
n seek the employee’s agreement and maintain clear communication with him/her;
n be able to explain why the change is necessary and inform the employee of the alternative;
n provide the employee with reasonable notice of any variation to their terms and conditions;
n consider whether the new terms can be imposed in stages or whether an incentive can be offered to assist the employee in accepting the change; and,
n contact the IDA for advice

Applications are invited for the post of:
The Dublin Dental University Hospital is a centre of excellence in patient care, education and research, which enhances the learning experience of our students and the delivery of care to patients in an integrated and balanced way This is achieved in a safe environment by the effective use of the available resources and in response to the needs of the community through governance, partnership, investment in our staff, valuing diversity and the integration of technology The Hospital has a unique, and very important, relationship with Trinity College Dublin with which it co-operates in education and training of students.
Role:
The Chief Executive Officer (CEO) is a full-time role to which the Board of the Dublin Dental University Hospital will delegate overall authority, responsibility and accountability for all aspects of the operations of the Dublin Dental University Hospital The CEO is also the Accounting Officer with the final decision on how the resources of the Dublin Dental University Hospital are employed in the achievement of its strategic objectives
The CEO is responsible for carrying out the full range of functions and duties normally expected of a CEO in an organisation similar to the Hospital in nature, size, and economic and social significance
The CEO is a member of the Executive Team which also comprises the Clinical Director and the Dean
Requirements:
Ideally, the successful candidate should have extensive leadership and broad management experience, a track record of achievement in a complex and results-focused organisation (preferably Health Sector), strong experience of dealing with a wide range of stakeholders, may be a qualified dentist with a proven academic record and, in addition to previous relevant experience and personal skills, an appropriate educational qualification is desirable
Skills and attributes:
The successful candidate will have excellent resource and people management skills with the ability to motivate staff, demonstrate leadership and strategic skills, be a clear, analytical and decisive thinker and have drive, energy and commitment S/he must also have good communication and presentation skills, be a good negotiator and be a team player
Interested candidates need to refer to www dentalhospital ie/category/vacancies for full details of the application process:
Applications must be sent to Ita Goggin, Head of HR, ita goggin@ dental tcd ie or via post to Ita Goggin, Head of HR, Dublin Dental University Hospital, Lincoln Place, D02 F859
Closing date for applications is strictly 5.00pm on Tuesday 2nd May 2017
Shortlisting will take place Dublin Dental University Hospital is an equal opportunities employer



Irish dentists are among those working to assist the huge numbers of refugees currently stranded in Greece.
After seeing the images of the refugee crisis on our screens over the past few years, Dr Úna Shields and I had discussed wanting to do some volunteer work to help We discovered Dentaid and, through this, Health Point Foundation, two dental volunteering organisations We contacted them and arranged to fly to Thessaloniki in Northern Greece where there are numerous refugee camps
We fundraised and brought my surgical motor and lots of toothpaste for the children We met two other dentists from Scotland and England, respectively, and a dental nurse and hygienist from London, and we became a team In Greece we were introduced to two Health Point Foundation co-ordinators who were also dentists, and they knew how to set up the clinics each day
Language barriers
On our first working day we drove to Diavata camp, an ex-military barracks where there were approximately 400 refugees Whole families were housed in container units: mostly Syrian and Kurdish and a few Afghani people The camp

Dr Naomi Rahman
BDentSc DChDent (Oral Surg.) FFD
RCSI
Naomi is a specialist oral surgeon who practises in Dublin, Meath and Kildare
previously held 2,000 people living in tents, but the month before we arrived there was heavy snow so some people had been moved to small hotels in the area This was the dental base camp so we had the luxury of two dental chairs and suction, all housed within a shipping container
We were lucky to have translators there who had travelled from Egypt and Australia to volunteer to speak Arabic, and our hygienist was Kurdish so she was able to speak to the Kurds To speak to an Afghani woman, we had to call our translator’s friend in Australia to translate Farsi over the phone!
We quickly started to triage patients and then carry out first-stage root canal treatments, restorations and extractions Some patients had good oral health and beautiful dental work and others had never seen a dentist before in their life We were determined to treat our patients with respect and dignity In one instance we repeatedly asked a young man if he was okay as we were treating him He smiled and laughed and said: “Yes, I just feel like I’m in a foreign movie!”
We later went to the makeshift school, which had four classes, to give the children oral hygiene instruction, toothpaste and brushes
The dentist is here!
On our second day we drove to Lagkadikia Camp, which again held approximately 400 refugees Our clinic set-up was two massage beds in a container and one outside, with a mobile drill unit and no suction or radiographs Each morning we walked around the camps with a loudspeaker calling out “The dentist is here” in Arabic, Kurdish and English, and the patients


TOP: The intrepid team (from left); Dr Malcolm Hamilton, dentist; Dr Úna Shields, dentist; Dr Sheena Vyas, oral surgery SpR; Dr Ahmed Zaki Alsaleh, Health Point Foundation co-ordinator; Yahya, translator; Dr Naomi Rahman, oral surgeon; Terza Dilshad, hygienist; Rachna Rai, dental nurse; Amani Za, translator; and, Dr Rayyan Abdulwahed, Health Point Foundation co-ordinator
ABOVE: The best seat in the house!
ABOVE RIGHT: Our dental supplies, kindly donated by our sponsors [We would like to acknowledge and thank our sponsors, without whom this trip would not have been possible: Pamex; Dental Care Ireland; Curaprox; Happythreads; Coincidental; and, Colgate (who provided us with toothpaste) RIGHT: Treating a patient


quickly arrived at our door Úna treated a young girl who had not slept in a month due to toothache She needed a root canal treatment on an upper central incisor Her parents were not in the camp so she was living with her siblings We were all glad she at least got a good night’s sleep that night A Syrian man I treated who spoke good English found out that I love dogs He returned to the clinic later with a puppy for me to play with and gave me his lunch food rations as thanks for his treatment I was so touched by this heartfelt gesture
Our third day found us in Nea Kavala Camp, close to the Macedonian border We managed to fit the three massage chairs into the storage unit so we were all warm! Again we gave some children oral hygiene instruction and toothpaste
Every evening we met up with our whole team of co-ordinators, translators and clinical workers and had amazing Greek mezze dinners in Thessaloniki town The food was beautiful, fresh and inexpensive We all really bonded on this trip and formed firm friendships as we spent so much time together We are all still in touch on a WhatsApp group and Facebook
If you’d like more information, please visit www dentaid org or www healthpointfoundation

Maximising clinical efficiency using the dental laboratory to facilitate the planning and execution of crown preparations.
FIGURE 1: The pre-operative presentation of the patient in the maximum intercuspation position
When multiple teeth or localised segments of the mouth require crowns, the restorative interventions involved can be psychologically and physically demanding for the operator, patient and dental technician alike 1 2 It is important that all parties involved in restorations of this nature hold a shared understanding of the expected outcome of treatment, with a realistic, common end goal in mind right from the very beginning Such clarity of thought and communication is key to avoiding biological, mechanical and aesthetic failures
i n t h
Biomechanically stable and aesthetically pleasing provisional restorations are an essential aspect of treatment, which allow teeth to be prepared and provisionalised over multiple appointments within the comfort zone of the operator and patient 3 The following clinical article illustrates a diagnostic method which, prior to any invasive treatment at all, can aid the restorative operator in:
1 Determining the feasibility of a proposed treatment plan
2 Determining the aesthetic acceptability of the proposed restorations from the perspective of the patient and operator

Dr David McReynolds
BA BDentSc MFDS RCSEd
Specialist Registrar in Prosthodontics, Department of Restorative Dentistry and Periodontology, Division II, Dublin Dental University Hospital, Lincoln Place, Dublin 2 david mcreynolds@dental tcd ie
FIGURE 2: An initial course of fixed orthodontic treatment is prescribed on the maxillary arch in order to procline the maxillary labial segment dentition
An occlusal splint on the mandibular arch allows free movement of the maxillary labial segment dentition
3 Informing the operator of the tooth preparations required with a view towards conserving tooth structure
4 Simply provisionalising multiple teeth simultaneously in a biomechanically stable and aesthetically pleasing manner
These goals can be achieved by making high-quality pre-operative records, which allow the lab to form pre-operative models, diagnostically waxed-up models and provisional shell crowns The records gathered at this diagnostic stage may be transferred back to the mouth at relevant times to inform the operator, patient and dental technician of the nature of the work required in order to fulfil the treatment plan
It is assumed prior to commencement of the following techniques that the mouth has been suitably prepared for reconstructive dentistry, insofar that the periodontal, endodontic and caries status of the dentition is treated, and disease stability has been established and maintained for an extended period of time Oral hygiene and diet must be persistently and consistently held to a high standard and the patient must be medically and psychologically robust enough to tolerate the necessary procedures Segmental reconstruction is not straightforward and should only be undertaken by suitably experienced and qualified practitioners 1 2 This report shows an example of the above described technique, and the treatment of a localised segment of the mouth only, as part of a complex full mouth restoration
Case report
The patient is a 50-year-old gentleman in good health, whose chief complaint
4a, 4b, 4c, 4d, 4e, 4f: Maxillary and mandibular two-stage polyvinylsiloxane impressions, a maxillary transfer bow recording and an interocclusal wax record in the centric maxillomandibular relation position are made immediately following orthodontic debond The two-stage impression technique illustrated produces exceptionally accurate study models
was of “ worn, discoloured teeth which don’t look right” Extra-oral assessment revealed a mild class III skeletal arrangement, high functional lip line and loss of the vertical dimension of occlusion, while intra-oral examination (Figure 1) displayed a class III incisor relationship in a dentition severely affected by tooth structure loss which appeared to be of attritive, abrasive and erosive origin, exacerbated by the absence of the anterior determinants of tooth-guided o c c
attachment loss; however, the periodontal status was stable with good oral hygiene, no evidence of periodontal pocketing greater than 3mm and no evidence of bleeding on probing
Initial treatment
Following a multidisciplinary assessment, an initial course of fixed orthodontic treatment was prescribed in the maxillary arch in order to procline the maxillary labial segment dentition (Figure 2) A “bite-raising” appliance is used in the mandibular arch, which allows free movement of the maxillary labial segment teeth during the orthodontic phase of treatment Initial treatment took approximately eight months and resulted in an edge-to-edge occlusion at the first tooth contact position on the rotational arc of closure (Figures 3a-3c) No further orthodontic movement was advisable at this point following a risk–benefit analysis
Diagnostic method
Making preoperative records
Immediately following the debonding of orthodontic fixed appliances, preoperative records are fabricated (Figures 4a-4f) Maxillary and mandibular impressions may be made in a two-stage technique using polyvinylsiloxane Initial impressions are made using putty only and a polyethylene spacer (Figures 4a and 4b) Once the putty has completely set and the plastic spacer has been removed, the impression can be completed using a light body wash material (Figures 4c and 4d) Polyvinylsiloxane impressions are highly accurate and are robust enough to permit multiple pours, which offers some advantages over alginate in this diagnostic method A transfer bow recording should be made to relate the resultant maxillary cast to the transverse horizontal hinge axis and an interocclusal wax record is made (Figures 4e and 4f) in the centric maxillomandibular relation treatment position at the proposed vertical dimension of occlusion These records can be used to mount casts in a semiadjustable articulator such as the Whipmix 2240 4 A programmed semiadjustable articulator will transfer to the lab the patient’s midline and interpupillary line, and it allows simulation of mandibular movements, thus determining the occlusal form of the final restorations with a reasonable degree of accuracy Indirect restorations fabricated in this manner will require minimal occlusal adjustment on fitting




8c), tooth-guided articulation and maxillary occlusal plane, and thus of the contours of all teeth to be restored (Figures 9a-9c) Initially, the incisal edge can be waxed to average dimensions according to published data for the population being treated5 and can be later modified to the subjective preferences of the patient if required 3
A well-made diagnostic wax-up permits clear communication between the dental technician and dentist with regards to the desired outcome of
treatment and, in combination with a diagnostic mock-up, will highlight pre-operatively any potential limitations of treatment from a biological, mechanical and aesthetic perspective
3 Provisional shell crowns
A third set of models produces casts from which provisional shell crowns can be fabricated (Figures 10a-10f) Shallow depth cuts and shallow trial preparations are carried out on these models A putty matrix made from

Précis
Get it done in year one! A practical approach to an infant oral health visit is presented to encourage commencement of oral healthcare at this important age
Abstract
The IDA adopted a formal policy on children’s oral health in 2011 There is increasing evidence to support early dental visits for children. The background to the infant oral health visit is discussed and a systematic approach to the practicalities of the visit is offered. General dental practitioners are encouraged to offer the first oral health visit before the first birthday, and this paper aims to give them practical advice concerning this visit The feature is accompanied by a companion paper that reviews the literature pertaining to the topic, and serves to complement the recent clinical feature published in the Jour nal of the Irish Dental Association
Journal of the Irish Dental Association 2017; 63 (2): 99-104
Introduction
The Irish Dental Association (IDA) adopted a formal policy on children’s oral health in 2011 1 This was the second policy position paper from the Association, highlighting its standing on child oral health promotion in Ireland This standpoint is echoed by the World Health Organisation (WHO),2 the European Academy of Paediatric Dentistry (EAPD),3 the American Academy of Pediatric Dentistry (AAPD),4 and the British Society of Paediatric Dentistry (BSPD) 5 Given the preventable nature of dental caries, early identification of the children at risk and the utilisation of appropriate preventive measures by the dental team are to be encouraged


Dr Kirsten FitzGerald
BDentSc MS (Texas) FFD (RCSI)
The Irish standpoint
Measures supporting public dental health in Ireland have achieved enormous progress, particularly for children There has been a reduction of 75% in the mean decayed, missing, or filled teeth (DMFT) index scores for 12-15 year olds and in the mean DMFT scores for five year olds between the 1960s and 2002 6 Community water fluoridation was one of the greatest public health successes of the 20th century,7 being effective in both disadvantaged and nondisadvantaged communities The dental profession should continue to work hard to advocate for continued community water fluoridation Fluoride toothpastes were introduced into Ireland in the 1970s Supported by
Consultant Paediatric Dental Surgeon, Our Lady’s Children’s Hospital, Crumlin, and Dublin Dental University Hospital
Dr Eleanor McGovern
BDS MFD MDentCh (Paediatric Dentistry)
Consultant Paediatric Dental Surgeon, The Children’s University Hospital, Temple Street
Corresponding author:
Dr Aifric Ní Chaollaí
BA BDentSC MDentSc (Leeds) MPaedDent (RCPSG) Paediatric Dentist at Dental Care Ireland, Cabinteely and the Northbrook Clinic, Ranelagh
Dr Brett Duane
BDS MAM (Health) MPH PHD Associate Professor, Dental Public Health, Dublin Dental University Hospital
Dr Kirsten FitzGerald, Dental Department, Our Lady’s Children’s Hospital, Crumlin E: kirsten fitzgerald@olchc ie T: 01-409 6549
This link http://bit.ly/2iNCSlI contains four demonstration videos on examining and brushing infants' and toddlers' teeth, which were made with the support of UCD and the Genetics Department at Our Lady's Children's Hospital Crumlin
more than half a century of research, the benefits of fluoride toothpastes are firmly established Full-strength formulations (1,450ppm) are best, and twice a day use, without rinsing afterwards, increases the benefit 8 Full strength fluoride toothpaste is now recommended for all children in Ireland over the age of two, and for high caries risk children under that age 9 Medicines formulated for children are subject to the European Medicines
A g e n c y ’ s “ G u i d
paediatric use”,10 which states: “Frequent and/or high doses of sweetening agents should preferably be avoided in paediatric formulations intended for long-term use The use of cariogenic sugars should be carefully justified” Doctors are encouraged to prescribe sugar-free formulations where available and appropriate
Unfortunately, the absence of a current oral health policy, the lack of up-todate epidemiological data, and the decline in access to care for adults of lower socioeconomic status in recent years are signs of the underfunding and low priority given to oral health and dental services in Ireland Without doubt, these issues have an impact on our children’s oral health both directly and indirectly There appears to be some lack of awareness among parents and non-dental healthcare providers around the issue of early childhood caries, its causes, effects and the measures that can be employed to prevent its occurrence Infant feeding practices are important in the development of early childhood
caries, and frequent ingestion of sugar-sweetened drinks and snacks are highrisk factors for both caries and obesity There is very limited care provided by the public dental services for pre-school children in Ireland This is concerning as dental caries is the most common chronic disease of childhood in Ireland, a situation which is echoed internationally
The WHO accurately describes the impact of poor oral health, particularly caries, on the child and family: “Severe caries detracts from children’s quality of life: they experience pain, discomfort, disfigurement, acute and chronic infections, and eating and sleep disruption as well as higher risk of hospitalisation, high treatment costs and loss of school days with the consequently diminished ability to learn Caries affects nutrition, growth and weight gain Children of three years of age with nursing caries weighed about 1kg less than control children because toothache and infection alter eating and sleeping habits, dietary intake and metabolic processes” 2
The IDA, in its policy on children’s oral health,1 values oral health as “ an integral part of the overall health and well-being of children”, which reflects the WHO standpoint Health spending is limited by the available resources Current per capita public spend on health in Ireland is in the region of ¤3,100 per
of
for
population of 4 58 million at the 2011 census It is easy to see how operative treatment (restoration and extractions) of a dentition affected by severe early childhood caries, which is likely to require general anaesthesia, could deplete per capita healthcare resources very quickly A health promoting and preventive strategy is urgently needed, in line with early child health strategies
Preventable nature of oral disease in childhood
Dental caries is largely preventable The reader is directed to the companion paper by Duane et al , published in this edition of the Journal
The dental home
Central to many effective models of oral healthcare is the concept of the dental home: the patient-centred, family-friendly relationship between healthcare provider and patient that fosters primary oral healthcare, and enables appropriate referral to secondary and tertiary services as needed 12 The emphasis is on the relationship between the dentist (or other suitable healthcare provider), their team, and the family This is akin to the medical home, which is usually facilitated by the general medical practitioner, supported by a practice nurse and with a network of local, regional and supraregional referral pathways Most pre-school children in Ireland lack a dental home, but the available oral health workforce, led by dentists, could be organised and developed to provide a dental home for all children The workforce would consist of the obvious: dentists; dental hygienists; dental nurses; and, oral health promoters Some less obvious members of the healthcare team such as public health nurses, general medical practitioners and area medical officers have also been recruited in some healthcare systems internationally to serve as the first point of contact for risk assessment and implementation of caries preventive measures
Rationale for timing of the first oral health visit
Antenatal oral healthcare for expectant mothers is recommended as a good first s t e p i n
partnership Given that transmission of cariogenic bacteria is thought to occur around the time of eruption of the first tooth,13 and in light of the normal developmental milestones and dietary changes of children in the first year of life, timing of the first oral health visit to coincide with these events is sensible
Weaning from milk to solid foods is recommended around six months, and dietary habits begin to become established Preventive advice can be given at appropriate times in a format known as anticipatory guidance, which involves giving proactive advice and counselling that focuses on the child’s needs at different stages In this way, parents receive tailored advice that meets their child’s current and upcoming developmental needs Both the EAPD and the AAPD recommend that children should have their first dental visit with counselling during the first year of life 3 14 Offering an infant oral health visit can help build a family-friendly environment, enhancing a dental practice
Special healthcare needs
Children with special healthcare needs such as craniofacial anomalies or other medical, physical or intellectual conditions can be at increased risk of developing dental caries, and may also be at increased risk from the effects of the disease They should receive targeted preventive care in line with the best available evidence The early oral health visit can help identify these children and afford them an increased level of protection to counteract their vulnerability
Clinical guidelines and toolkits
There are many useful guidelines and clinical practice toolkits available to the practitioner to aid them in their management of the young child with and without caries 3 14-25 These resources, both Irish and international, are listed in Table 1
For practitioners who wish to offer the infant oral health visit in their practice, some new knowledge and skills may be needed, and it is hoped that the following advice and systematic approach will facilitate both the practitioner and the family An example of a systematic approach to the visit that may be useful is given in Appendix 1 The visit should include a formal caries risk assessment, which is generally best achieved with the aid of a tool such as the Caries Risk Assessment Checklist (CRAC),17 which is suitable for all children, or a specific tool aimed at the 0-3 age group such as the AAPD’s Caries-risk Assessment Tool (CAT) 23 It is important to remember that caries risk is dynamic, and regular reassessment of risk is appropriate
The reader is directed to the recent clinical feature published in this Journal for a systematic approach to the infant oral health visit 26 Having clear aims and objectives for the visit, employing techniques to minimise stress for all involved, using a systematic or pro forma approach to the history, examination and advice, and being prepared to manage or refer as appropriate if disease is encountered, should all help to make the visit enjoyable, beneficial and rewarding for all
Although it is most unusual to find cavitated caries in children under one year of age, it is possible to find demineralisation Such a finding may be disappointing, but it should be considered an opportunity to highlight issues early before cavitation occurs, and with appropriate advice and aggressive preventive measures, much of this disease can be arrested Infants with early signs of caries should be placed on three-month recall for fluoride varnish application and review At home, these high-risk infants should have their teeth brushed with a full-strength fluoride toothpaste (1,450ppm), with careful advice around how much to apply to the brush to minimise the potential for fluorosis Dietary advice should emphasise the importance of water as the only safe drink for all babies at night time Milk (cow’s or formula) taken from a bottle throughout the night is highly cariogenic and this practice is to be highlighted and strongly discouraged The authors find that photographs of carious incisors are a useful visual aid for educating parents who may be reluctant to discontinue night-time use of a bottle of milk Fluoride varnish should be applied for all children at this visit The teeth should be dried with gauze, and varnish applied with a brush or gloved finger, to areas of high risk in particular Concerns around fluoride toxicity with respect to fluoride varnish application are addressed by careful consideration and discussion of the appropriate dose Fluoride varnish 22,600ppm (e g , Duraphat or Profluorid) contains 22 6mg fluoride per ml The correct dose for children under six is 0 25ml The toxic dose of fluoride ingestion is estimated at 5mg of fluoride per kg of child body weight The average one year old weighs approximately 9kg, and so the dose of 0 25ml of varnish, containing 5 6mg of fluoride, being approximately one-tenth of the toxic dose, is well within safe levels Application up to four times a year is also safe with respect to concerns around chronic ingestion A blob 5-7mm in diameter will be

adequate (Figure 1) Single-dose packaging conveniently combines a brush with a small volume of fluoride varnish (Figure 2) Many of the single dose
varnishes available on the market are 0 4ml in volume, but Premier’s Enamel
Pro Varnish comes in a bubblegum flavour in a 0 25ml single-dose packet
Appendix 1 – Baby steps: a checklist for the infant oral health visit
History
n Child perinatal and ongoing medical history
n Caries risk assessment (CRAC or AAPD)
n Feeding practices (use of bottles of milk or other sweet liquid while asleep, between meals food and drink exposure)
n Systemic and topical fluoride status (water, formula and toothpaste)
n Non-nutritive sucking habits (thumb/soother)
n Trauma

Examination
n Knee-to-knee position
n Dry teeth with gauze, use a prop if needed
n Examine for caries, trauma and abnormalities of dental development, and soft tissues
n Toothbrushing demonstration, three-sided brush (Figure 3) if needed
n “Lift the lip” demonstration
Preventive care
n Remove any soft and hard deposits
n Apply 5% NaF fluoride varnish to erupted teeth
Treatment of severe early childhood caries (SECC)
n White spot lesions (Figure 4): this is SECC Apply fluoride varnish, educate about oral health and diet Advise home use of a smear of 1,450ppm fluoride toothpaste twice daily, without rinsing after brushing
n Cavitated lesions in upper incisors: manage as above, plus consider interim therapeutic restoration (ITR) with glass ionomer as a preventive
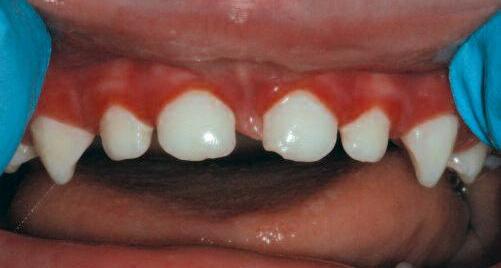
4: Demineralised maxillary incisors in a child under three years old This is severe early childhood caries Note the inflamed gingivae as a result of plaque accumulation
As children get a little older, examination can be resisted a little more strongly Correct use of the knee-to-knee position is invaluable, and practitioners are advised to learn this simple yet effective technique by watching videos available online 25 Informed consent for the examination should include adequate discussion of the method of examination, the likely time it will take, and a reassurance that the toddler’s protest is entirely normal By the same token, a toddler’s protests about tooth brushing at home are reassuringly normal Parents can be advised to brush a baby’s teeth using the knee-to-knee position (two adults required), or on the bed or couch at home Specialised three-sided brushes are recommended (Figure 3), perhaps with the use of a plastic toothbrush handle as a mouth prop if needed
Prolonged non-nutritive sucking habits may be identified at the first oral health visit, and the orthodontic effects (anterior open bite, narrowed maxillary arch, protruding maxillary incisors) may already be evident Parents
and therapeutic approach Consider specialist referral
n Large cavitated lesions in incisors (Figure 5): manage as above, plus consider specialist referral Use full coverage restorations, particularly if compliance for prevention is an issue (Figure 6)
should be advised to use only orthodontic soothers, and to discontinue their use by around 18 months of age
If it is identified that parents are using inappropriate foods for weaning, such as those with a high sugar or salt content, general nutrition advice should be given, and onward referral to a general medical practitioner or public health nurse may be necessary
Some well-meaning, but poorly-informed parents begin using fluoridated toothpaste for their infants earlier than the recommended age of two years For the infant identified as being at low risk for dental caries, the use of fluoride toothpaste is to be discouraged until two years of age, when the enamel of the permanent incisors is quite mature, and so the risk of cosmetically concerning fluorosis is low It should be emphasised, however, that use of full-strength fluoride toothpaste is appropriate for high-risk children in this age group, as the caries-preventive effects outweigh the risks of fluorosis
n Extensive disease (Figure 7) with/without pulpal involvement: manage as above, plus consider referral to a specialist provider for definitive care
Establishing the dental home and periodicity of review
n Discuss ongoing relationship between dental team and patient in terms of the “dental home”
n Determine the interval for periodic review (three, six or 12 months) based on risk
n If needed, refer to a specialist provider, with arrangements for follow-up at the dental home
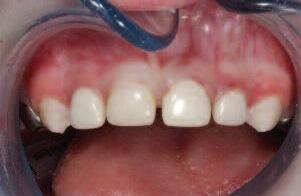
Key points for the infant oral health visit
The key points for the visit can be summarised as follows:
■ caries risk assessment – includes medical, social and dental history;
■ knee-to-knee examination;
■ preventive care – oral hygiene demonstration, toothpaste advice, fluoride varnish;
■ education – weaning, diet, drinks, pacifier use/cessation; and,
■ establish the dental home
Summary
The first oral health visit should be carried out within the first year of life This affords the practitioner the opportunity to convey suitable preventive advice, to identify potential problems early, and to place children at high caries risk on the appropriate preventive programme The general dental practitioner is encouraged to examine and provide oral healthcare and advice for infants and young children, and the resources, advice and techniques presented here aim to facilitate practitioners who wish to include this service in their practice
References
1 Irish Dental Association Children’s oral health Journal of Irish Dental Association 2011/2012; 57 (6): 284
2 Sheiham, A Oral health, general health and quality of life Bull World Health Organ 2005; 83(9): 644 Epub 2005 September 30
3 European Academy of Paediatric Dentistry Guidelines on Prevention of Early Childhood Caries: An EAPD Policy Document [Internet] 2008 [undated: cited January 12, 2017] Available from: http://www eapd gr/dat/1722F50D/file pdf
4 American Academy of Pediatric Dentistry Policy on Early Childhood Caries (ECC): Classifications, Consequences, and Preventive Strategies [Internet] Chicago: American Academy of Pediatric Dentistry; 2015 [undated: cited January 12, 2017] Available from: http://www aapd org/media/policies guidelines/p eccclassifications pdf
5 Fayle, S A , Welbury, R R , Roberts, J F ; British Society of Paediatric Dentistry British Society of Paediatric Dentistry: a policy document on management of caries in the primary dentition Int J Paediatr Dent 2001; 11 (2): 153-157
6 Whelton, H , O’Mullane, D , Harding, M , Guiney, H , Cronin, M , Flannery, E , et al North/South survey of children s oral health in Ireland 2002 Brunswick Press Ltd, 2006 [cited January 12, 2017] Available from: http://www lenus ie/hse/bitstream/ 10147/119028/1/OralHealthReport pdf
7 Centers for Disease Control and Prevention Ten Great Public Health Achievements in the 20th Century [Internet] Atlanta: Centers for Disease Control and Prevention; no date [ u p d a t e d A p r i l 2 6 , 2 0 1 3 , c i t e d J a
http://www cdc gov/about/history/tengpha htm
8 Marinho, V C C , Higgins, J P T , Logan, S , Sheiham, A Fluoride toothpastes for preventing dental caries in children and adolescents Cochrane Database Syst Rev 2003; Issue 1 Art No : CD002278
9 Forum on Fluoridation Dublin Stationery Office, 2002 [cited January 12, 2017] A v a i l a b l e f r o m : h t t p
/ fluoridation forum pdf
10 European Medicines Agency Guideline on development of pharmaceuticals for paediatric use London: European Medicines Agency 2013 [cited January 12, 2017] A v a i l a b l e f r o m : h t t p : / /
/ Scientific guideline/2013/07/WC500147002 pdf
11 Department of Health, Information Unit. Health in Ireland: Key Trends Dublin: S t a t
http://health gov ie/wp-content/uploads/2015/12/Health in Ireland KeyTrends 2015 pdf
12 American Academy of Pediatric Dentistry Policy on the Dental Home [Internet] Chicago: American Academy of Pediatric Dentistry; 2015 [undated: cited January 12 2 0 1 7 ] A v a
P DentalHome pdf
13 Berkowitz, R J Mutans streptococci: acquisition and transmission Pediatr Dent 2006; 28 (2): 106-109; discussion 192-198
14 American Academy of Pediatric Dentistry Guideline on Infant Oral Health Care [Internet] Chicago: 2015 [undated: cited January 12, 2017] Available from: http://www aapd org/media/policies guidelines/g infantoralhealthcare pdf
15 Irish Oral Health Services Guideline Initiative Oral Health Assessment: Best practice guidance for providing an oral health assessment programme for school-aged children in
https://www ucc ie/en/ohsrc/guidelines/
16 Irish Oral Health Services Guideline Initiative Pit and Fissure Sealants: Evidence-based guidance on the use of sealants for the prevention and management of pit and fissure c
www ucc ie/en/ohsrc/guidelines
17 Irish Oral Health Services Guideline Initiative Strategies to prevent dental caries in children and adolescents: Evidence-based guidance on identifying high caries risk children and developing preventive strategies for high caries risk children in Ireland (Full guideline) 2009 [undated: cited January 12, 2017] Available at: www ucc ie/en/ohsrc/ guidelines/
18 Irish Oral Health Services Guideline Initiative Topical Fluorides: Evidence-based guidance on the use of topical fluorides for caries prevention in children and adolescents i
www ucc ie/en/ohsrc/guidelines/
19 Scottish Intercollegiate Guidelines Network (SIGN) Dental interventions to prevent caries in children Edinburgh: 2014 (SIGN publication no 138) [March 2014; cited January 12, 2017] Available from: www sign ac uk
20 Scottish Dental Clinical Effectiveness Programme Prevention and Management of Dental Caries in Children Dundee: 2010 [undated; January 12, 2017] Available from: http://www sdcep org uk/published-guidance/caries-in-children/
21 Childsmile Professionals [Internet] [undated: cited January 12, 2017] Available from: www child-smile org uk/professionals/index aspx?
22 European Academy of Paediatric Dentistry Guidelines on the use of fluoride in children: an EAPD policy document Eur Arch Paediatr Dent 2009; 10 (3): 129-135 [undated: cited January 12, 2017] Available from: http://www eapd gr/dat/ 82C0BD03/file pdf
23 American Academy of Pediatric Dentistry Guideline on Caries-risk Assessment and Management for Infants, Children, and Adolescents [Internet] Chicago: 2015 [undated; cited January 12, 2017] Available from: www aapd org/media/ policies guidelines/ g cariesriskassessment pdf
24 American Academy of Pediatric Dentistry Guideline on Periodicity of Examination, Preventive Dental Services, Anticipatory Guidance/Counseling, and Oral Treatment for Infants, Children, and Adolescents [Internet] Chicago: 2015 [undated: cited January 12, 2 0 1 7 ] A v a i l a b l e f r o m : h t t p : / / w w w a a p d o r g / m e d i a / p o l i c i e s g u i d e l i n e s / g periodicity pdf
25 Novia Scotia Dental Association Knee-To-Knee Training Video [Internet] 2013 [cited January 12, 2017] Available from: www youtube com/watch?v=9hu Dzl5OpbQ&sns=em
26 FitzGerald, K , McGovern, E , Ní Chaollaí, A , Duane, B Baby steps: a systematic approach to the infant oral health visit Journal of Irish Dental Association 2016; 62 (3): 158-160
provides emergency, routine and preventive oral health services to children up to 16 years of age and to people of all ages with special needs 5 The resources, priorities and service interventions vary considerably within and between regions The HSE also operates a school dental programme where nationally, school children and children with special needs are screened in selected classes 6 It is possible that children who attend national school and do not present with a dental emergency do not receive dental care until they are screened by the HSE at six to eight years of age, with the possibility of even later attendance for some In some areas, it is possible that this screening is delayed due to resourcing issues
In the UK, dental caries has been reported as the most common reason for children between five and nine years of age to be admitted to hospital for treatment under general anaesthesia (GA), equating to 31% of all GAs administered to children in that age group 7 This dental treatment under GA is concerning due to the GA-associated morbidity and risk of mortality The financial burden is considerable: in England it has an estimated cost of £30 million (2012) 8-10
There may be some underestimation in the numbers of children reported to have had dental treatment provided under GA in the UK 11 Within Ireland, the lack of reliable data is also apparent with recent national discussions having highlighted this uncertainty 12 Within the Irish Healthcare Pricing Office’s report for the year ended December 2014, it is noted there were 8,406 procedures carried out in acute hospitals for dental-related morbidity for children under 15 years, with 4,320 patient discharges relating to dental care in under 15s 13 It is likely that the majority of these patients’ discharges were related to GA There is, however, some debate about the number of GAs undertaken for children for dental care, which has been reported in October 2015 by the HSE as being 3,600 per year in Ireland 12
It is certain that dental caries is problematic Not only does the disease significantly impact on child well-being,14 but societally it is an expensive and time-consuming problem to treat, both for the State, and for parents of children who elect to be seen privately Internationally, early childhood caries (ECC), defined as the presence of decay in one or more primary teeth in a child younger than six years of age, is reported to affect 28-82% of children 15 ECC is also a strong predictor of caries in future life 16 From a public health perspective it is important, therefore, to do as much as possible to reduce the occurrence of ECC
Primary prevention (before dental decay develops) is key
This paper reviews the recent evidence for the benefits to infants aged 12 months or less of attending a dentist It reviews the types of oral health interventions that can be delivered either on an individual basis or in a population programme to the infant, and applies that evidence to addressing the issues in the context of the Irish health system
Methods
A review was undertaken of all papers which addressed the following question: what are the benefits to infants aged 12 months or less of attending a dentist, specifically: pathology/soft tissue; early dental prevention; caries prevention; fluoride varnish; tooth brushing; nutrition; education of parents/behavioural change of parents; and, health visitor referral (Ireland: public health nurse visits after birth and at six weeks)?
For the purpose of this review only randomised controlled trials (RCTs) and systematic reviews published in the English language within the last 10 years were searched, using the databases Web of Science, Embase, CINAHL and
Table 1: Summary of interventions that can influence the oral health of a child
Perform risk assessment
Provide oral health education using a motivational interviewing approach
Prevention: fluoridated water; fluoride gels; varnishes; and, mouthwashes
Oral health promotion
Others with possible benefit: CPP; and, xylitol
PubMed The review was not intended to be systematic, but was undertaken to find relevant evidence to answer the question, and produce a narrative review on the topic of interest This was not a systematic review; therefore, tools were not used to assess quality and bias Two individual authors (B D and K F ) assessed each paper for its relevance to the research question and to the Irish landscape Both individual interventions and population approaches were considered
From an individual perspective there is significant evidence of the benefits of infants attending a dentist before the age of 12 months The interventions that can influence the oral health of a child can be seen in Table 1, and each is discussed in more detail below The interventions are then discussed in the Irish context and with reference to cost-effectiveness
Performing a risk assessment
To prevent caries in children, high-risk individuals should be identified at an early age before problems occur Babu and Doddamani state that risk factors should be assessed in mothers during prenatal care and strategies should be adopted, including anticipatory guidance, behaviour modifications (oral hygiene and feeding practices) and establishment of a dental home by one year of age for children deemed at risk 17 Seeing children at an early age enables a clinician
factors/indicators and protective factors, and then to design an appropriate intervention tailored to a child’s individualised risk An example of a caries risk assessment tool is given in the UCC guidance 18
The strategy of risk assessment for caries is used within the Scottish Childsmile programme – a targeted preventive programme that has been successful in reducing the prevalence of caries in children in Scotland 19 Children who are considered to be at high risk within Scotland are given appropriate support by a dedicated team of dental health support workers, including support for behavioural modification (oral hygiene and feeding practices) 17
In addition to the risk factors/indicators and protective factors as described in the UCC guidance,18 there are additional risk factors identified in the literature, which contribute to the development of dental caries in children There have been a number of reviews demonstrating both the evidence of a vertical transmission of Streptococcus mutans from mother to child, and the increased risk this can cause to a child’s oral health 20-22 Hooley demonstrated high caries rates within single-parent families, large family sizes, low education, minority ethnicity, immigrants, and poor living conditions 23 The Scottish Intercollegiate Guidelines Network (SIGN) 138 document lists dietary habits, oral hygiene, microbiological risk factors, socio-demographic markers and previous caries experience as risk factors for dental caries in children 24 In Kumar et al ’s
systematic review of parent-related factors on dental caries in the permanent dentition of six- to 12-year-old children, children with highly-educated, professional and high-income parents were at lower risk 25 The relationship between higher caries rate and deprivation is well documented and apparent in recent epidemiological surveys 1 Leong et al outlined a number of risk factors that can increase a child’s risk of dental caries 21
An oral health education programme should include a common risk approach and advice on common risks in oral and general health, including advice on diet, adequate intake of fresh fruit and vegetables, reduced sugar intake, smoking cessation, etc
Due to the relationship between diet and caries,26 influencing diet is an important part of any oral health prevention programme The diet that children are exposed to in their early formative years influences the development of their taste and food preferences, highlighting the need to intervene early 27 Obesity and dental caries are significantly associated with the consumption of foods high in sugar and are more pronounced in those of lower socioeconomic status
Soft drink consumption provides a significant source of added sugar to the diet and contributes around 5% to average total energy intake in men aged 19-24 years 23,28 Obesity is one of the primary challenges to public health, so the need for immediate preventive action is warranted 29 Hooley suggests that the level of health knowledge and skills possessed by parents will influence children’s diet choice, as well as the level of physical activity within their lives, which in turn influences their weight 23 Dentists can play an important role in supporting healthy feeding practices and improving long-term health in these children 31
The type of health education that takes place in dental practices traditionally involves giving oral hygiene and diet advice rather than using the newer motivational interviewing (MI) approach There are a number of reviews that have investigated the effectiveness of traditional oral health education on reducing caries risk Kay and Locker looked at the effectiveness of health education and its relationship to oral health improvement 32 The authors could not conclude that oral health education was effective in reducing oral disease indices There were only improvements in oral health in programmes which included fluoride Harris et al reviewed five studies looking at one-to-one dietary interventions within a dental setting In this review, each study demonstrated a change in dietary behaviour 33 A third, more recent paper, by Chaffee et al noted that there was no difference in infant oral health when oral health education was provided by one group of healthcare workers who had received training and the other group of workers who had not received such education 34 The majority of evidence suggests therefore that a simple oral health improvement programme consisting of education only is unlikely to be effective at reducing oral disease MI is an approach that is based on psychology and defined by Miller and Rollnick as a technique based on evidence, centred on the individual and individually tailored MI involves setting goals and providing client-centred counselling in an attempt to elicit behavioural change 35 For more information on this please refer to Curtin’s useful paper 36 Yevlahova (2009) performed a review of 32 studies and demonstrated that MI interventions were the most effective method for altering health behaviours in a clinical setting 37 Ismail (2011) evaluated the effectiveness of a tailored educational intervention on oral health behaviours and new untreated carious lesions One group received both MI and a DVD, with booster calls six months after the intervention, while the
other group received just the DVD After six months of follow-up, the parents who received MI and DVD were more likely to have changed oral health behaviour There was, however, no change in new untreated carious lesions 38 Six months is also a short time period to assess the development of untreated lesions In contrast, Harrison performed a cluster randomised pragmatic effectiveness trial testing MI in Canadian indigenous children When the children were examined at 30 months of age there was a substantial preventive effect for dental decay 39
Leong suggests that oral health promotion leaders need to identify, as part of the oral health promotion programme development, why some health behaviour programmes are adopted and others are not Strategies often do not sufficiently consider the socio-cultural content or behavioural determinants that influence individual behaviour Factors identified in his review that may add further complexity include the broader social determinants of health such as identified by Marmot 40 These five key areas (determinants) are also defined by healthy people to include economic stability, education, social and community context, health and healthcare, and neighbourhood and built environment 41
The relationship between fluoride and caries reduction was first demonstrated by Dean in 1944 44 Topical fluoride reduces dental disease by reducing demineralisation and encouraging remineralisation of the tooth surface 45 Splieth has also demonstrated the considerable cost benefits of using fluoride in reducing the cost of operative dentistry over the life course 46 Fluoride can be delivered through water fluoridation, toothpaste, gel, varnish and mouthwash From the studies reviewed it is clear that there is consistent and strong evidence that the use of fluoride can significantly reduce dental caries The best available evidence suggests that fluoridation of drinking water supplies reduces caries prevalence, both as measured by the proportion of children who are caries free and by the mean decayed, missing or filled teeth (DMFT) score 47 The fluoridation of Irish water has had significant impact on the reduction of dental caries, with the most recent studies confirming lower caries rates in children living in fluoridated areas compared to children living in non-fluoridated areas 48 In 2014, ¤3 9 million was spent on water fluoridation with an estimated cost of ¤1 per person per year
In Ireland, fluoride toothpaste is readily available The Cochrane review on fluoride toothpastes provides considerable evidence as to the effectiveness of toothpaste in caries reduction with a child who brushes with fluoride toothpaste having 23% less caries than a child who does not The review, however, only found a reduction in caries for fluoride concentrations of 1,000ppm and above 49
Widespread use of fluoride toothpaste is considered responsible for much of the significant decline in caries since the 1970s 50
There are a number of studies that demonstrate the efficacy of school toothbrushing programmes A study by Jackson et al (2005)51 demonstrated an overall caries rate reduction of 10 9% compared to controls and a study by Pine et al 52 (2007) showed a reduction in the proportion of children with dental decay with a preventive fraction of 0 44 in school-based toothbrushing programmes
Ellwood53 demonstrated that access to toothpaste and toothbrushes was also a factor in reducing caries prevalence When toothpaste containing fluoride at levels of 440ppm or 1,450ppm was posted at three-month intervals to children from the age of one to five years, the children who received the toothpaste had significantly less caries
Marinho et al 54 (2015) recently updated their review on the effectiveness of fluoride gels and showed a 28% reduction in dental caries in permanent teeth, with fluoride gel used once a year to several times a year There was only lowquality evidence to show a reduction in caries of 20% in the primary dentition
A Cochrane review on fluoride varnish55 demonstrated a reduction in dental caries of 37% in primary teeth and 43% in permanent teeth compared to controls These studies included children from as young as 12 months of age The evidence is so strong that HSE guidance recommends fluoride varnish applications for children at high caries risk 48
There are other preventive agents that could be used at an infant oral health visit for high risk children; however, the evidence for their effectiveness is not strong A recent Cochrane review, for example, could not demonstrate that chlorhexidine varnish or gel reduces tooth decay or reduces the bacteria that encourage tooth decay 56 There is some early work looking at the efficacy of probiotics at reducing dental disease, but the evidence is conflicting57 58 and more research is needed before probiotics could be considered as clinically relevant Similarly, casein phosphopeptideamorphous calcium phosphate (CPP-ACP) is also used as a caries-preventive agent, but a recent review by Raphael and Blinkhorn could not find evidence of its efficacy 59
There have been a number of clinical studies looking at the effect of xylitol on dental caries These can be grouped into direct effects (where the xylitol is consumed directly by the person, and its effect on their oral health) and maternal consumption studies (the theory is that by consuming xylitol at a specific point in the child’s life, just before the teeth erupt, that mothers can influence the type of bacteria they pass onto their child) Looking at the evidence for a direct effect of xylitol, Riley et al showed that fluoride toothpaste containing xylitol provided additional benefit, but could not find any conclusive evidence to demonstrate that any other xylitol-containing products could prevent caries 60 Looking at the maternal consumption of xylitol, Lin recently reviewed the evidence and showed a significant reduction in mutans streptococci (MS) transmission in mothers who consumed xylitol 61 However, the evidence is of low to moderate quality 62 A recent paper by Duane63 reported no statistical difference in MS transmission between children whose mothers consumed xylitol and children whose mothers did not However, it is possible that this was because the control group consisted of children who were enrolled in the Childsmile programme
An effective oral health promotion programme for the younger child according to the Ottawa Charter would build healthy public policy, create supportive environments, strengthen community actions, develop personal skills of individuals and reorient health services 64 An oral health promotion programme should be embedded across all health areas including child health teams, community programmes, and dental services Sir Michael Marmot would argue that an oral health promotion programme is not only about education, but would also ensure that every child would have the ability to maximise their capability and have control over their lives 40
In England, parents are encouraged to take their child to the dentist when “their first milk teeth appear” 65 English dental teams are encouraged to follow a preventive programme known as: ‘Delivering better oral health’ 66 The American Academy of Pediatric Dentistry gives similar advice, with parents being encouraged to bring their child to a dentist no later than after their first birthday 67
In Scotland, an oral health improvement programme, Childsmile, in line with the Marmot Review,19,40 has adopted a population/proportionate universalism approach to improve the oral health of its population The programme works both within community dental services targeting schools and nurseries, and all NHS dental practices This programme ensures every child has access from six months of age to Childsmile, with different support offered to targeted groups of children along the life course Within the community all children receive free toothbrushes at various stages before school, with all three and four year olds attending nursery school receiving toothbrushing as part of the nursery programme In areas of higher risk of dental disease, children receive both fluoride varnish programmes and toothbrushing programmes in the first few years of primary school As part of Childsmile, all parents are encouraged to register their baby with a dentist as soon as possible after birth, or by the time they are six months of age 68 Health visitors encourage parents to bring their child to a dentist, and also provide toothbrushes and toothpaste at an early age
In a Childsmile practice the dental team all supports the oral health of a child, with specially trained extended duties dental nurses allowed from the General Dental Council to apply fluoride varnish, and provide oral health resources and oral health education to high-risk children The government provides additional payments to Childsmile practices, including a payment for fluoride varnish to high-risk children The Scottish oral health programme has reduced caries prevalence by half since its inception in 2007, enabling children to start to have comparable oral health status with their English peers 69
In Ireland, no nationwide early oral health programme has been established, and the guidelines developed in collaboration with the HSE and UCC have not been fully implemented 70
Screening, including dental screening, is an integral part of Government-funded health services in Ireland The school-based dental screening service in Ireland enables some children to receive dental care for defects identified It also enables eligible children to gain access to the orthodontic pathway Within the UK, population screening in school-aged children from six to nine years of age was carried out until 2006 At that time, the UK national screening committee
s
recommendation was that screening should stop 42 The US Preventive Services Task Force (USPSTF) believes that the current evidence is insufficient to assess the potential benefits and harms of routine screening examinations for dental caries performed by primary care clinicians in children from birth to five years of age 43
According to the American Academy of Pediatric Dentistry, the dental home is the “ongoing relationship between the dentist and the patient, inclusive of all aspects of oral healthcare delivered in a comprehensive, continuously accessible, co-ordinated, and family-centred way” The dental home should be established at no later than 12 months of age and includes referral to dental specialists when appropriate 71 Using the medical model the dental home concept could be used to improve families’ access to dental care 72
The Dental Council in Ireland states that: “A dentist is best placed within the dental team to provide leadership, develop a vision of patient care, promote integrity, openness and fairness within the dental team and ensure a holistic approach to the patient’s care” 73 Internationally, in recent decades there has
Age of first preventive visit
been a growing use of the team approach, which can be advantageous in the delivery of oral healthcare The General Dental Council in the UK for example has mandatory registration of dental nurses, dental technicians, dental therapists, dental hygienists, orthodontic therapists and clinical dental technicians Within Ireland, it is this team approach that could be very helpful to provide cost-effective dental care for infants Within the UK, for example, dental nurses with extended approved training can provide fluoride varnish as part of an oral health promotion programme 74 In other countries there is an even wider approach to delivering oral health promotion In Ohio, USA, nurse practitioner teams were utilised to increase dental workforce capacity The team trained registered dieticians and nursing students to provide oral health assessments and place fluoride varnish, with a resultant expansion of access to oral health and reduced dental caries 75 Within Scotland, in Childsmile, an important part of the health visitor’s role is to identify children at risk and support their entry into a child oral health pathway 76 The team approach is limited within Ireland due to the Dental Act, which restricts the scope of practice more narrowly than its UK equivalent However, a guidance document ‘Strategies to prevent caries’ has recommended the need for public health nurses, practice nurses, GPs and other primary care workers who have regular contact with young children to have training in the identification of high caries risk preschool children and in completing an oral assessment as part of their child health record 18 This has yet to be implemented nationally
Savage undertook an analysis of the effects of early preventive dental visits on subsequent utilisation and costs of dental services among preschool-aged children 77 The investigation studied a longitudinal cohort of children in North Carolina, coding their care as either preventive or restorative The age of the first visit had a significantly positive effect on dental-related expenditures, with the average dental-related costs being less for children who received earlier preventive care Results need to be interpreted carefully as there are significant biases in their selection Parents who provide an optimal oral health environment in their homes may also, for example, be more likely to access earlier dental care Within this study, children from racial minority groups had significantly more
difficulty in finding access to dental care as did those in counties with fewer dentists per population Lee72 demonstrated the cost-effectiveness of early dental visits (Figure 1)
It was demonstrated that an average total cost of care over five years for a child in US dollars ($) rises from around $250 if a child is seen for prevention before age one, to around $550 if the child is not seen for prevention until aged four to five years
Anopa recently calculated the costs of the Childsmile nursery toothbrushing programme in Scotland to be £1 8 million per year The estimated costs of dental treatment in 2001/2002 were £8 8 million per year, which decreased to £4 7 million by 2009/2010 78 The authors noted that these cost reductions were more than two and a half times the cost of the Childsmile nursery preventive programme implementation
Discussion
From the papers reviewed there are distinct advantages in seeing children in the dental setting from a very young age There is a high-quality body of evidence that children should have early oral health visits, not just for economic reasons but for optimal oral and systemic health This review has demonstrated the evidence for the need to perform a risk assessment, the need for better tailored oral health education (using an MI type approach), with preventive care offered as an integrated oral health promotion plan, either on an individual or population basis
In Ireland, the advice that is given in a preventive care booklet for babies and young children encourages parents to take their baby to the dentist when their first teeth start to appear 79 However, in the HSE, such a service is at present limited to children with special healthcare needs
From an Irish perspective, there would need to be changes made to a number of services to optimise oral healthcare for children A primary care strategy would need development to allow a higher number of children to access care For those children who are not accessing care, and this appears to be most preschool children, systems need to be developed to identify children at high risk of caries, with system changes to enable public health nurses, practice nurses, GPs and other primary care workers who have regular contact with young children to have both training in the identification of high caries risk preschool children and in completing an oral assessment as part of their child health record 18
In addition to a national system of identifying children at risk of caries, pathways need to be developed and funded so that children can receive high-quality education and prevention to improve their oral health Publicly-funded, highquality, evidence-based dental treatments should be available to children for whom preventive care is not entirely successful
This review presents conclusive evidence that investing early in oral health yields lasting dividends It is certainly possible, with appropriate early intervention, to maintain the oral health of the one-year-old child And it is eminently possible to avoid the development of dental caries in the young child and the need for dental treatment under GA or otherwise Introduction of the first dental visit by 12 months of age should be firmly on the health agenda here in Ireland
References
1 McMahon, A.D., Blair, Y., McCall, D.R., Macpherson, L.M. The dental health of three-year-old children in Greater Glasgow, Scotland Br Dent J 2010; 209 (4): E5
2 Public Health England. Dental public health epidemiology programme Oral health survey of three year old children 2013 A report on the prevalence and severity of d e n t a l d e c a y 2 0 1 3 [ A c c e s s e d M
http://www nwph net/dentalhealth/reports/DPHEP%20for%20England%20OH%2 0Survey%203yr%202013%20Report pdf
3 Gussy, M , Ashbolt, R , Carpenter, L , Virgo-Milton, M , Calache, H , Dashper, S , et al Natural history of dental caries in very young Australian children Int J Paediatr Dent 2016; 26 (3): 173-183
4 H e a l t h ( D e n t a l S e r v i c
http://www irishstatutebook ie/eli/2000/si/248/made/en/print) [Accessed May 10, 2016]
5 PA Consulting Group/HSE Strategic Review of the Delivery and Management of HSE Dental Services 2010
6 Irish Dental Association Dental Care in Ireland [Accessed May 10, 2016] Available from: http://www dentist ie/your-oral-health/dentistry-in-ireland 137 html
7 Health and Social Care Information Centre NHS Dental Statistics for England –2 0 1 3 - 2 0 1 4 L o n d o n , U K : 2 0 1 4 [ A
o m : http://www hscic gov uk/catalogue/PUB13531/nhs-dent-stat-eng-2013-14-secquar-rep pdf
8 Department of Health Reference costs 2012 to 2013 London: DH; 2013 [Accessed May 10, 2016] Available from: https://www gov uk/government/publications/nhsreference-costs-2012-to-2013
9 Bridgman, C M , Ashby, D , Holloway, P J An investigation of the effects on children of tooth extraction under general anaesthesia in general dental practice Br Dent J 1999; 186 (5): 245-247
10 Department of Health A Conscious Decision: A Review of the Use of General Anaesthesia and Conscious Sedation in Primary Dental Care London, UK, 2000
11 Robertson, S , Ní Chaollaí, A , Dyer, T A What do we really know about UK paediatric dental general anaesthesia services? Br Dent J 2012; 212 (4): 165-167
12 Brennan, C Varadkar dismisses claims 10,000 Irish children have teeth extracted in hospital each year [cited May 10, 2016] Available from: http://www thejournal ie/ children-teeth-extractions-2389382-Oct2015/
13 Healthcare Pricing Officer Activity in Acute Public Hospitals in Ireland [Accessed May 10, 2016] Available from: http://www hpo ie/latest hipe nprs reports/ HIPE 2014/HIPE Report 2014 pdf
14 Drummond, B.K., Meldrum, A.M., Boyd, D. Influence of dental care on children’s oral health and well-being Br Dent J 2013; 214 (11): E27
15 O’Keefe, E Early childhood caries Evid Based Dent 2013; 14 (2): 40-41
16 Thomson, W M , Poulton, R , Milne, B J , Caspi, A , Broughton, J R , Ayers, K M Socioeconomic inequalities in oral health in childhood and adulthood in a birth cohort Community Dent Oral Epidemiol 2004; 32 (5): 345-353
17 Girish Babu, K L , Doddamani, G M Dental home: Patient centered dentistry J Int Soc Prev Community Dent 2012; 2 (1): 8-12
18 University College Cork. Oral Health Services Research Centre Strategies to prevent d e n
http://www dentalhealth ie/download/pdf/shortguidelines pdf
19 Macpherson, L M , Ball, G E , Brewster, L , Duane, B , Hodges, C L , Wright, W , et al Childsmile: the national child oral health improvement programme in Scotland Part 1: Establishment and development Br Dent J 2010; 209 (2): 73-78
20 Parisotto, T M , Steiner-Oliveira, C , Silva, C M , Rodrigues, L K , Nobre-dosSantos, M Early childhood caries and mutans streptococci: a systematic review Oral Health Prev Dent 2010; 8 (1): 59-70
21 Leong, P M , Gussy, M G , Barrow, S Y , de Silva-Sanigorski, A , Waters, E A
systematic review of risk factors during first year of life for early childhood caries Int J Paediatr Dent 2013; 23 (4): 235-250
22 da Silva Bastos, Vde A , Freitas-Fernandes, L B , Fidalgo, T K , Martins, C , Mattos, C T , de Souza, I P , et al Mother-to-child transmission of Streptococcus mutans: a systematic review and meta-analysis J Dent 2015; 43 (2): 181-191
23 Hooley, M , Skouteris, H , Boganin, C , Satur, J , Kilpatrick, N Parental influence and the development of dental caries in children aged 0-6 years: a systematic review of the literature J Dent 2012; 40 (11): 873-885
24 SIGN 138 Dental interventions to prevent caries in children [Accessed November 22, 2014] Available from: http://www sign ac uk/pdf/QRG138 pdf
25 Kumar, S , Tadakamadla, J , Kroon, J , Johnson, N W Impact of parent-related factors on dental caries in the permanent dentition of 6-12-year-old children: A systematic review J Dent 2016; 46: 1-11
26 Palmer, C A , Kent, R , Loo, C Y , Hughes, C V , Stutius, E , Pradhan, N , et al Diet and caries-associated bacteria in severe early childhood caries J Dent Res 2010; 89 (11): 1224-1229
27 Birch, L L Development of food preferences Annu Rev Nutr 1999; 19: 41-62
28 Henderson, L , Gregory, J , Irving, K , Swan, G The national diet and nutrition survey: adults aged 19-64 years, volume 2: energy, protein, carbohydrate, fat and alcohol intake London: TSO, 2003
29 Hayden, C , Bowler, J O , Chambers, S , Freeman, R , Humphris, G , Richards, D , et al Obesity and dental caries in children: a systematic review and meta-analysis Community Dent Oral Epidemiol 2013; 41 (4): 289-308
30 Skouteris, H , McCabe, M , Swinburn, B , Newgreen, V , Sacher, P , Chadwick, P Parental influence and obesity prevention in pre-schoolers: a systematic review of interventions Obes Rev 2011; 12 (5): 315-328
31 NHS Health Scotland Oral Health and Nutrition Guidance for Professionals (2012) [Accessed January 28, 2015] Available from: http://www healthscotland com/ documents/5885 aspx
32 Kay, E J , Locker, D Is dental health education effective? A systematic review of current evidence Community Dent Oral Epidemiol 1996; 24 (4): 231-25
33 Harris, R , Gamboa, A , Dailey, Y , Ashcroft, A One-to-one dietary interventions undertaken in a dental setting to change dietary behaviour Cochrane Database Syst Rev 2012 (3): CD006540
34 Chaffee, B W , Feldens, C A , Vítolo, M R Cluster-randomized trial of infant nutrition training for caries prevention J Dent Res 2013; 92 (7 Suppl ): 29S-36S
35 Miller, R , Rollnick, S Motivational Interviewing: Preparing People for Change New York: Guildford Press, 2002
36 Curtin, S , Trace, A , Ziada, H , Crowley, E Motivational interviewing for dental clinicians J Ir Dent Assoc 2014; 60 (1): 35-37
37 Yevlahova, D , Satur, J Models for individual oral health promotion and their effectiveness: a systematic review Aust Dent J 2009; 54 (3): 190-197
38 Ismail, A I , Ondersma, S , Jedele, J M , Little, R J , Lepkowski, J M Evaluation of a brief tailored motivational intervention to prevent early childhood caries Community Dent Oral Epidemiol 2011; 39 (5): 433-448
39 Harrison, R L , Veronneau, J , Leroux, B Effectiveness of maternal counseling in reducing caries in Cree children J Dent Res 2012; 91 (11): 1032-1037
40 Marmot, M. UCL Insitute of health Equity: Fairer lives Healthy lives The Marmot Review [Accessed May 10, 2016] Available from: http://www instituteofhealth equity org/projects/fair-society-healthy-lives-the-marmot-review
41 Office of Disease Prevention and Health Promotion Social determinants of health Available from: www healthypeople gov/2020/topics-objectives/topic/ socialdeterminants-of-health
42 UK National Screening Committee. [Accessed May 10, 2016] Available from: http://legacy screening nhs uk/policydb download php?doc 422
43 Moyer, V A , US Preventive Services Task Force Prevention of dental caries in children from birth through age 5 years: US Preventive Services Task Force recommendation statement Pediatrics 2014; 133 (6): 1102-1111
44 Dean, H T Post-war implications of fluorine and dental health: epidemiological aspects Am J Public Health Nations Health 1944; 34 (2): 133-143
45 Clark, M B , Slayton, R L , Section on Oral Health Fluoride use in caries prevention in the primary care setting Pediatrics 2014; 134 (3): 626-633
46 Splieth, C H , Flessa, S Modelling lifelong costs of caries with and without fluoride use Eur J Oral Sci 2008; 116 (2): 164-169
47 Treasure, E T , Chestnutt, I G , Whiting, P , McDonagh, M , Wilson, P , Kleijnen, J The York review a systematic review of public water fluoridation: a commentary Br Dent J 2002; 192 (9): 495-497
48 University College Cork Topical Fluorides Evidence-based guidance on the use of topical fluorides for caries prevention in children and adolescents in Ireland
49 Walsh, T , Worthington, H V , Glenny, A M , Appelbe, P , Marinho, V C , Shi, X Fluoride toothpastes of different concentrations for preventing dental caries in children and adolescents Cochrane Database Syst Rev 2010 (1): CD007868
50 Moore, W J , Corbett, E The distribution of dental caries in ancient British populations II Iron Age, Romano-British and Mediaeval periods Caries Res 1973; 7 (2): 139-153
51 Jackson, R J , Newman, H N , Smart, G J , Stokes, E , Hogan, J I , Brown, C , et al The effects of a supervised toothbrushing programme on the caries increment of primary school children, initially aged 5-6 years Caries Res 2005; 39 (2): 108-115
52 Pine, C M , Curnow, M M , Burnside, G , Nicholson, J A , Roberts, A J Caries prevalence four years after the end of a randomised controlled trial Caries Res 2007; 41 (6): 431-436
53 Ellwood, R P , Davies, G M , Worthington, H V , Blinkhorn, A S , Taylor, G O , Davies, R M Relationship between area deprivation and the anticaries benefit of an oral health programme providing free fluoride toothpaste to young children Community Dent Oral Epidemiol 2004; 32 (3): 159-165
54 Marinho, V C , Worthington, H V , Walsh, T , Chong, L Y Fluoride gels for preventing dental caries in children and adolescents Cochrane Database Syst Rev 2015 (6): CD002280
55 Marinho, V.C., Worthington, H.V., Walsh, T., Clarkson, J.E. Fluoride varnishes for preventing dental caries in children and adolescents Cochrane Database Syst Rev 2013 (7): CD002279
56 Walsh, T , Oliveira-Neto, J M , Moore, D Chlorhexidine treatment for the prevention of dental caries in children and adolescents Cochrane Database Syst Rev 2015 (4): CD008457
57 Stensson, M , Koch, G , Coric, S , Abrahamsson, T R , Jenmalm, M C , Birkhed, D , et al Oral administration of Lactobacillus reuteri during the first year of life reduces caries prevalence in the primary dentition at 9 years of age Caries Res 2014; 48 (2): 111-117
58 Taipale, T , Pienihäkkinen, K , Alanen, P , Jokela, J , Söderling, E Administration of Bifidobacterium animalis subsp lactis BB-12 in early childhood: a post-trial effect on caries occurrence at four years of age Caries Res 2013; 47 (5): 364-372
59 Raphael, S , Blinkhorn, A Is there a place for Tooth Mousse in the prevention and treatment of early dental caries? A systematic review BMC Oral Health 2015; 15 (1): 113
60 Riley, P., Moore, D., Ahmed, F., Sharif, M.O., Worthington, H.V. Xylitol-containing products for preventing dental caries in children and adults Cochrane Database Syst Rev 2015(3): CD010743
61 Lin, H K , Fang, C E , Huang, M S , Cheng, H C , Huang, T W , Chang, H T , et al Effect of maternal use of chewing gums containing xylitol on transmission of mutans streptococci in children: a meta-analysis of randomized controlled trials Int J Paediatr Dent 2016; 26 (1): 35-44
62 Richards, D , Duane, B , Sherriff, A Maternal consumption of xylitol for preventing dental decay in children Cochrane Database Syst Rev 2012: CD010202
63 Duane, B Improving oral healthcare in Scotland with special reference to sustainability and caries prevention [Doctoral thesis] 2015
64 World Health Organisation Ottawa Charter for Health Promotion (1986) [Accessed
promotion/conferences/previous/ottawa/en/
65 N H S C h
www nhs uk/livewell/dentalhealth/pages/careofkidsteeth aspx
66 Public Health England Delivering better oral health: an evidence-based toolkit for p
https://www gov uk/government/publications/delivering-better-oral-health-anevidence-based-toolkit-for-prevention
67 American Association of Pediatric Dentistry Frequently Asked Questions [ A c c e s s
frequently asked questions/#311
68 NHS Scotland Childsmile at the dentist [Accessed May 10, 2016] Available from: www child-smile org uk/parents-and-carers/Childsmile-at-the-dentist aspx
69 Deery, C , Owen, J , Welbury, R , Chadwick, B Dental caries in children and the level of repeat general anaesthetics for dental extractions A national disgrace Dent Update 2015; 42 (4): 305-306
70 University College Cork Irish Oral Health Services Guideline Initiative [Accessed September 6, 2016] Available from: https://www ucc ie/en/ohsrc/guidelines/
71 American Association of Pediatric Dentistry Definition of Dental Home [Accessed M a y 1 0 , 2 0 1 6 ] A v a i l
policies guidelines/d dentalhome pdf
72 Lee, J Y , Bouwens, T J , Savage, M F , Vann, W F Examining the cost-effectiveness of early dental visits Pediatr Dent 2006; 28 (2): 102-105; discussion 92-98
73 Dental Council Ireland Scope of Practice [Accessed October 6, 2016] Available f r o m : h t t p : / / w w w
%20Guidance%20(approved)%20-%2020141203 pdf
74 Gnich, W , Deas, L , Mackenzie, S , Burns, J , Conway, D I Extending dental nurses’ duties: a national survey investigating skill-mix in Scotland’s child oral health improvement programme (Childsmile) BMC Oral Health 2014; 14: 137
75 Biordi, D.L., Heitzer, M., Mundy, E., DiMarco, M., Thacker, S., Taylor, E., et al Improving access and provision of preventive oral health care for very young, poor, and low-income children through a new interdisciplinary partnership Am J Public Health 2015; 105 (Suppl 2): e23-e29
76 Scottish Government. Universal Health Visiting Pathway in Scotland [Accessed May 11, 2016] Available at: http://www gov scot/Resource/0048/00487884 pdf
77 Savage, M F , Lee, J Y , Kotch, J B , Vann, W F Early preventive dental visits: effects on subsequent utilization and costs Pediatrics 2004; 114 (4): e418-e423
78 Anopa, Y., McMahon, A.D., Conway, D.I., Ball, G.E., McIntosh, E., Macpherson, L M Improving Child Oral Health: Cost Analysis of a National Nursery Toothbrushing Programme PLoS One 2015; 10 (8): e0136211
79 Health Service Executive Dental Care for Babies and Children [Accessed May 10 2016] Available at: https://www hse ie/eng/health/az/D/Dental-care-for-babiesand-children/
A randomised controlled clinical trial comparing small buccal dehiscence defects around dental implants treated with guided bone regeneration or left for spontaneous healing
Jung,
R E , Herzog, M , Wolleb, K , Ramel, C F , Thoma, D S , Hämmerle, C H
Purpose: The aim of the present randomised controlled clinical study was to test whether small bony dehiscence defects (≤5mm) left to heal spontaneously result in the same clinical and radiological outcome as defects treated with guided bone regeneration (GBR)
Materials and methods: A total of 22 patients who received at least one implant with a small bony dehiscence defect were enrolled in the study If the defect height was ≤5mm, the site was randomly assigned to either the spontaneous healing (SH) group or the GBR group In the SH group, the defect was left without any treatment In the GBR group, the defects around the implants were grafted with deproteinised bovine bone mineral (DBBM) and c
measurements were performed six months after implant placement, with a reentry surgery at the time of crown insertion and the subsequent follow-up appointments at three, six, 12 and 18 months after loading For statistical analyses, the mixed linear model was applied for the clinical and radiographic measurements observed around the implants Simple comparisons of the location of the measurements in the two independent groups were performed with the Mann-Whitney U-test In addition, the mixed model assumptions were checked
Results: The implant and crown survival rate 18 months after loading was 100%, revealing no serious biologic or prosthetic complication The mean changes of the buccal vertical bone height between implant placement and re-
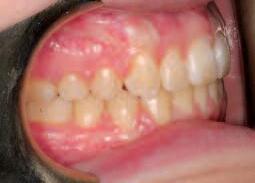
Questions on page 62
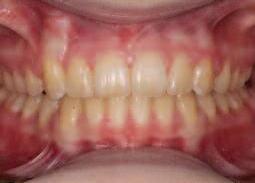
1 i) Observe for the presence of buccal or palatal bulge; ii) palpate the buccal sulcus and palatal surface in the canine region to locate canine bulge; and, iii) inspect the inclination of the maxillary lateral incisors The canine can place pressure on the lateral incisor root, which can result in tipping of crowns If the crown is inclined buccally, the canine is likely to be buccal If the crown is tipped palatally, the canine is likely to be palatal
2 Parallax technique: the apparent movement of an object as a result of the actual movement of the radiograph tube If the object moves in the same direction as the radiograph tube, it is considered lingual (palatal) If the object moves in the opposite direction to the radiograph tube, it is considered buccal This is the same lingual, opposite buccal, or SLOB, rule
entry surgery after six months revealed a small bone loss of -0 17 ± 1 79mm (minimum -4mm and maximum 2 5mm) for the SH group and a bone gain of 1 79 ± 2 24mm (minimum of -2 5mm and maximum of 5mm) for the GBR group, respectively (P = 0 017) Radiographic measurements demonstrated a slight bone loss of -0 39 ± 0 49mm for the SH group and a stable bone level of 0 02 ± 0 48mm for the GBR group after 18 months All peri-implant soft tissue parameters revealed healthy tissues with no difference between the two groups
Conclusion: Small bony dehiscence defects left for SH demonstrated high implant survival rates with healthy and stable soft tissues However, they revealed more vertical bone loss at the buccal aspect six months after implant insertion and also more marginal bone loss between crown insertion and 18 months after loading compared to sites treated with GBR
Clin Oral Implants Res 2017; 28 (3): 348-354
Periodontitis and incident type 2 diabetes: a prospective cohort study
Winning, L , Patterson, C C , Neville, C E , Kee, F , Linden, G J
Objectives: The aim of this study was to investigate periodontitis as a risk factor for incident type 2 diabetes mellitus (T2DM) in a group of men aged 5872 years
Methods: One thousand three hundred and thirty-one dentate, diabetes-free men in Northern Ireland underwent a detailed periodontal examination during 2001-2003 Follow-up was by biannual questionnaire and for those reporting diabetes their general medical practitioner was contacted to validate diabetes
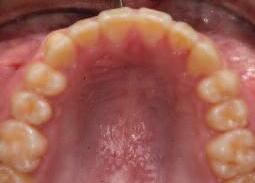
3 Parallax can be performed in a vertical or horizontal dimension To perform a vertical parallax a maxillary anterior occlusal (65°) and an OPG (7°) are used The radiographic tube moves down vertically Horizontal parallax can be performed using two periapicals with a 30° shift between them, in the horizontal plane It can also be accomplished by comparing a periapical (taken at 65°) and a maxillary anterior occlusal
4 When comparing their position in the maxillary anterior occlusal radiograph and in the OPG, both canines have moved coronally relative to the maxillary lateral incisor The radiographic tube has also moved coronally (down)
When applying the SLOB rule we ascertain that both canines are ectopic in a palatal position
The canines were surgically exposed and aligned as part of fixed appliance therapy
type, treatment and diagnosis date Cox’s proportional hazard models were used to estimate the effect of periodontitis on incident diabetes Multivariable analysis included adjustment for various known confounders
Results: The mean age of the men was 63 7 (SD 3 0) years There were 80 cases (6 0%) of incident T2DM Follow-up was for a median period of 7 8 years (IQR 6 7-8 3) After adjusting for confounding variables, the hazard ratio (HR) for incident T2DM in men with moderate/severe periodontitis versus those with no/mild periodontitis was 1 69 (95% CI 1 06-2 69), p = 0 03
Conclusion: There was evidence in this homogenous group of dentate men, that those with moderate to severe periodontitis had a significantly increased risk of incident T2DM
J Clin Periodontol 2017; 44 (3): 266-274
Quality of life changes in children following emergency dental extractions under general anaesthesia
Wong, S , Anthonappa, R P , Ekambaram, M , McGrath, C , King, N M , Winters, J C
Objectives: To assess the changes in the oral health-related quality of life (OHRQoL) of 221 preschool children who presented to the emergency department with the consequences of untreated dental caries requiring dental extractions under general anaesthesia (DEGA)
Methods: Two hundred and twenty-one healthy preschool children, who required emergency DEGA, were recruited over a period of 12 months Each child’s parent or caregiver completed the early childhood oral health impact scale (ECOHIS) questionnaire, both prior to the DEGA and at the two-week post-treatment visit Data were analysed using repeated ANOVA with adjustments for multiple comparisons using the Bonferroni tests, with the significance level set at 5%
Results: In total, 126 participants, with a mean age of 4 02 and a mean decayed, missing or filled teeth (DMFT) score of 8 27 (SD = 4 13), completed the two-week post-treatment questionnaires The overall ECOHIS, CIS, and FIS s
demonstrating large effect sizes The biggest decrease in prevalence after emergency DEGA was observed for the items of pain in teeth, trouble sleeping, being irritated or frustrated, difficulty drinking food, and parents being upset
Conclusions: The OHRQoL of preschool children who presented to the emergency department with the consequences of untreated dental caries was significantly improved following emergency DEGA
Int J Paediatr Dent 2017; 27 (2): 80-86
A qualitative investigation into patients’ perspectives on edentulousness
Meaney, S , Connell, B O , Elfadil, S , Allen, F
Objectives: This study explored the experiences of edentulous patients for their perceptions of tooth loss and patient attitudes to treatment options for
rehabilitation of the edentate state
Methods: Purposive sampling was used to recruit edentate patients with varying denture-wearing experience from two dental hospitals in the Republic of Ireland Sixteen edentate patients, aged 59 to 83 years, of whom 12 were women and four men, were interviewed Interviews were transcribed, and thematic analysis was undertaken
Results: Findings from this study reflect previous studies, whereby some patients indicated dissatisfaction with the functionality of their dentures The majority of participants had no regret regarding the loss of their teeth, and despite dissatisfaction with dentures, they would not consider other forms of treatment Finance was not considered an issue in determining whether to seek out treatment by these participants These participants expressed a reluctance to get new dentures in case they were more problematic
Conclusion: This study illustrates that some elder edentate patients were dissatisfied with the functionality of their dentures and raised concerns about the quality of dentures which may be provided to them by dentists These participants identified clinical dental technicians as a preferred point of contact for their care Consideration should be given to new oral healthcare delivery models which are accessible and acceptable to future elders
Gerodontology 2017; 34 (1): 79-85

SITUATIONS WANTED
Gentle, kind and very caring general dentist is looking for an opportunity Special interest and strong experience in paediatric dentistry Dublin area preferred Email happytoothdublin@gmail com
V
Kerry/Limerick/Cork Based in Kerry Email kerrydentist21@gmail com
Enthusiastic, friendly and hardworking dentist (certified implantologist) based in Dublin, looking for a part-time position in Dublin, long experience in prosthetic and surgical treatments Contact wisdomtooth111@gmail com
Motivated female dentist with five years ' experience available for full/parttime work in the Cork/Kerry area Available from April onwards Email corklocumdentist@gmail com
SITUATIONS VACANT
Dentists
Strabane – Fantastic opportunity for a general dentist to join our wellestablished practice in Strabane Position offers an existing list and modern working environment three to five days per week Candidates must be General Dental Council (GDC) registered To apply email tina thomas@oasis dentalcare com
Shannon: experienced general practitioner required for newly-built dental clinic in Skycourt Shopping Centre Excellent staff and equipment OPG, digital radiographs, etc Must be hardworking and flexible with good level of CPD Email shannon@alexandradental ie for more information, or call 061-315 228 Work in Newfoundland, Canada An opportunity to practise in a beautiful, clean province that is a short plane ride from home We have a Trinity College
g
officemanager@nf aibn com
Advertisements will only be accepted in writing via fax (01-295 0092), letter or email (fionnuala@irishdentalassoc ie) Non-members must pre-pay for advertisements, which must arrive no later than May 10, 2017 Classified ads placed in the Journal are also published on our website www dentist ie for 12 weeks
Advert size Members Non-members up to 25 words ¤80 ¤160 26 to 40 words ¤95 ¤190
The maximum number of words for classified ads is 40
If the advert exceeds 40 words, then please contact: Think Media, The Malthouse, 537 North Circular Road, Dublin 1 Tel: 01-856 1166 Fax: 01-856 1169 Email: paul@thinkmedia ie
Please note that all classified adverts MUST come under one of the following headings:
4 Positions Wanted 4 Positions Vacant
4 Practices for Sale/To Let 4 Practices Wanted
4 Equipment for Sale/To Let
Classified adverts must not be of a commercial nature Commercial adverts can be arranged by contacting Paul O’Grady at Think Media
:
Part-time dentist required, in our longstanding, small, general dental practice in north Dublin The days are Wednesday, Thursday and Friday Please email th andrianos@hotmail com with CV
Co Galway Full-time dentist position available Monday to Friday with the odd S
seaportdental@hotmail com
Part-time dentist required for family practice in Glasnevin Mainly private Initially one day going to two days Possibility of becoming a partner after one year Email orthosull@gmail com
Full-time dentist required for busy city centre surgery to cover maternity leave in our mixed practice with a view to a permanent position in our fully private digital practice Email: smile@rdent ie
Dentist required for new practice in Wexford town – state-of-the-art facilities/full back-up – CV to southeastdental46@gmail com please
Deansgrange Dental Clinic has a fantastic opportunity for an experienced general dentist in a state-of-the-art facility to replace a colleague Private practice with ortho, implant, hygiene and general dentistry CBCT, 3D printer, Cerec, etc Applications to careers@deansgrangedental ie
Dentist for Co Clare practices, established 20 years, very modern clinics, digital OPG/xrays, computerised Must be willing to travel between Ennis and Kilrush (main centre is Kilrush) Large GMS/private list, would suit part-time or full-time Email niallmcrty@gmail com
Experienced dentist, well-established dental practice Excellent location, full patient list Highly experienced dental nurses in place Busy practice located in south Dublin city centre Email julie@omalleyhr ie
Dentist wanted for Tuesday afternoon/evening slot 2 00pm-8 00pm Busy private practice in southwest Dublin Room to increase hours if we find the right candidate Modern practice with high clinical standards Email mayberrydentalcare@gmail com
technologically advanced Co Galway practice with excellent support team Email CV and letter of application to fiacloirconagaillimhe@gmail com
Dublin – Exciting opportunity for an enthusiastic, experienced general dentist to join our modern, well-equipped, well-established Smiles Dental practice in Waterloo Road, Dublin 4 Position offers existing patient list and five days per week Candidates must be IDC registered Email joanne bonfield@smiles co uk
Dentist required for busy 60:40 (private:GMA) practice in Kilkenny city Fulltime, ideally immediate start Email dentistkilkenny@gmail com
Dentist wanted for two to three days per week in growing surgery located in Dunboyne Immediate start Please contact pklinowski@gmail com with a CV
Dublin – Exciting opportunity for an enthusiastic general dentist to join our modern, well-equipped, well-established Smiles Dental practice in Tallaght Position offers five days per week Candidates must be experienced and IDC
joanne bonfield@smiles co uk
Co Wicklow – Smiles Dental is looking for a passionate dentist to join our state-of-the-art practice in Bray Established practice offers modern facilities and is fully computerised Must have experience and be IDC registered Financial joining incentive available Email joanne bonfield@smiles co uk
Dentist required to take over list of retiring principal in a very busy west Cork practice Email with CV to sgdentistlongford@gmail com
Enthusiastic dentist required for newly established practice Cavan town Immediate start, Private/GMS/SW Computerised, digital, state-of-the-art
orthodontics Experience and IDC registration essential Submit CV to info@mcgarritydental ie
Dentist/Managing Clinical Director needed in rural northwestern Canada Must be proficient in molar endodontics, surgical extractions, complete/partial dentures, crowns Graduates from 2012 eligible to apply Annual basic salary: ¤80,000 with benefits Work/immigrant visa sponsorship available Email northerndentalcentre@gmail com
Exciting opportunity for an enthusiastic general dentist to join our modern, well-equipped and well-established practice in north Dublin Part-time position for three days a week Wednesdays, Thursdays and some Saturdays till 2 00pm Candidates must be experienced and IDC registered CVs to Michelle Teeling@smartdentalcare co uk
Dublin – weekend work – exciting opportunity for an enthusiastic general dentist to join our modern, well-equipped, well-established Smiles Dental practices in Dublin Position offers Saturdays and/or Sundays Candidates must be IDC registered Email joanne bonfield@smiles co uk
Dún Laoghaire – Smiles Dental has an exciting opportunity for a passionate dentist to join our brand new state-of-the-art practice in Dun Laoghaire Must be experienced and IDC registered Guaranteed earning for the first few months Email joanne bonfield@smiles co uk
Clondalkin Dental is looking for a passionate dentist with implant and oral surgery experience to join our brand new practice with modern facilities, fully computerised with digital x-rays and CT scanner Must have experience and be IDC registered Email anne@clondalkindental ie
Associates
Experienced associate with a view required to replace departing colleague of eight years in busy, long-established, multi-surgery practices in northwest (short commute from Sligo) Great team, very high turnover Fully developed book CVs to northwestdentaljob1@gmail com
A growing dental practice based in Dublin looking for an experienced, motivated and passionate dentist to join our team IDC a must Preferable e x p e r i e n c e w o r k i n g w
eslattery@onsiteservice com
Dental associate position available one day a week in the south-east Brand new a-dec chair Digital OPG and intra-oral Qualified staff Hygienists Visiting specialist Mixed practice Very relaxed and friendly Please email adecdental365@gmail com
North west Ireland Dynamic, flexible, self-motivated and experienced associate required Immediate start Full week Busy, well-equipped practice Knowledgeable and supportive staff Excellent figures with good earning p o t e n t i a l E m a i l w i t h C V a n d p e r s o n a l p r
o rachelmccafferty71@gmail com
Full-time dental associate required for a practice in the greater Dublin area Fulltime position in a modern, computerised practice with excellent support staff
Full book and great earning potential Email laura cowman@dentalcareireland ie
Dental associate position available in south Co Meath Modern, computerised practices with digital x-rays Full-time or part-time position Email with CV and personal profile to meathdentist@gmail com
Experienced associate with a long-term view required to replace departing colleague of three years in busy, computerised, long-established multisurgery practice in Ennis Great team, great support Initially part-time CVs to
gbrowne ennis@gmail com
Experienced, enthusiastic associate with great people skills required in busy, progressive practice in Gorey Long-term view required Great team, great support OPG, hygienist, computerised Four days a week to start CVs to info@ocdental ie
Experienced and enthusiastic dental associate required in busy multidisciplinary Donegal practice Digital radiographs, OPG equipment, Kodak CBCT scanner, CEREC equipment High commission rate Apply to josephbonner@me com
Clonmel, Co Tipperary Experienced associate required for maternity leave
Long-established, busy practice Currently two days per week, potential to increase Modern computerised surgeries, digital radiographs, hygienists, excellent staff Good earning potential Must be hard working, enthusiastic and friendly April start Email locumclonmel@gmail com
Part-time associate required for fully computerised, modern and predominantly private practice in Dublin 3 Experienced nurses and dental hygienist available Enthusiastic candidate required Email pauleggles@gmail com
Motivated and experienced associate to take over full book in busy, longe
opportunity CVs to westmeathdentist@gmail com
Enthusiastic associate needed part-time for state-of-the-art practice in north Wicklow Must be prepared to work at least one late evening and Saturday mornings Minimum three years ' post-qualification experience and IDC registered Email CV to dentaljobnorthwicklow@gmail com
Kilkenny City Part/full-time (four to five days, flexible) associate – modern computerised practice located in a primary care centre OPG, hygienist, oral surgeon Email ayrfielddentalpractice@gmail com
Experienced associate required for a very busy north Cork practice Friendly w o r k e n
northcorkdentist@gmail com
Dental associate required in busy modern SW Dublin practice (just off M50) to assist existing dental associate Starting end April part-time and for three full weeks in July-August Please contact Wendy on wmunroe@eircom net
Experienced and enthusiastic associate required for busy, well-equipped and computerised practice in Westmeath 30 minutes from M50 Excellent team support and remuneration Private/GMS General practice experience IDC registered essential Email info@kinnegaddental ie
Dental associate required for practice situated on Co Wicklow/Co Carlow border Modern practice with digital x-rays, computerised records and rotary endodontics Part-time position of two days per week (days flexible) and some Saturdays per month (Saturdays all private patients) Must have IDC number Queries to Ldental99@yahoo ie
Associate dentist (experienced) to work two days per week or full-time if preferred with view to purchase Letterkenny, Co Donegal Past experience of working in Ireland or UK essential CV to adrianmillen@tiscali co uk
Dentist required as locum from March 6 to April 3 Mondays, Tuesdays, Fridays For more information, email alex@whitesmiledental ie, or Tel: 087-050 6633
Locum dentist required in Limerick practice from June 2017 to January 2018 for maternity cover Please email CV to cornmarketdental@gmail com
Locum dentist to cover principal on maternity leave, mid-May Private practice Digital radiographs, OPG, CBCT, Exact software Possibility of continued hours in the future after maternity cover Experience mandatory, good
attitude and eagerness to learn Email drodonovan@alexandradental ie
Specialist/limited practice
Canada – St John's, Newfoundland Paediatric dentist needed NOW Looking for a dynamic, energetic and exceptionally motivated paediatric dentist to join LOL dental, paediatric dentistry and orthodontics Part-time or full-time
Renumeration: $1,200 per day guaranteed (Canadian funds) or 35% of net collection Contact drlynanaseri@gmail com
Endodontist required part-time in general/specialist practice in southeast – 50 minutes by M50 – prosthodontist, orthodontist, oral surgeon/implants on s i t e – d a y s / h o u r s t o s u i t – f u l l b a c
southeastdental46@gmail com in confidence
Specialist orthodontist to join a thriving, modern, busy, primary care centre
Existing orthodontic list, increasing and expanding rapidly Immediate start, west Dublin Great support staff Excellent remuneration Flexible hours
Reply to positionspecialist@gmail com
Orthodontist wanted to join specialist practice in Co Wicklow One day per fortnight initially with view to increasing Reply to louisdevereux@msn com
Wanted – oral surgeon to replace departing colleague in an existing, modern, specialist practice in Galway Part-time Long-established book Email paul@paulmccabe ie
Dental nurses/practice managers/receptionists
Fantastic opportunity for an experienced dental nurse Busy clinic working in different locations around Dublin Wide range of dental procedures Great opportunity to learn from experienced dentists and improve your current skills Email eslatter@onsiteservice com
P r a c t i c e m a n a g e r w a n t e d f o r s o u t h s i d e d e n
(www thefreshbreathclinic ie) Dental nursing experience is mandatory Exact SOEUK computer experience preferable Full-time job with immediate start
Please send CV to tfbc16@gmail com
Full-time dental nurse required for practice in Dublin 18 to include a half-day on Saturday Please email CV to admin@cdpractic com
We are looking for a part-time dental nurse to work 30 to 34 hours per week in our busy specialist dental practice in Dublin This position is to start in March
Please email your CV to Michelle Teeling@smartdentalcare co uk
Nurse receptionist required for top-class, busy, progressive practice in the south east Must be a professional, enthusiastic, caring, empathic team player w i t h g r e a t p e o p l e s k i l l s I T s k i l l s c
o d renumeration, high job satisfaction Contact info@ocdental ie
Full- or part-time experienced dental nurse required for dynamic and friendly p r a c
C o
weneedadentalnurse@gmail com
Part-time/full-time dental nurse required for a busy, modern, computerised, award-winning dental practice in Co Meath (approximately 40 minutes north of Dublin) We are looking for a highly motivated individual to join our professional team Contact dentaljobireland1@gmail com
Deansgrange Dental Clinic requires a full-time nurse in a busy, modern dental practice based in south Co Dublin Experience preferred Please send cover letter and CV to careers@deansgrangedental ie
Dental nurse required for award-winning south Dublin practice We look forward to hearing from you CV to rosemary@eircom net
Receptionist required four to five days per week in busy practice on Main St,
Dundrum SOE/Exact experience preferable but not essential Please reply with CV to dr moroney@dentalclinic ie
Part-time qualified dental nurse required to work initially on Fridays in busy practice on Main St, Dundrum Please reply with CV to dr moroney@dentalclinic ie
Full-time dental nurse/receptionist required, city centre practice, Cork Reply by email to aidanmon@eircom net
Full-time qualified dental nurse (experience desirable but not essential) required in the Cork city area to join dynamic and friendly orthodontic practice Apply to info@corkclinicorthodontics com We look forward to hearing from you
Booterstown dental practice requires an experienced dental nurse Full- and part-time position available Great location next to the DART line Forward CV to booterstowndentalpractice@gmail com
Dental nurse required part-time for a busy modern practice in Ennis Email gbrowne ennis@gmail com
Part-time hygienist required in Spiddal Initially one day every two weeks
Minimum contract of one year Minimum of ¤170 earnings per day Email lod@orthocosmetics ie
Full time dental hygienist required for large, friendly and relaxed north Dublin practice Good salary guaranteed for working a four-day week (not including S
balbriggandentalcare@mail com
communication skills and enjoy working as a team Modern practice, digital x-rays, etc Emails only please to dentalpracticekildare@gmail com
Experienced hygienist (two to three years) required for modern, awardwinning, state-of-the-art clinics in Dublin city centre Initially part-time and maternity cover with a view to long-term Email hello@docklandsdental ie Deansgrange Dental Clinic requires a full-time hygienist in a busy, modern dental practice based in South County Dublin Experience preferred but not essential, new grads are welcome to apply Please send cover letter and CV to careers@deansgrangedental ie
Dental hygienist required for sessions in a busy multi-surgery practice in Midleton, Co Cork Must have gentle hands and the ability to put patients at e a s e
carmel@corabbeydentalclinic ie
A dental suite comprising two surgeries, with separate sterilisation, available to lease in busy primary care centre in Blessington Suitable for start-up or relocation Large catchment area in commuter distance of Dublin Please respond to andrewcox204@gmail com
Naas, County Kildare Three treatment rooms to let in existing dental surgery Suit dental specialist Recent renovation, air-conditioned, lift access to upper floors Flexible terms Email info@naasdentalcentre ie
Established state-of-art three- to four-surgery private practice for sale in Cork area Specialist skills a bonus All modern equipment and digital radiographs Email claire ring@smilesandmore ie
Co Donegal Long-established dental practice for sale Two full-time dentists Owner retiring Enquires: forsale dentalsurgery@gmail com
Fantastic opportunity Bright, newly-refurbished unit in prominent location,
Dr Eimear Norton is a paediatric dentist in practice at Clonmel Children's Dental Clinic in Co
T ipperary She is a member of the South East Branch of the IDA
What led you to first get involved in the IDA?
After I graduated I went to work in Kilkenny and my principal dentist, Dr Roger Ryan, highly recommended that I join the IDA and brought me along to my first meeting The South East Branch is a very strong, social branch so it was great to meet other dentists working in the area It's hugely reassuring to talk to colleagues and see that we ' re all experiencing the same issues
What form did that involvement take?
As a general dentist, my involvement was fairly passive; I would go to meetings and conferences but I wouldn't say a word Later, I left general practice and went back to college for three years to qualify in paediatrics, and during that time I didn’t have a lot of involvement with the IDA When I graduated I moved back to Clonmel and set up my practice, and at that stage I became more active I joined the committee and took turns as Treasurer and Chairperson of the Branch It was hugely rewarding I can now say that I appreciate the work that goes into organising and chairing meetings Being on the committee forces you to engage with everybody It takes you out of your comfort zone, but I now have friends from that time that I might not have otherwise
What is your involvement now?
I m not on the committee now – I m too busy at the moment with my own children and my practice! But I do go to the meetings and the Annual Conference, and I'm a lot more active at them; I'm not afraid to speak up anymore I'm also very lucky to be regularly invited to speak on paediatric topics at meetings and I enjoy that
What has your involvement in the IDA meant to you?
Since I set up my own practice the support services that the IDA offers have been fantastic The resources available on practice management, interpreting legislation, radiology, data protection, HR, etc , are really excellent All the information you could need is there, both on the website and on the phone if you need it
What has been the single biggest benefit of IDA membership for you?
Socially it's invaluable Nothing else allows you to engage with colleagues over a cup of tea and discuss the happenings of the wider dental world For me, that's probably the most important part of it
How would you like to see the Association progress into the future?
I would love to see the Association progress even further at local level, but that's up to members – we are only as strong as our members and people need to go to meetings and get involved I also hope that the IDA will keep building the supports available on the website – I know that they are growing all the time
Finally, I hope that the Association will continue to advocate for our patients to Government and in the media It's so important to let the wider public know about dental and oral health issues Recent campaigns about the number of children undergoing extractions under general anaesthetic and the focus on dental health in older people in nursing homes are excellent examples of the IDA in action
The IDA has the power to advocate on our behalf There are a lot of 'alternative facts' out there about dentistry, so it's important that these oral health campaigns have the weight of the IDA behind them – I'm delighted that it's happening
Eimear is originally from Kilkenny, and when she's not looking after the dental health needs of the children who visit her practice in Clonmel, she's kept busy taking care of her own two children, Niamh, who's two, and John, who's seven months old She finds that running her own practice helps to deal with the pressures of being a working parent, as it gives her the freedom to structure her hours more flexibly She also does a bit of running when she gets the time, although not as much as she'd like