







There are two simple ways to request information about the products and services found in Physicians Office Resource.
1. Go to www.PhysiciansOfficeResource.com and enter the four-digit reference number found next to the product or service into the search field, then request additional information, schedule a demo, or speak with a sales agent all with just a simple click of a button.
2. Find the Business Reply Card in this issue, circle the desired reference numbers, complete the form, and drop into any USPS mailbox. A representative will contact you as quickly as possible to answer your questions.
PUBLISHED BY Medical Education Resources, LLC
PUBLISHER
Aaron R. Medaris amedaris@physiciansofficeresource.com
CEO
Andrew C. Nimmo acnimmo@physiciansofficeresource.com
PRESIDENT
John D. Pasquale jpasquale@pharmaconnect.com
BUSINESS MANAGER
Marci J. Hills mhills@physiciansofficeresource.com
TRAVEL EDITOR
Brandi L. Brower
EDITORIAL BOARD
Shakeel Ahmed, MD
Barry Craig, MLT (NCA), CLC
STAFF WRITER
Dylan J. Chadwick
CREATIVE DIRECTOR PRODUCTION MANAGER
Jessica Elmer
Copyright ©2026
To continue your free subscription of Physicians Office Resource magazine, please fill out the Business Reply Card (BRC) located within this magazine and drop in any United States Post Office mailbox.
If you are a manufacturer of medical products or provide services to medical professionals and would like to advertise your products or services to the nation’s top physicians doing in-office testing, call 801-380-6094 or visit: POR.io for more information.



LeadCare® II brings CLIA-waived blood lead testing directly to the point-of-care — so you can test, educate, and take action in a single visit. For pediatric practices, every well-child visit is an opportunity to protect a child’s development. With rapid, quantitative results in just three minutes from a simple fingerstick, you can counsel families and initiate next steps immediately — turning screening into meaningful action when it matters most.
23
IBS vs. IBD: Distinguishing Functional and Inflammatory Bowel Disorders
Gastrointestinal complaints remain among the most common reasons for visits in primary care, with abdominal pain, bloating, and altered bowel habits frequently driving evaluation.
CLIA-Waived Diagnostics: How Speed and Accuracy Transform Clinical Decision-Making
Primary care physicians today operate at the intersection of clinical complexity, patient expectations, and increasing pressure to deliver efficient, evidence-based care.
Screening for Iron Deficiency, Lead & Anemia: What's New?
Screening for iron deficiency, anemia, and lead exposure remains a foundational component of preventive care in primary care practice, particularly across pediatrics, women’s health, and vulnerable populations.




Gastrointestinal complaints remain among the most common reasons for visits in primary care, with abdominal pain, bloating, and altered bowel habits frequently driving evaluation. Among the most commonly encountered diagnoses are irritable bowel syndrome (IBS) and inflammatory bowel disease (IBD)—two conditions that share overlapping symptoms but differ profoundly in pathophysiology, diagnostic approach, prognosis, and management.
For primary care physicians, the ability to distinguish between IBS and IBD is critical. IBS is a functional gastrointestinal disorder without structural or biochemical abnormalities detectable on routine testing, while IBD encompasses chronic, immune-mediated inflammatory conditions that can lead to progressive intestinal damage and systemic complications. Misclassification can delay appropriate therapy in IBD or lead to unnecessary testing and anxiety in IBS.
This article provides a comprehensive overview of IBS and IBD, highlighting their differences and offering a detailed discussion of each condition’s subtypes, clinical presentation, diagnostic strategies, and treatment approaches.
At a high level, IBS and IBD represent two ends of the gastrointestinal disease spectrum.
IBS is classified as a disorder of gut-brain interaction. It is characterized by chronic abdominal pain associated with changes in bowel habits—without evidence of inflammation, mucosal damage, or structural pathology. Symptoms are often influenced by diet, stress, and visceral hypersensitivity, and while IBS can significantly impact quality of life, it does not increase mortality or lead to long-term intestinal injury.
In contrast, IBD—including Crohn’s disease and ulcerative colitis—is marked by chronic inflammation of the gastrointestinal tract. This inflammation is driven by dysregulated immune responses in genetically susceptible individuals and can result in mucosal ulceration, fibrosis, strictures, fistulas, and increased risk of colorectal cancer. Unlike IBS, IBD often presents with systemic features such as weight loss, anemia, and fatigue. Clinically, distinguishing between the two requires careful attention to “alarm features.”
While IBS patients typically present with intermittent symptoms and normal laboratory findings, IBD patients often exhibit objective signs of inflammation such as elevated inflammatory markers, fecal calprotectin, or endoscopic abnormalities.
Pathophysiology and Overview
IBS is a multifactorial condition involving altered gut motility, visceral hypersensitivity, immune activation at a low level, and disruptions in the gut microbiome. Increasing evidence highlights the role of the gut-brain axis, with bidirectional signaling between the central nervous system and enteric nervous system contributing to symptom generation.
Psychological stress, prior gastrointestinal infections (post-infectious IBS), and dietary triggers—particularly fermentable carbohydrates—are frequently implicated.
IBS is classified into subtypes based on predominant bowel habits:
• IBS with constipation (IBS-C)
• IBS with diarrhea (IBS-D)
• IBS with mixed bowel habits (IBS-M)
• IBS unclassified (IBS-U)
These subtypes are not static; patients may shift between them over time, which has implications for treatment selection.
The hallmark of IBS is recurrent abdominal pain associated with defecation or changes in stool frequency or form. Patients commonly report bloating, gas, and a sensation of incomplete evacuation. Pain is often crampy, varies in location, and may improve or worsen with bowel movements.
Importantly, IBS does not typically present with nocturnal symptoms, unintentional weight loss, gastrointestinal bleeding, or significant laboratory abnormalities. The presence of these features should prompt evaluation for alternative diagnoses, including IBD.
IBS is a clinical diagnosis based on symptom criteria, most commonly the Rome IV criteria, which require recurrent abdominal pain at least one day per week in the last three months, associated with at least two of the following:
• Related to defecation
• Associated with a change in stool frequency
• Associated with a change in stool form
Routine diagnostic testing should be limited in the absence of alarm features. However, targeted testing—such as celiac serology, inflammatory markers, or fecal calprotectin—may be appropriate to exclude organic disease.
Management of IBS is multifaceted and tailored to symptom subtype and severity.
Dietary modification is often first-line, with the low FODMAP diet demonstrating efficacy in reducing symptoms. Fiber supplementation, particularly soluble fiber, may benefit patients with IBS-C, while poorly tolerated fibers should be avoided.
For patients with constipation-predominant IBS (IBS-C), pharmacologic therapy often progresses in a stepwise fashion, beginning with over-the-counter (OTC) options and advancing to prescription therapies when symptom control remains inadequate. This escalation is common—many IBS-C patients report only partial or inconsistent relief with OTC interventions, particularly when abdominal pain and bloating are prominent alongside constipation.
Initial pharmacologic therapy typically includes osmotic and bulk-forming agents, which are widely accessible and generally well tolerated.
Polyethylene glycol (PEG) is one of the most commonly used
osmotic laxatives and works by retaining water in the stool to increase stool frequency. While PEG is effective for improving bowel movement frequency, it has limited impact on global IBS symptoms such as abdominal pain and bloating, which are key components of IBS-C. As a result, patients may experience improved stooling but persistent discomfort.
Magnesium-based products, such as magnesium hydroxide or citrate, also act as osmotic agents. These can be effective in the short term but may be limited by tolerability, particularly diarrhea or electrolyte disturbances with chronic use.
Bulk-forming agents such as psyllium are often recommended early in treatment. Soluble fiber can improve stool consistency and frequency, and some patients report modest improvement in overall symptoms. However, insoluble fiber (e.g., bran) may exacerbate bloating and abdominal discomfort and is generally less well tolerated in IBS-C populations.
Stimulant laxatives, including senna and bisacodyl, are sometimes used intermittently for rescue therapy. While effective at inducing bowel movements, they are not ideal for chronic management due to the potential for cramping and the lack of effect on underlying IBS pathophysiology.
Despite these options, a substantial proportion of IBS-C patients continue to experience symptoms—particularly abdominal pain, bloating, and incomplete evacuation—prompting consideration of prescription therapies.
Prescription Therapies: Targeted Mechanisms for IBS-C
When OTC therapies fail to provide adequate relief, escalation to prescription medications is appropriate. Unlike traditional laxatives, these agents target specific mechanisms involved in IBS-C pathophysiology, including intestinal fluid secretion, motility, and visceral hypersensitivity.
Guanylate Cyclase-C (GC-C) Agonists
These medications activate guanylate cyclase-C receptors on the intestinal epithelium, increasing cyclic GMP levels. This results in enhanced chloride and bicarbonate secretion into the intestinal lumen, leading to increased fluid secretion and accelerated transit.
Importantly, GC-C agonists also appear to reduce visceral pain signaling, making them particularly effective for patients with prominent abdominal pain. Clinical trials have demonstrated improvements in both bowel movement frequency and global IBS symptoms.
Diarrhea is the most common adverse effect and may lead to discontinuation in some patients, but overall tolerability is favorable.
Chloride Channel Activators
These types of therapies activate type-2 chloride channels (ClC-2) on intestinal epithelial cells, promoting fluid secretion and facilitating stool passage.
Chloride channel activators have demonstrated efficacy in improving spontaneous bowel movements and some global symptoms of IBS-C, although its impact on abdominal pain is generally less robust compared to GC-C agonists.
Common side effects include nausea, which can be mitigated by taking the medication with food.
Sodium/Hydrogen Exchanger 3 (NHE3) Inhibitors
Sodium/Hydrogen Exchanger 3 (NHE3) Inhibitors represents a newer class of therapy targeting sodium absorption in the small intestine. By inhibiting the NHE3 transporter, this therapy reduces sodium uptake, leading to increased water secretion into the intestinal lumen and softer stools.
In addition to improving bowel movement frequency, NHE3 inhibitors have demonstrated benefits in reducing abdominal pain and bloating, making it a valuable option for patients with more complex symptom profiles.
Diarrhea remains the most common adverse event, consistent with other secretory agents.
In addition to secretory agents, 5-HT4 receptor agonists provide a targeted approach to improving gastrointestinal motility.
These agents act on serotonin (5-HT4) receptors located on enteric neurons within the myenteric plexus. Activation of these receptors enhances the release of excitatory neurotransmitters such as acetylcholine, promoting coordinated peristalsis and accelerating colonic transit. This mechanism directly addresses one of the core physiologic abnormalities in IBS-C—delayed intestinal transit.
Clinically, 5-HT4 receptor agonists increase spontaneous bowel movements, improve stool consistency, and reduce straining and the sensation of incomplete evacuation. Their impact on abdominal pain is generally more modest compared to GC-C agonists, but they are particularly effective in patients with motility-predominant symptoms.
In practice, the transition from OTC to prescription therapy is often driven by persistent symptoms despite adequate trials of fiber and osmotic agents. Importantly, IBS-C management should not focus solely on stool frequency; addressing abdominal pain and bloating is equally critical for improving patient quality of life.
Many patients require a combination approach, integrating dietary modification (such as low FODMAP), pharmacologic therapy, and behavioral interventions. Shared decision-making is essential, as treatment response can vary significantly between individuals.
Given the chronic nature of IBS-C, clinicians should set realistic expectations with patients—emphasizing symptom control
rather than cure—and be prepared to adjust therapy over time.
Pathophysiology and Overview
IBD is a chronic inflammatory condition arising from an inappropriate immune response to intestinal microbiota in genetically predisposed individuals. Environmental factors such as smoking, diet, and antibiotic exposure also play a role.
The two primary forms of IBD—Crohn’s disease and ulcerative colitis—are distinguished by their distribution and depth of inflammation.
Crohn’s Disease
Crohn’s disease can affect any part of the gastrointestinal tract from mouth to anus and is characterized by transmural inflammation. It often presents with “skip lesions,” meaning discontinuous areas of disease.
Subtypes are often categorized based on location and behavior:
• Ileal
• Colonic
• Ileocolonic
• Upper GI involvement
Behavioral classifications include inflammatory, stricturing, and penetrating disease.
Ulcerative colitis is limited to the colon and rectum, with continuous inflammation beginning in the rectum and extending proximally.
Subtypes are based on disease extent:
• Ulcerative proctitis
• Left-sided colitis
• Extensive colitis (pancolitis)
Inflammation in ulcerative colitis is typically confined to the mucosal layer.
Clinical Presentation
IBD often presents with chronic diarrhea, which may be bloody in ulcerative colitis. Abdominal pain, urgency, and tenesmus are common. Systemic symptoms such as fatigue, weight loss, and fever may also occur.
Extraintestinal manifestations are a key distinguishing feature and may involve the skin (erythema nodosum), joints (peripheral arthritis), eyes (uveitis), and hepatobiliary system (primary sclerosing cholangitis).
Unlike IBS, IBD symptoms may occur at night and are frequently associated with laboratory abnormalities such as anemia, elevated C-reactive protein (CRP), and hypoalbuminemia.
The diagnosis of IBD requires a combination of clinical, laboratory, endoscopic, and histologic findings.
Initial evaluation typically includes blood tests (CBC, CRP, ESR), stool studies to exclude infection, and fecal calprotectin to assess intestinal inflammation. Elevated fecal calprotectin is particularly useful in distinguishing IBD from IBS.
Colonoscopy with biopsy remains the gold standard for diagnosis, allowing direct visualization of mucosal inflammation and histologic confirmation. Imaging studies such as CT or MR enterography are often used in Crohn’s disease to assess small bowel involvement and complications.
The management of IBD has evolved significantly, with a focus on achieving and maintaining remission while preventing complications.
Treatment is tailored to disease severity, location, and patient-specific factors.
Aminosalicylates (5-ASA) are commonly used in mild to moderate ulcerative colitis but have limited efficacy in Crohn’s disease. Corticosteroids are effective for inducing remission but are not suitable for long-term use due to side effects. Immunomodulators are used for maintenance therapy in selected patients.
Biologic therapies have transformed IBD management, targeting specific inflammatory pathways. These include anti-TNF agents, anti-integrin therapies, and interleukin inhibitors. More recently, small-molecule agents such as Janus kinase (JAK) inhibitors have expanded treatment options.
Surgical intervention may be required in cases of refractory disease or complications such as strictures, fistulas, or dysplasia. Unlike Crohn’s disease, ulcerative colitis can be cured with total colectomy, although this carries significant implications for quality of life.
For primary care physicians, differentiating IBS from IBD often hinges on recognizing patterns in presentation and identifying red flags.
IBS is characterized by chronic, fluctuating symptoms without objective evidence of inflammation. Patients typically appear well, and laboratory testing is normal. Symptoms are often triggered by stress or diet and improve with conservative management.
IBD, on the other hand, should be suspected in patients with persistent diarrhea, especially if bloody, accompanied by systemic symptoms or abnormal laboratory findings.
The presence of nocturnal symptoms, weight loss, anemia, or elevated inflammatory markers should prompt further evaluation and referral for endoscopy.
Fecal calprotectin has emerged as a valuable noninvasive tool in primary care, helping to distinguish inflammatory from functional bowel disorders and guide referral decisions.
Primary care physicians play a central role in both IBS and IBD management. In IBS, ongoing care focuses on symptom management, patient education, and reassurance. Establishing a strong therapeutic relationship is essential, as patients often benefit from continuity of care and validation of their symptoms.
In IBD, primary care physicians are key partners in monitoring disease activity, managing comorbidities, ensuring vaccination compliance, and addressing preventive care needs such as colorectal cancer screening. Coordination with gastroenterology is essential, particularly as treatment regimens become increasingly complex.
Advances in microbiome research, precision medicine, and targeted therapies continue to reshape the landscape of gastrointestinal disease.
In IBS, emerging therapies aimed at modulating the microbiome and gut-brain axis hold promise for more personalized treatment approaches.
In IBD, the expansion of biologic and small-molecule therapies is enabling more precise targeting of inflammatory pathways, with the goal of achieving deep remission and altering disease course.
For primary care physicians, staying informed about these developments is critical, as early recognition and appropriate management can significantly impact patient outcomes.
While IBS and IBD share overlapping gastrointestinal symptoms, they represent fundamentally different conditions requiring distinct diagnostic and therapeutic approaches. IBS is a functional disorder driven by gut-brain interactions, whereas IBD is a chronic inflammatory disease with potential for serious complications.
Accurate differentiation begins in primary care, where careful history-taking, recognition of alarm features, and judicious use of diagnostic tools can guide appropriate management and referral. By understanding the nuances of each condition, primary care physicians can improve diagnostic accuracy, optimize treatment, and ultimately enhance patient quality of life.

- Move from Waived to Non-Waived Testing with the help of experts
- Expand testing, don’t worry about all the work- policies, fillable forms, e-signatures, calendar reminders included
- Remote access – Lab Directors and Consultants manage compliance efficiently, save time, and travel expenses
call
or email us at
from Newman Medical ABI
Your Patients Trust YOU To Find Their Peripheral Artery Disease
• High-risk patients include those over 65, diabetics, and smokers.
• If left untreated, 25% of patients with PAD will experience a heart attack or stroke within 5 years.
• PAD symptoms are often mistaken for arthritis or old age.
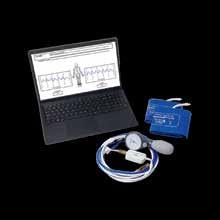
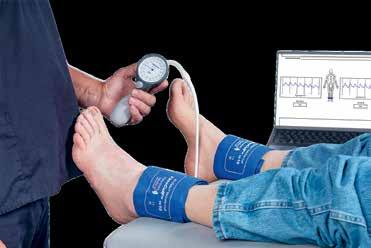
The simpleABI Cuff-Link System is Easy to Learn and Use.
• With a push-button remote, automatic calculations, and waveforms, it’s incredibly user-friendly.
• Reports are straightforward to save and share since the system is PC-based.
Outstanding Value and Reimbursements
• The system pays for itself in less than a year with just one test per week.
• Medicare reimbursements vary by exam and location, averaging from $91 to $174.
From Bindex Medical
Comparable to DXA
Extensive clinical research has proven Bindex to be 90% accurate in detecting osteoporosis. It can replace nearly 70% of DXA scans for patients with suspected osteoporosis.
Fast and effective
Using safe pulse-echo ultrasound to measure cortical bone thickness, Bindex analyzes bone density in just seconds.
Easy to use anywhere
Lightweight and pocket-sized, Bindex allows patients to receive on-the-spot bone density scans in doctors’ offices, hospitals and clinics and at home.
From Morningside Medical



Standard cognitive screening tools like MMSE/ MOCA are exactly that; screening tools. The technology is there to test the patients that fail these screening tools right in your office. Get clinically relevant information about your patients’ brain performance, while generating additional reimbursement for the practice, leading to earlier diagnosis and more accurate referrals.
Aids in clear diagnosis • Strong Reimbursement • Improves Patient Outcomes
• Easy for any staff to perform • Cognitive Testing / Mental Health • Sudomotor Function / Neuropathy • Vestibular Testing / Fall Prevention • Autonomic Function/ Cardiovascular Risk

DIAZYME DZ-LITE™ C270 BENCHTOP GENERAL/SPECIAL CHEMISTRIES + DRUG SCREENS
From Carolina Liquid Chemistries
A fully-automated, open system, benchtop clinical chemistry analyzer with throughput up to 270 tests/hour, 36 reagent positions, and 30 sample positions. It features a menu of over 60 CLIA moderate complexity assays, including cancer markers, cardiovascular markers, coagulation markers, diabetic markers, inflammatory markers, liver markers, renal/pancreatic markers, sepsis markers, vitamin markers, photometric electrolytes, and drugs of abuse. To learn more, visit https://www.carolinachemistries.com/products/dz-lite-c270-benchtop-chemistry-analyzer/.
From Carolina Liquid Chemistries
When starting a lab, look no further. With a CLIA moderately complex menu of 35 general chemistries and 14 urine drug screens, the EasyRA is well-suited for oncology, rheumatology, and multi-specialty practices needing a benchtop clinical chemistry analyzer. The EasyRA offers photometric throughput of 240+ tests/hr (up to 480 tests/hr with ISE) and STAT samples in under 8 minutes. This all-in-one system is easy to learn and easy to operate.




TOXICOLOGY SCREENING SIMPLIFIED ABBOTT’S IMMTOX 270 BENCHTOP ANALYZER NOW WITH 14 ASSAYS
CLIA CATEGORIZED AS MODERATE COMPLEXITY
From Abbott
The ImmTox270 benchtop analyzer offers comprehensive toxicology screening solutions for physician offices, treatment centers and independent laboratories.
Broad test menu with over 20 assays to choose from including 14 that are now available as moderately complex.
With complete laboratory solutions from consultation to licensure, and compliance the Abbott Clinical Laboratory Solutions team has you covered.


From Siemens Healthineers
CLINITEK Status ® Connect System simplifies wireless or wired connectivity and testing oversight in point-of-care urinalysis for improved risk management.
• Offers flexible connectivity solutions by integrating data directly to the LIS, EMR or via point-of-care data management software solutions
• Provides improved POC testing workflow efficiencies when interfaced to leading data management solutions
• Minimize transcription errors with the 2-D bar-code scanner
• Improves risk management through advanced operator control functions, prevents unauthorized use
• Drives compliance across testing sites with programmable QC protocols and QC lockout
• Auto-Checks* help to ensure the quality and accuracy of data while facilitating an enhanced interpretation of results.
*Only available when using Siemens test strips with IR or color bands
From Siemens Healthineers
The DCA Vantage® Analyzer is a multi-parameter, point-of-care analyzer for monitoring glycemic control in patients with diabetes and detecting early kidney disease.
Benefits of the DCA Vantage System:
• CLIA-waived HbA1c test that is IFCC and NGSP-certified
• 1 µl finger stick without fasting – HbA1c results in 6 minutes
• Random urine sample provides A:C ratio in 7 minutes*
• Requires no sample or reagent preparation prior to testing
• Sample integrity safeguards
*CLIA moderately complex.
From Semler Scientific
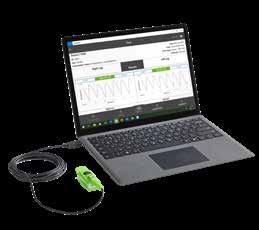
QuantaFlo® PAD is an easy to use, accurate, point of care, non-invasive solution that aids in the early detection of peripheral arterial disease (PAD). This FDA cleared device can be administered by a medical aide in less than 5 minutes. As published in the Journal of Vascular Surgery and the American Journal of Preventive Medicine, QuantaFlo detected undiagnosed PAD in 31.6% of patients +65.1 QuantaFlo is portable and integrates with other technologies and platforms. It is ideal for both home and clinic environments.
1. Smolderen KG, Ameli O, Chaisson CE, Heath K, Mena-Hurtado C. Peripheral Artery Disease Screening in the Community and 1-Year Mortality, Cardiovascular Events, and Adverse Limb Events, AJPM Focus (2022), https://doi.org/10.1016/j.focus.2022.100016





From Nova Biomedical
The U.S. FDA has cleared Nova Primary as a blood glucose reference analyzer that fills the need for a new reference analyzer to replace the YSI STAT PLUS 2300 (YSI, Inc., Yellow Springs, OH). Manufacturers of blood glucose measuring devices and clinical diabetes researchers have relied on the YSI 2300 as a reference and correlation analyzer. However, YSI, Inc. no longer supports the analyzer, and its discontinuation has left a critical industry void. With today’s FDA clearance, Nova Primary from Nova Biomedical is now available in the U.S. and worldwide.
From Meridian Bioscience
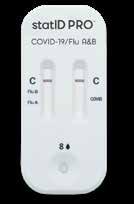
StatID PRO™ COVID-19/Flu A&B is an FDA-cleared, CLIA-waived rapid antigen test that detects and differentiates SARS-CoV-2, Influenza A, and Influenza B from a single anterior nasal swab. Delivering results in 15 minutes, it supports efficient, on-site respiratory testing in physician offices, urgent care, and point-of-care settings enabling timely clinical decisions and streamlined patient management.


BD VERITOR™ SYSTEM FOR RAPID DETECTION OF SARS-COV-2 & FLU A+B* (EUA) TEST
From BD Veritor™ Plus System
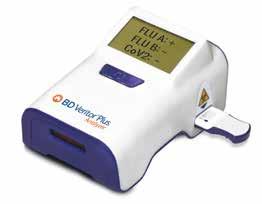
A 3-in-1 antigen assay for COVID-19, Flu A and Flu B with test results in 15 minutes.1
The BD Veritor™ Plus System streamlines clinical and patient workflows by detecting three key respiratory viruses in one test, reducing the need for multiple sample collections. With multiple testing modes and workflow efficiencies, the analyzer empowers convenience and efficiency (1 kit = 30 tests).
*In the USA, the BD Veritor™ System for Rapid Detection of SARS-CoV-2 & Flu A+B has not been FDA cleared or approved but has been authorized by the FDA under an Emergency Use Authorization for use by authorized laboratories; use by laboratories certified under the CLIA, 42 U.S.C. §263a, that meet requirements to perform moderate, high, or waived complexity tests. The product is authorized for use at the Point of Care (POC), i.e., in patient care settings operating under a CLIA Certificate of Waiver, Certificate of Compliance, or Certificate of Accreditation.
This product has been authorized only for the detection of proteins from SARS-CoV-2, influenza A and influenza B, not for any other viruses or pathogens; and, in the USA, the emergency use of this product is only authorized for the duration of the declaration that circumstances exist justifying the authorization of emergency use of in vitro diagnostics for detection and/or diagnosis of COVID 19 under Section 564(b)(1) of the Federal Food, Drug and Cosmetic Act, 21 U.S.C. §360bbb-3(b)(1), unless the declaration is terminated or authorization is revoked sooner.
1. BD Veritor™ Plus System for Rapid Detection of SARS-CoV-2 and Flu A+B. Package insert. 500051910 Becton, Dickinson and Company.




From LifeSign
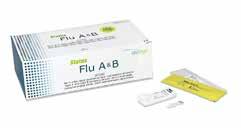
Status Flu A & B is an in vitro rapid qualitative test that detects influenza type A and type B directly from nasal swab, nasopharyngeal swab, and nasopharyngeal aspirate/wash specimens obtained from patients with signs and symptoms of respiratory infection. It is intended to aid in the rapid differential diagnosis of Influenza A and B viral infections.
• CLIA waived *Innovative flip design with onboard sample extraction
• Premeasured developer solution capsule for increased accuracy and ease of use
• Flocked nasal swabs for improved patient comfort and superior specimen collection
From LifeSign



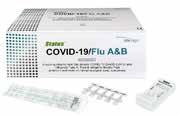
A Rapid Immunoassay for the Simultaneous Direct Detection and Differential Diagnosis of SARS-CoV-2, Influenza Type A and Type B Antigen from Anterior Nasal and Nasopharyngeal swab specimens. Infections with these viruses may present similar symptoms. Can you tell them apart? WE CAN!

OSOM® COVID-19 ANTIGEN
From Sekisui Diagnostics 6226
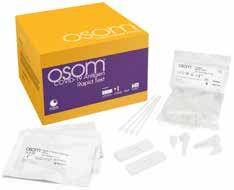
The OSOM® COVID-19 Antigen Rapid Test is a lateral flow immunoassay that detects the SARS-CoV-2 nucleocapsid protein with a nasal swab in only 15 minutes at the point-of-care. The test is intended to be used by healthcare professionals or operators on patients suspected of COVID-19 within the first 7 days of symptom onset. The clinical performance compares favorably against polymerase chain reaction methodology, with a positive percent agreement of 95.1% and a negative percent agreement of 97%.
OSOM® COVID-19 Antigen Rapid Test has not been FDA cleared or approved. It is authorized by FDA under an EUA for prescription use only. It has been authorized only for the detection of SARS-CoV-2 antigen, not for any other viruses or pathogens and is only authorized for the duration of the declaration that circumstances exist justifying the authorization of emergency use of in vitro diagnostics for detection and/or diagnosis of COVID-19 under Section 564(b)(1) of the Federal Food, Drug, and Cosmetic Act, 21 U.S.C S360bbb-3(b)(1), unless the authorization is terminated or revoked sooner.

Comprehensive toxicology menu now with 14 CLIA 1 categorized moderate complexity assays.


Toxicology screening solutions for physician offices, pain management, treatment centers and laboratories testing 200+ patient samples/mo.
MODERATE COMPLEXITY ASSAYS – FDA 510(K) CLEARED
6-acetylmorphine (6-AM Heroin metabolite)
Amphetamine
Barbiturates
Benzodiazepines
Benzoylecgonine (Cocaine metabolite)
Buprenorphine
Cannabinoids (THC)

EDDP (Methadone metabolite)
Fentanyl*
Methamphetamine
Opiates
Oxycodone
Phencyclidine (PCP)
Tramadol
Scan this QR code to view the ImmTox™ 270 product video
BY MATT BAKER, PHYSICIANS OFFICE RESOURCE
Primary care physicians today operate at the intersection of clinical complexity, patient expectations, and increasing pressure to deliver efficient, evidence-based care. Across family medicine, internal medicine, pediatrics, OB/GYN, and geriatric medicine, clinicians are tasked with making rapid decisions that directly influence outcomes, resource utilization, and patient satisfaction.
At the center of these decisions lies diagnostic testing.
Historically, primary care has relied on a combination of clinical judgment, laboratory send-out testing, and rapid in-office assays. However, delays in results, diagnostic uncertainty, and workflow inefficiencies have often complicated care delivery. The evolution of CLIA-waived diagnostics—encompassing both antigen-based and molecular testing—has begun to fundamentally change this dynamic.
Today, clinicians can access high-quality diagnostic results within minutes, enabling real-time, evidence-based decision-making. The implications are profound: faster answers, more accurate diagnoses, improved antimicrobial stewardship, and enhanced patient experiences.
CLIA-waived tests are designed to be simple, safe, and reliable, allowing them to be performed in point-of-care settings without the need for complex laboratory infrastructure. These tests meet criteria established under the Clinical Laboratory Improvement Amendments (CLIA), making them widely accessible across physician offices, urgent care centers, and outpatient clinics.
Two primary categories dominate the CLIA-waived diagnostic landscape:
• Antigen-based tests, which detect specific proteins from pathogens
• Molecular tests, which detect genetic material (DNA or RNA) using amplification technologies
Each modality offers distinct advantages, and together they provide a complementary toolkit that supports a wide range of clinical scenarios.
Perhaps the most transformative aspect of CLIA-waived diagnostics is speed. Many tests—both antigen and molecular—deliver results in as little as a few minutes to under half an hour. This rapid turnaround reshapes the clinical encounter.
In traditional workflows, physicians often rely on empiric treatment while awaiting laboratory confirmation. This can lead to overtreatment, delayed therapy, or the need for follow-up communication once results become available. With CLIA-waived testing, clinicians can instead make immediate, data-driven decisions during the patient visit.
For example, a patient presenting with fever, cough, and malaise during respiratory virus season can be tested and diagnosed before leaving the exam room. Whether the result indicates influenza, COVID-19, RSV, or no viral infection at all, the physician can tailor treatment, counseling, and follow-up accordingly—on the spot.
This shift from delayed to real-time diagnostics improves clinical efficiency, reduces uncertainty, and enhances patient trust.
Antigen-based CLIA-waived tests have long been a cornerstone of point-of-care diagnostics in primary care. Their rapid turnaround time—often within minutes—combined with ease of use and lower cost makes them highly valuable in high-volume clinical settings.
These tests are particularly effective when pathogen burden is high, such as during the early symptomatic phase of infections like influenza or COVID-19. In such scenarios, antigen testing can provide quick answers that enable immediate clinical action.
In practice, antigen tests are often used for:
• Rapid screening during peak respiratory seasons
• Triage decisions in busy clinics or urgent care settings
• Situations where immediate isolation or cohorting decisions are needed
Their speed allows clinicians to quickly identify infectious patients, initiate appropriate precautions, and begin treatment when indicated.
However, antigen tests do have limitations. Their lower sensitivity compared to molecular assays means that false negatives can occur, particularly in cases with low viral load or early infection. As a result, negative antigen results in patients with high clinical suspicion may require confirmatory testing.
Despite these limitations, antigen testing remains an essential tool— particularly when speed, cost, and accessibility are prioritized.
CLIA-waived molecular diagnostics represent a significant advancement in point-of-care testing. By detecting pathogen-specific genetic material, these tests offer superior sensitivity and specificity, bringing laboratory-level accuracy directly into the physician office.
Modern molecular platforms have been engineered for simplicity, allowing them to meet CLIA waiver requirements while delivering results in approximately 10 to 30 minutes. This combination of speed and precision makes them particularly valuable in cases where diagnostic certainty is critical.
Molecular testing is especially impactful in:
• Differentiating between pathogens with overlapping symptoms
• Detecting infections in early or low viral load stages
• Confirming negative antigen results when clinical suspicion remains high
For instance, respiratory infections caused by influenza, RSV, and SARS-CoV-2 often present similarly. Molecular assays can accurately distinguish between these pathogens, enabling targeted treatment decisions and more precise patient counseling.
By reducing false negatives and diagnostic ambiguity, molecular diagnostics allow clinicians to practice with greater confidence and precision.
Rather than viewing antigen and molecular diagnostics as competing technologies, many primary care practices are adopting a complementary, tiered approach.
In this model, antigen testing serves as a rapid, cost-effective first-line tool for screening and immediate decision-making. Molecular testing is then used in situations where:
• Clinical suspicion remains high despite a negative antigen result
• Diagnostic confirmation is necessary before initiating treatment
• Patient risk factors warrant the highest level of diagnostic accuracy
This layered strategy allows clinicians to balance speed, cost, and accuracy, tailoring their approach to each patient’s clinical presentation and risk profile.
One of the most important implications of improved point-of-care diagnostics is their role in antimicrobial stewardship.
Diagnostic uncertainty has historically driven the overuse of antibiotics, particularly in cases of respiratory illness where viral and bacterial infections can present similarly. CLIA-waived diagnostics—both antigen and molecular— help address this challenge by providing rapid, actionable insights.
When a viral pathogen is identified, clinicians can confidently avoid prescribing antibiotics, reducing unnecessary exposure and helping combat antimicrobial resistance. Conversely, accurate identification of bacterial infections ensures that antibiotics are used appropriately and effectively.
This precision in prescribing not only benefits individual patients but also supports broader public health efforts.
The integration of CLIA-waived diagnostics into primary care workflows offers significant operational benefits.
Rapid in-office testing reduces the need for follow-up communication, minimizes delays in care, and decreases administrative burden associated with tracking laboratory results. Patients receive answers during their visit, improving satisfaction and adherence to treatment plans.
From a practice management perspective, these efficiencies can translate into improved throughput, optimized scheduling, and enhanced overall performance. As reimbursement models continue to evolve, point-of-care diagnostics are increasingly recognized as both a clinical and economic asset.
CLIA-waived diagnostics provide value across all primary care specialties.
In family and internal medicine, they support the management of common acute conditions such as respiratory infections and streptococcal pharyngitis, enabling timely and appropriate treatment.
In pediatrics, where rapid diagnosis is essential and symptom presentation can be nonspecific, these tests provide clarity that can prevent disease progression and unnecessary interventions.
In OB/GYN, point-of-care diagnostics facilitate timely identification of infections that may impact maternal and fetal health, allowing for prompt and targeted treatment.
In geriatric medicine, where patients often present with atypical symptoms and increased vulnerability, diagnostic accuracy is critical to avoid complications and optimize outcomes.
For patients, the benefits of CLIA-waived diagnostics are immediate and tangible.
Receiving a diagnosis during the same visit reduces anxiety, eliminates uncertainty, and allows for prompt initiation of treatment. Patients are more likely to trust and adhere to care plans when decisions are supported by clear diagnostic evidence.
In an era where convenience and transparency are increasingly valued, point-of-care diagnostics align closely with patient expectations for modern healthcare delivery.
The landscape of CLIA-waived diagnostics continues to evolve rapidly. Advances in technology are expanding the range of detectable pathogens, improving test performance, and further reducing turnaround times.
Multiplex testing capabilities are enabling clinicians to assess multiple pathogens simultaneously from a single sample, providing comprehensive diagnostic insights in real time. Integration with digital health platforms and electronic medical records is also enhancing data utilization and population health management.
As innovation continues, the role of CLIA-waived diagnostics in primary care will only expand, further solidifying their place as a cornerstone of modern clinical practice.
CLIA-waived diagnostics—spanning both antigen and molecular testing—are transforming how primary care physicians approach diagnosis and treatment.
By delivering rapid, reliable results at the point of care, these tools enable clinicians to move beyond uncertainty and make informed decisions in real time. Antigen testing provides speed and accessibility, while molecular diagnostics offer enhanced accuracy and diagnostic confidence.
Together, they form a powerful, complementary approach that supports better clinical outcomes, improved antimicrobial stewardship, and a more efficient healthcare system. In today’s fast-paced clinical environment, the ability to act quickly and accurately is no longer a luxury—it is a necessity. CLIA-waived diagnostics are helping primary care physicians meet that need, one patient at a time.
From Sekisui Diagnostics
• 3-in-1 Multiplex – Detects COVID-19, Flu A and Flu B from one swab, in one test
• Minimal Hands-On Time – Can be performed in a CLIA-waived setting in a few simple steps
• Convenient– No maintenance or calibration, ready for testing any time
• Accessible and Flexible – Suitable for any facility
• Exceptional Support – Experienced support teams and online training modules to help streamline your implementation
This product has not been FDA cleared or approved, but has been authorized for emergency use by FDA under an EUA; This product has been authorized only for the detection and differentiation of nucleic acid from SARS-CoV-2, Influenza A, and Influenza B, not for any other viruses or pathogens. The emergency use of this product is only authorized for the duration of the declaration that circumstances exist justifying the authorization of emergency use of in vitro diagnostics for detection and/or diagnosis of COVID-19, Flu A, and Flu B under Section 564(b) (1) of the Federal Food, Drug, and Cosmetic Act, 21 U.S.C. § 360bbb 3(b)(1), unless the declaration is terminated or authorization is revoked sooner.
From Sekisui Diagnostics
From only one sample, the OSOM® Flu SARS-CoV-2 Combo Test simultaneously detects and differentiates between COVID-19, Flu A, and Flu B in just 10 minutes, allowing healthcare providers to make more informed decisions when treating patients who are symptomatic with viral infections that have similar symptoms, but different treatment protocols. Designed for point-of-care testing, the OSOM® Flu SARS-CoV-2 Combo Test empowers healthcare providers with the confidence necessary to initiate immediate treatment and isolation protocols at the very first patient visit.
This test has not been FDA cleared or approved. It is authorized by FDA under an EUA for use by authorized laboratories. It has been authorized only for the detection of proteins from SARS-CoV-2, influenza A and influenza B, not for any other viruses or pathogens and is only authorized for the duration of the declaration that circumstances exist justifying the authorization of emergency use of in vitro diagnostics for detection and/or diagnosis of COVID-19 under Section 564(b)(1) of the Federal Food, Drug, and Cosmetic Act, 21 U.S.C S360bbb-3(b)(1), unless the authorization is terminated or revoked sooner.


from Sekisui Diagnostics
Test for both high-risk groups, younger children & elderly adults, for severe RSV infection using the OSOM® RSV Test. This test is a CLIAwaived, point-of-care test designed to detect Respiratory Syncytial Virus (RSV) using a painless anterior nasal swab in just 15 minutes. It is suitable for both children aged 6 months to 6 years and adults aged 60 and above, providing healthcare professionals with flexibility in diagnosing patients exhibiting symptoms of respiratory infections.


From Abbott
With reduced budgets, shrinking laboratory space and staffing challenges, many laboratories need a solution that lets them work smarter with less. The CELL-DYN Emerald 22 AL is a full performance, automated optical 5-part differential analyzer that delivers smarter results for small to midsize clinical laboratories.
• Compact Design
• Walkaway Functionality
• Ease Of Use
• Smart Safety Features


From Sysmex
With its simplified operation, the Sysmex XP-300™ is ideal for clinics and physician office labs. It provides a CBC with 17 different parameters, including a 3-part WBC Differential. The XP-300+M combines the accuracy and reliability of a Sysmex CBC with the agility of Medicus Middleware. Features include EMR connectivity, instrument interfaces and a QC module.


From CitoCBC
Cito means “quickly” in Latin, and CitoCBC® brings that efficiency to paitent care. FDA-cleared and CLIA-waived, it delivers lab-quality CBC results in minutes, reporting 16 parameters including a 5-part differential. Its cartridge-based design makes operation simple, while LIS connectivity and monthly QC ensure seamless workflow integration. For urgent care and primary care, CitoCBC is a true differentiator — enabling same-visit diagnostics that elevate patient care.


From Meridian Bioscience
LeadCare® II brings CLIA-waived blood lead testing directly to the pointof-care — so you can test, educate, and take action in a single visit. For pediatric practices, every well-child visit is an opportunity to protect a child’s development. With rapid, quantitative results in just three minutes from a simple fingerstick, you can counsel families and initiate next steps immediately — turning screening into meaningful action when it matters most.
From Semler Scientific
QuantaFlo® PAD is an easy to use, accurate, point of care, non-invasive solution that aids in the early detection of peripheral arterial disease (PAD). This FDA cleared device can be administered by a medical aide in less than 5 minutes. As published in the Journal of Vascular Surgery and the American Journal of Preventive Medicine, QuantaFlo detected undiagnosed PAD in 31.6% of patients +65.1 QuantaFlo is portable and integrates with other technologies and platforms. It is ideal for both home and clinic environments.
1. Smolderen KG, Ameli O, Chaisson CE, Heath K, Mena-Hurtado C. Peripheral Artery Disease Screening in the Community and 1-Year Mortality, Cardiovascular Events, and Adverse Limb Events, AJPM Focus (2022), https://doi.org/10.1016/j.focus.2022.100016



from Newman Medical
Your Patients Trust YOU To Find Their Peripheral Artery Disease
• High-risk patients include those over 65, diabetics, and smokers.
• If left untreated, 25% of patients with PAD will experience a heart attack or stroke within 5 years.
• PAD symptoms are often mistaken for arthritis or old age.
The simpleABI Cuff-Link System is Easy to Learn and Use.
• With a push-button remote, automatic calculations, and waveforms, it’s incredibly user-friendly.
• Reports are straightforward to save and share since the system is PC-based. Outstanding Value and Reimbursements
• The system pays for itself in less than a year with just one test per week.
• Medicare reimbursements vary by exam and location, averaging from $91 to $174.

From
A 3-in-1 antigen assay for COVID-19, Flu A and Flu B with test results in 15 minutes.1
The BD Veritor™ Plus System streamlines clinical and patient workflows by detecting three key respiratory viruses in one test, reducing the need for multiple sample collections. With multiple testing modes and workflow efficiencies, the analyzer empowers convenience and efficiency (1 kit = 30 tests).
*In the USA, the BD Veritor™ System for Rapid Detection of SARS-CoV-2 & Flu A+B has not been FDA cleared or approved but has been authorized by the FDA under an Emergency Use Authorization for use by authorized laboratories; use by laboratories certified under the CLIA, 42 U.S.C. §263a, that meet requirements to perform moderate, high, or waived complexity tests. The product is authorized for use at the Point of Care (POC), i.e., in patient care settings operating under a CLIA Certificate of Waiver, Certificate of Compliance, or Certificate of Accreditation.
This product has been authorized only for the detection of proteins from SARS-CoV-2, influenza A and influenza B, not for any other viruses or pathogens; and, in the USA, the emergency use of this product is only authorized for the duration of the declaration that circumstances exist justifying the authorization of emergency use of in vitro diagnostics for detection and/or diagnosis of COVID 19 under Section 564(b)(1) of the Federal Food, Drug and Cosmetic Act, 21 U.S.C. §360bbb-3(b)(1), unless the declaration is terminated or authorization is revoked sooner.
1. BD Veritor™ Plus System for Rapid Detection of SARS-CoV-2 and Flu A+B. Package insert. 500051910 Becton, Dickinson and Company.
OSOM® ULTRA STREP A TEST
From Sekisui Diagnostics

The OSOM® Ultra Strep A test is a color immunochromatographic assay intended for the qualitative detection of Group A Streptococcus antigen directly from throat swab specimens. Shown to be not statistically different than single swab culture. Sensitivity 95.7% and 100% Specificity. Includes two additional test sticks for External QC. CLIA Waived.
TOXICOLOGY SCREENING SIMPLIFIED ABBOTT’S IMMTOX 270 BENCHTOP ANALYZER NOW WITH 14 ASSAYS CLIA CATEGORIZED AS MODERATE COMPLEXITY
From Abbott
The ImmTox270 benchtop analyzer offers comprehensive toxicology screening solutions for physician offices, treatment centers and independent laboratories.
Broad test menu with over 20 assays to choose from including 14 that are now available as moderately complex.
With complete laboratory solutions from consultation to licensure, and compliance the Abbott Clinical Laboratory Solutions team has you covered.

I G H T N O W .
1 O U T O F 3 H A S P A D A N D T H E Y P R O B A B L Y D O N ’ T K N O W I T . A
Healthy Artery
P E R I P H E R A L
Patients with Peripheral Artery Disease (PAD) who may be facing a heart attack, stroke, amputation, or even death within the next 5 years I N T R O D U C I N G
Diabetics Smokers Over age 65
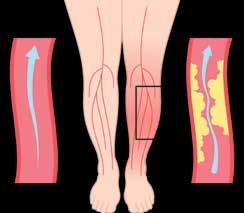
Diseased Artery
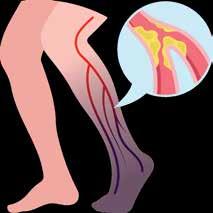
Atherosclerosis
(PAD) is an often silent condition where narrowed arteries reduce blood flow to the legs, causing symptoms like leg pain, numbness, and slow-healing wounds.
DON’T LET PAD SNEAK UP ON YOU OR THESE PATIENTS.
50% report no symptoms, while those that do attribute their pain to arthritis or “old age”.

N o n - i n v a s i v e , p a t i e n t - f r i e n d l y t e s t
A C C U R A T E
A c c u r a c y e q u a l o r b e t t e r t h a n D o p p l e r A B I .
U s e f u l f o r d i a b e t i c s w i t h c a l c i f i e d a r t e r i e s
R E I M B U R S A B L E
r .
G r e a t R O I : t h e t y p i c a l i n t e r n i s t h a s 8 0 0 M e d i c a r e p a t i e n t s , p e r A C P
T
l e s s t h a n t w o m o n t h s .
C P T 9 3 9 2 3 ( A B I w / e x e r

THESE PATIENTS TRUST YOU TO FIND THEIR PAD
before they have a heart attack, stroke, or even die PAD also leads to significant disability and reduced quality of life.

For over 45 years, Newman Medical has been a leader in vascular innovation The ABI-Q system continues that legacy with fast, accurate results you can trust
Scan for more info





Whether you're craving pristine beaches or vibrant cities, these nine must-visit destinations around the world promise stunning scenery, rich culture, and unforgettable adventures for every type of traveler.
md-escapes.com
Escape to an island oasis surrounded by crystal blue waters, white sand and lush tropical greenery. A breathtaking 30 acre, oceanfront luxury hotel in St. Thomas, VI, The Ritz-Carlton, St. Thomas is a Caribbean marvel styled after traditional island architecture, but richly updated with all of the contemporary comforts for which the resorts of The Ritz-Carlton are known.



In a city renowned for its beauty and culture, The Ritz-Carlton, Vienna distinguishes itself with a unique blend of modern luxuries, fine dining, and spa experiences, all housed within four 19th-century palaces. Situated in the heart of downtown Vienna, along the iconic Ringstrasse and adjacent to the Stadtpark, our luxury hotel offers 200 elegant guestrooms, including 43 exquisite suites, allowing you to indulge in tasteful living, distinctive designs, and breathtaking views.

SCAN TO LEARN MORE
Discover an elevated escape with the perfect balance of fun and relaxation at our AAA Five Diamond, luxury Orlando Resort. Splash around with the family at Explorer Island water park, or unwind beneath swaying palms at Oasis adult-only pool while we entertain your young ones at our complimentary kids camp. Treat yourself to a soothing, post-park massage at The Spa, then toast to the nightly Walt Disney World® fireworks views over dinner at our Michelin-starred rooftop steakhouse Capa. SCAN TO LEARN MORE



Spectacularly sited on a clifftop promontory where the rainforest meets the sea on Dominica, the “Nature Island” of the Caribbean, Secret Bay is among the leading boutique resorts in the world and an acclaimed Relais & Châteaux property. The secluded six-star, all-villa resort consists of elegantly appointed, residential-style villas, each with a private plunge pool and dedicated villa host, on-call concierge, chefs and guides, access to a secret beach and transformative experiences curated specifically for each guest.

SCAN TO LEARN MORE
All Inclusive Family Resort in Puerto Vallarta. Experience the best all-inclusive resort in Puerto Vallarta, where first-class amenities invite you to relax by infinity pools, indulge in gourmet dining, and rejuvenate at a world-class spa embraced by jungle and ocean views. Garza Blanca Puerto Vallarta combines breathtaking natural beauty, exceptional service, and upscale comfort for an unforgettable luxury family vacation.



Welcome to Five-Star Luxury in California Wine Country. In the food and wine capital of North America, Four Seasons welcomes you to a bespoke luxury resort in Napa Valley, the heart of California wine country. Our Forbes FiveStar Hotel in Calistoga is set within its own world-class vineyard. Discover innovative and seasonal cuisine at Michelin-starred Auro, holistic spa rituals at Spa Talisa and thoughtfully personalized Four Seasons service. Raise a glass to all the best in life as you soak in magnificent views of Napa Valley.

SCAN TO LEARN MORE
As one of the only non-gaming and non-smoking hotels on The Strip, Four Seasons Hotel Las Vegas is a unique oasis in the heart of the action-packed sports and entertainment capital of the world. Offering Five Diamond luxury accommodations, acclaimed dining and a Forbes Five-Star spa, Four Seasons offers the best of both worlds: a resort retreat amid the famous energy of Las Vegas.



Welcome to Four Seasons Hotel Nashville, a luxury hotel located in the heart of downtown’s vibrant SoBro neighborhood. This new social hub is just steps away from the city's iconic music, sports, and entertainment venues. Experience the rhythm of our lively restaurants and event spaces, the tranquility of our Spa, and the stunning views from our rooftop pool overlooking the Cumberland River and Riverfront Park. With the unmatched service of Four Seasons and warm Southern hospitality, we’ll inspire an authentic experience of Music City.

SCAN TO LEARN MORE

Located in the heart of Budapest, our luxury art nouveau palace Hotel – the only Forbes Five-Star hotel in Hungary – embodies the spirit of Budapest’s Golden Era glam. From the moment you enter the iconic wrought iron peacock gates, pass through the lobby adorned with more than two million mosaic tiles illuminated with its striking chandelier, and let inspiration wash over you. Outside, views of the Danube and the picturesque Buda skyline stand before you. Spend the day exploring the sights, recharge in our Spa that harnesses the city’s heritage in wellness, then enjoy an innovative cocktail at our lobby bar MÚZSA.

Better outcomes. Lower costs. Better patient experience. Better clinician experience.

Gain insights into your patient’s current status with real-time actionable results.
DCA Vantage® Analyzer
Rapid assessment of glycemic control and kidney health
HbA1c
• CLIA-waived
Albumin-to-creatinine ratio (ACR)
• CLIA Moderate Complexity
CLINITEK Status® Connect System
CLIA-waived analyzer for routine urinalysis, including kidney health
• CLINITEK® Microalbumin 2 Strip (ACR)

Customize your patient consultations to enhance physician-patient partnership toward improved outcomes.


Screening for iron deficiency, anemia, and lead exposure remains a foundational component of preventive care in primary care practice, particularly across pediatrics, women’s health, and vulnerable populations. However, recent evidence has begun to reshape how clinicians approach screening—shifting away from a model focused primarily on detecting overt disease toward one that emphasizes earlier identification, improved biomarkers, and more nuanced risk-based strategies.
Historically, screening efforts have centered on identifying anemia through hemoglobin testing and detecting lead exposure at higher thresholds. While these approaches remain important, they are increasingly recognized as insufficient for capturing early or subclinical disease. Iron deficiency without anemia, for example, can still significantly impact patient well-being, while even low levels of lead exposure have been shown to cause measurable neurodevelopmental harm. As a result, primary care physicians are being asked to rethink traditional screening paradigms and adopt a more proactive and comprehensive approach.
Iron deficiency is among the most prevalent nutritional deficiencies encountered in clinical practice, particularly affecting infants, children, and women of reproductive age. What has changed most significantly in recent years is the recognition that iron deficiency exists along a spectrum and that clinically meaningful symptoms can occur well before anemia develops.
Patients with iron deficiency may present with fatigue, decreased exercise tolerance, cognitive impairment, and reduced productivity even when hemoglobin levels remain within normal limits. This has led to growing awareness that relying exclusively on hemoglobin as a screening tool may delay diagnosis and treatment.
One of the most important updates in this area involves the use of ferritin as a primary screening biomarker. Ferritin reflects iron stores and allows for earlier detection of deficiency. In addition, updated guidance suggests that traditional ferritin thresholds were too conservative. Whereas a ferritin level below 15 ng/mL was historically used to define iron deficiency, more recent recommendations support higher thresholds— often below 30 ng/mL or even 45 ng/mL in the presence of anemia—to improve diagnostic sensitivity.
This shift is particularly relevant in patients with chronic inflammatory conditions, where ferritin may be falsely elevated. In such cases, combining ferritin with transferrin saturation (TSAT) improves diagnostic accuracy and helps distinguish between true iron deficiency and anemia of chronic disease.
Screening recommendations are also evolving. While universal screening in asymptomatic adults is not yet widely endorsed, there is increasing momentum toward more proactive screening in high-risk populations. These include infants, who are typically screened for anemia around 12 months of age, as well as pregnant individuals, who undergo routine hematologic evaluation during prenatal care. Increasingly, clinicians are also
considering ferritin testing early in pregnancy to detect iron deficiency before anemia develops.
Adolescent females and women of reproductive age represent another key group in whom expanded screening is gaining traction. Menstrual blood loss places these patients at higher risk, and earlier detection of iron deficiency may improve both clinical outcomes and quality of life. In adults more broadly, targeted screening is often appropriate in patients presenting with fatigue, chronic disease, or other nonspecific symptoms.
Although anemia screening continues to rely on hemoglobin and hematocrit measurements, the approach to evaluation has become more sophisticated. Rather than treating anemia empirically, current best practices emphasize identifying the underlying cause.
Iron deficiency remains the most common etiology, but clinicians must also consider other contributors such as chronic inflammation, vitamin B12 or folate deficiency, renal disease, and occult blood loss. In particular, iron deficiency anemia in adult men and postmenopausal women warrants careful investigation, as it may be the first sign of gastrointestinal pathology, including malignancy.
Recent guidance supports a more structured diagnostic approach in these patients, including evaluation for gastrointestinal sources of bleeding, screening for celiac disease, and testing for Helicobacter pylori infection when appropriate. This reflects a growing recognition that anemia is often a symptom of an underlying condition rather than a diagnosis in itself.
In pediatric populations, anemia screening continues to play a critical role in early development. Iron deficiency anemia in infancy and early childhood has been associated with long-term cognitive and behavioral consequences. As a result, routine screening during the first year of life remains a key preventive measure, with additional risk-based screening throughout childhood.
A notable trend in both adult and pediatric care is the increasing recognition of non-anemic iron deficiency as a clinically significant condition. This has implications for both screening and management, as earlier intervention may prevent progression to anemia and mitigate associated symptoms.
Perhaps the most significant shift in screening practices relates to lead exposure. Over the past decade, accumulating evidence has reinforced the concept that there is no safe level of lead exposure, particularly in children. Even low blood lead levels have been associated with adverse neurodevelopmental outcomes, including reduced IQ, attention deficits, and behavioral challenges.
In response to this evidence, public health authorities have lowered the blood lead reference value to 3.5 µg/dL. This
change reflects a move toward identifying and addressing exposure at earlier stages, rather than waiting for higher, more overtly toxic levels.
Screening recommendations vary based on population and geographic risk, but several key principles apply. Children enrolled in Medicaid are required to undergo lead screening at 12 and 24 months of age, while many states recommend universal screening for all children at similar intervals, particularly in high-risk areas. For children who have not been previously screened, catch-up testing is recommended.
Testing typically begins with a capillary blood sample, which offers convenience and accessibility in pediatric and primary care settings. If the capillary blood sample returns elevated results, the patient should have additional testing via a venous sample to confirm toxicity levels.
Management of elevated lead levels has also evolved. At lower levels, intervention focuses on education, environmental assessment, and nutritional optimization. As levels increase, more intensive monitoring and intervention are required, with chelation therapy reserved for significantly elevated cases.
An important and often underrecognized connection exists between lead exposure and iron deficiency. Iron-deficient individuals absorb lead more readily, which can exacerbate toxicity. As a result, screening for iron deficiency is recommended in patients with elevated lead levels, and addressing nutritional deficiencies is an essential component of management.
For primary care physicians, one of the key challenges is integrating these evolving screening recommendations into already busy clinical workflows. Fortunately, many opportunities exist to align screening with routine preventive care visits.
In pediatric practice, well-child visits provide a natural framework for screening. At approximately 12 months of age, children are typically screened for anemia and undergo initial lead testing. Repeat lead screening is often performed at 24 months, with additional risk-based screening as needed throughout early childhood.
In adolescent care, particularly for female patients, clinicians may consider incorporating ferritin testing into routine evaluations, especially in those with symptoms suggestive of iron deficiency or with known risk factors such as heavy menstrual bleeding.
In adult primary care, screening is often more individualized. Patients presenting with fatigue, chronic illness, or risk factors for nutritional deficiency may benefit from evaluation that includes a complete blood count and iron studies. Rather than ordering isolated tests, clinicians are increasingly adopting a more comprehensive approach that combines multiple relevant biomarkers to improve diagnostic yield and reduce the need for repeat testing.
Across all three domains—iron deficiency, anemia, and lead exposure—a common theme is emerging: the importance of earlier detection and intervention. Advances in our understanding of disease progression and risk have highlighted the limitations of traditional screening thresholds and approaches.
In iron deficiency, this has led to a greater emphasis on ferritin testing and the recognition of non-anemic deficiency as clinically meaningful. In anemia, it has prompted more thorough evaluation to identify underlying causes rather than relying on empiric treatment. In lead screening, it has resulted in lower thresholds for concern and a broader focus on environmental and social determinants of health.
These changes are not merely academic. They have direct implications for patient outcomes, particularly in vulnerable populations such as young children, pregnant individuals, and patients with limited access to care. By identifying disease earlier and addressing contributing factors more comprehensively, primary care physicians have the opportunity to improve both short- and long-term health outcomes.
Looking ahead, several trends are likely to further shape screening practices. Advances in point-of-care testing may soon allow for rapid, in-office assessment of ferritin and other biomarkers, reducing barriers to early detection. At the same time, increasing integration of electronic health record tools may enable more precise risk stratification, helping clinicians identify patients who would benefit most from screening.
There is also growing interest in developing formal guidelines for the diagnosis and management of iron deficiency without anemia, which could further expand screening recommendations. In the realm of lead exposure, continued collaboration between healthcare providers and public health agencies will be essential for identifying and mitigating environmental risks.
Screening for iron deficiency, anemia, and lead exposure is undergoing a meaningful transformation. The traditional focus on detecting overt disease is being replaced by a more proactive, prevention-oriented approach that emphasizes early identification, improved diagnostic tools, and individualized risk assessment.
For primary care physicians, this evolution underscores the importance of thinking beyond hemoglobin alone, incorporating updated ferritin thresholds, and recognizing the clinical significance of low-level lead exposure. By integrating these insights into routine practice, clinicians can enhance their ability to detect and address these common but often underrecognized conditions.
Ultimately, these changes represent an opportunity to deliver more effective, patient-centered care—improving outcomes through earlier intervention and a deeper understanding of the factors that contribute to disease.
From Abbott
Prescription drug misuse and illicit drug abuse is a growing public health challenge in this country. Building a test profile that covers highly misused drugs has never been so vital. With over 20 relevant assays to choose from Abbott’s suite of Immunalysis reagents allows you to easily screen for relevant substances. Our complete line of assays, calibrators, and controls enables you to implement an efficient drug screening program in office.


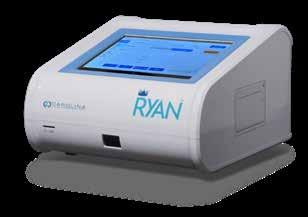
From Carolina Liquid Chemistries
Carolina Liquid Chemistries Corp. introduces the Fentanyl Urine Detection Test on CLC’s next-generation RYAN™ immunofluorescent analyzer. This FDA cleared and CLIA categorized, moderately complex, compact, point-of-care system detects fentanyl qualitatively in human urine at a cutoff concentration of 1.0 ng/mL. The test can be run in < 6 minutes, produces a chartable result, and is interfaceable. For detailed information, visit carolinachemistries.com/products/fentanyl-urinedetect-on-clc-ryan-analyzer/.
From CS Medical
The Ethos Automated Ultrasound Probe Cleaner Disinfector is the first FDA-cleared device to provide both cleaning and high-level disinfection of ultrasound probes in one system. It’s fast and easy to use—simply place a soiled transvaginal, transrectal, or surface probe into the device, follow the prompts on the display, and a reprocessing report is printed at the end of the cycle. Ethos removes the unknowns of manual cleaning, giving healthcare professionals confidence and consistency with every cycle.



From Sekisui Diagnostics
The OSOM® BVBLUE® detects elevated vaginal fluid sialidase activity, an enzyme produced by bacterial pathogens associated with bacterial vaginosis including Gardnerella, Bacteroides, Prevotella and Mobiluncus. OSOM® BVBLUE® is more sensitive than Amsel criteria providing physicians with a more accurate diagnosis to treat and minimize serious health consequences such as early spontaneous preterm births and miscarriage.


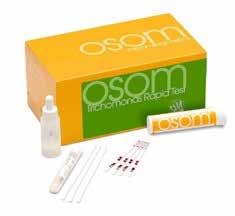
From Sekisui Diagnostics
The OSOM® Trichomonas Rapid Test is intended for the qualitative detection of Trichomonas vaginalis antigens from vaginal swabs or from the saline solution. The OSOM® Trichomonas Rapid Test is a CLIA-waived rapid test available today. OSOM® Trichomonas is more sensitive than wet mount due to the assay being able to detect viable and non-viable organisms which offers significant benefits to the patient and clinician alike.
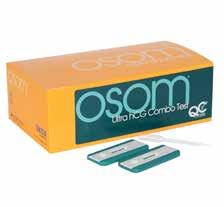
From Sekisui Diagnostics
The OSOM® Ultra hCG Combo test is a simple immunoassay for the qualitative detection of human chorionic gonadotropin (hCG) in serum or urine for the early confirmation of pregnancy. Internal studies have confirmed that the OSOM® Ultra hCG Combo test does not have a false negative result from hCG variants providing physicians with a higher level of confidence.








• Unambiguous positive/negative display which may help to reduce result interpretation errors and streamline diagnosis.
• No monthly calibration required, operated with single-button functionality.
• No service contracts, maintenance or calibration needed for device lifetime.
• Delivers digitally read results in 15 minutes or less,** supporting timely clinical decisions.
• Walk Away mode: Built in timer allows you to perform other tasks throughout test development.
• Analyze Now mode: Enables immediate processing to support batch testing.†
• Compact, lightweight and portable— able to function without cords.
*In the USA, the BD Veritor™ System for Rapid Detection of SARS-CoV-2 & Flu A+B has not been FDA cleared or approved but has been authorized by the FDA under an Emergency Use Authorization for use by authorized laboratories; use by laboratories certified under the CLIA, 42 U.S.C. §263a, that meet requirements to perform moderate, high, or waived complexity tests. The product is authorized for use at the Point of Care (POC), i.e., in patient care settings operating under a CLIA Certificate of Waiver, Certificate of Compliance, or Certificate of Accreditation. This product has been authorized only for the detection of proteins from SARS-CoV-2, influenza A and influenza B, not for any other viruses or pathogens; and, in the USA, the emergency use of this product is only authorized for the duration of the declaration that circumstances exist justifying the authorization of emergency use of in vitro diagnostics for detection and/or diagnosis of COVID 19 under Section 564(b)(1) of the Federal Food, Drug and Cosmetic Act, 21 U.S.C. §360bbb-3(b)(1), unless the declaration is terminated or authorization is revoked sooner.
**Result processing times for each BD Veritor™ assay are 15 minutes for the SARS-CoV-2 and SARS-CoV-2 & Flu A+B assays, 10 minutes for Flu A+B and RSV assays, and 5 minutes for the Group A Strep assay.
†Any batch testing performed should be conducted at the discretion of the user, in accordance with local policies and clinical judgment.

Your patients depend on you to provide the best care possible and find solutions for the most uncomfortable situations.
Our high-quality, women’s health rapid antigen tests are made in the U.S.A. and designed to be accurate and easy to use so you can get results fast. We help you deliver answers and treatment plans getting your patients on the road to recovery fast.
We make diagnostics that matter because we believe each test represents the health and well-being of a real person.


