TheUniversityofMelbourne acknowledgestheTraditionalOwnersof theuncededlandonwhichwework, learnandlive:theWurundjeriWoiwurrungandBunurongpeoples(Burnley, FishermansBend,Parkville,Southbank andWerribeecampuses),theYortaYorta Nation(DookieandShepparton campuses),andtheDjaDjaWurrung people(Creswickcampus).
Part1-BalancingAct
1.Marketfailure
2.Regulation
3.Competition(Marco)
Whypatientscan'tactlikeordinaryconsumers
Asymmetry
Patientsoften knowlessthan providers.
Consumerprotection
Demandisoften unpredictable. Costscanbe catastrophic.
Insuranceisneeded
CompetitionandRegulationintheHealthcareSector|SusanJ.Méndez
Supplier-Induced Demand
Doctorsboth recommendand delivercare.
Cream-skimming
Marketsexcludehighriskpopulations,lowincomecommunities, ruralareas.
Guidelinesandaudits
Insurancedesign
CompetitionandRegulationintheHealthcareSector|SusanJ.Méndez
Marketpower Entrybarriers increase concentration& reducescompetition levers. Competition policy
Part2–Australiancasestudies
1.Feetransparency
2.Telemedicine
3Background–Australianhealthcaresystem
Background:Tax-fundeduniversalhealthsystem.
-Publichospital(freebutwithwaitingtimes).
-Privatehospitals&outpatientservices(subsidisedfeefor-service).
-Unregulatedpricesout-of-pocketcosts
-Referral-basedmarket(GeneralPractitioneras gatekeeper).
AProblem:Patientsforgospecialistcarebecauseofcost. Publicfeedisclosureasasolution?
CompetitionandRegulationintheHealthcareSector|SusanJ.Méndez
Thelimitsofpatient-facingtransparency
Ifpricesarevisible,willdoctorscompete?
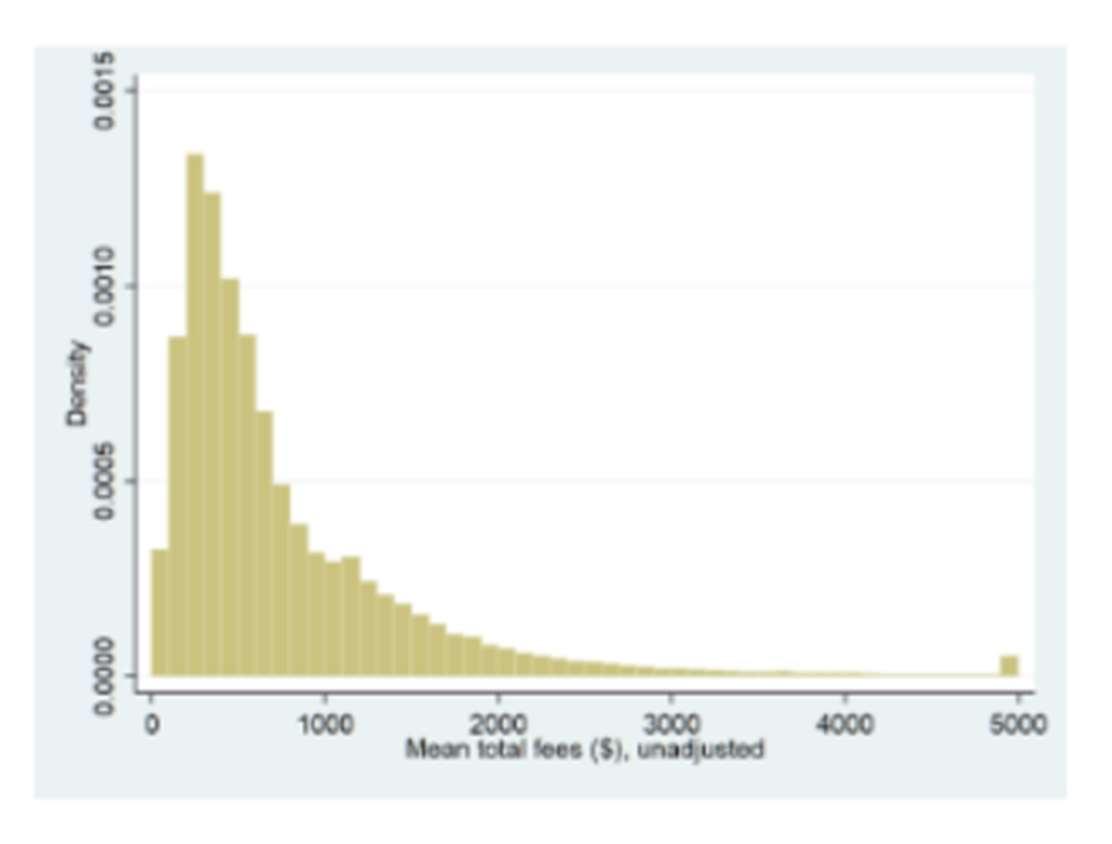
Non-GPspecialistmarketischaracterisedby
-Highpricedispersion(signalslow competition).
-Dispersionisnotdrivenbypatient complexity.
-Feebenchmarkingagainstpeernormsand anchors(recommendedfees). Rangeoffeesforcommonprocedures(in$)
Source:Yongetal.HP,2024
5Thelimitsofpatient-facingtransparency
Ifpricesarevisible,canpatientsshop?
-Searchingforinformationiscostly.
-Differencesinabilitytosearch,process,andinterpretinformation.
-Differencesinnegotiationskills.
Timeconstraints|Acutehealthneeds|Healthliteracy
-Referral-basedmarket(GPasgatekeeper)
CompetitionandRegulationintheHealthcareSector|SusanJ.Méndez
•TargettransparencyatGPs,notpatients:embedrisk-adjustedcost&qualitydata intoreferralsystems.
•Provideepisode-basedexpectedcosts(notrawfeelists),includingallteam members(surgeon,anaesthetist).
•Complementwithqualityindicatorsandwaitingtimestoreshapeprofessional normsandreferralpatterns.
DigitalInnovation
CaseStudy2:Telemedicine inAustralia
Thebenefitsofdigitaltechnologyinhealthcare
Types
-Electronic healthrecords (EHR) -Telemedicine -Remotecare -AI
Benefits -Efficiency -Reduceuse -Quality -Convenience
Telehealthalonesaves theconsumeraround $480million intraveltimecosts
Source:ProductivityCommission2024,Leveraging digitaltechnologyinhealthcare.Australia.
Upto30%ofthe tasksundertakenby theworkforcecouldbe automatedusing digital technologyandAI
CompetitionandRegulationintheHealthcareSector|SusanJ.Méndez
ElectronicMedical Recordsystemscould reduceduplicationof services,saving around $355million
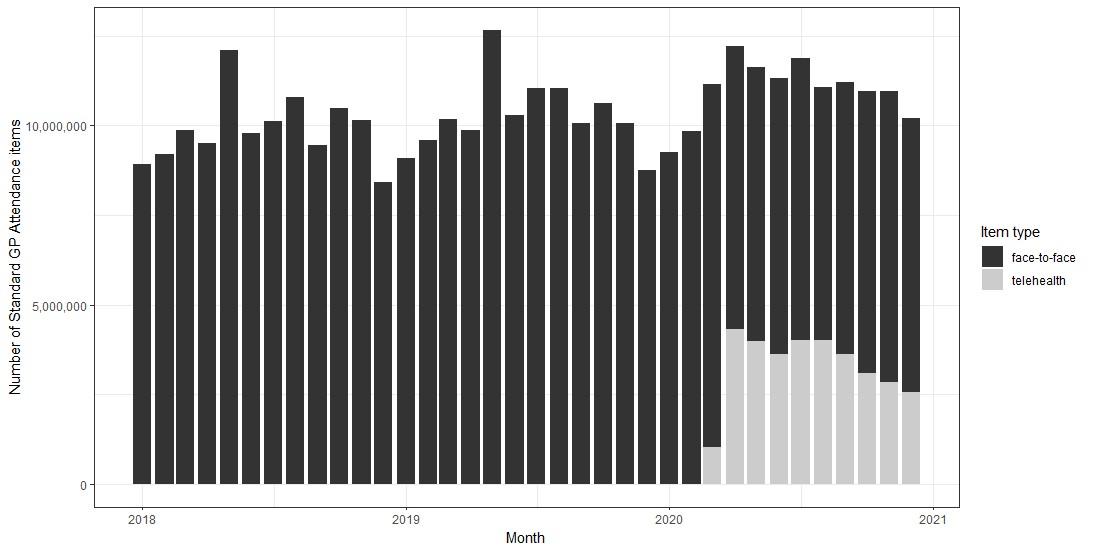
NumberofstandardGPconsultations
Source:Avdic,Kunz,MéndezWisniewska,JHE,2026
Aspectstoconsider
Healthcareprofessionals
Whocanpractisewhere
Telemedicineis
reimbursedif establishedrelationship withpatient.
Volume-basedrules limithowmany telemedicine consultationscanbe provided.
Payment&Reimbursement
Whogetspaidandforwhat
Governmentsubsidies fortelemedicine consultations. Includingphone.
CompetitionandRegulationintheHealthcareSector|SusanJ.Méndez
Data&Interoperability
Whocontrolsinformation
EHRdatatobe uploadedintoMy
HealthRecord
Privacyrulesdesigned fortraditionalcare,not commercialplatforms.