











Coates RD & NHD Editor 5 Up Front
Emma has been a Registered Dietitian for 18 years, with experience in adult and paediatric dietetics.
coatesyRD

Madi Myers ANutr 20 Myth Busting
Madi is a Freelance Nutritionist working with individuals, hosting workshops and writing. She works across the food industry and the private sector, promoting the non-diet approach to nutrition.
non_diet_nutrition nondietnutrition nondietnutrition.co.uk

Voas-Wootton RD 6 Nutrition in the News
Karen is a Community Prescribing Support Dietitian and Team Lead at Betsi Cadwaladr. She has a keen interest in appropriate prescribing and nutritional support.
Monday-Jones RD 8 Skills & Development
Holly is a Clinical Acute Dietitian and Student Lead for Betsi Cadwaladr University Health Board Central area and founder of HMJNutrition Services and HMJ Wellbeing Solutions.

Choudhury ANutr 22 Public Health
Farihah is a Public Health Nutritionist for Southwark Council. She is particularly interested in food policy, noncommunicable diseases, sustainable diets, food culture and anthropology.
easypeasysustainability farihahchdhry www.farihahchoudhury.com
HMJ Nutrition Services HMJWellbeing

27 Paediatric
Aqsa graduated from the University of Westminster with a BSc in Human Nutrition, the University of Lancashire with an MSc in Dietetics and recently completed her placement at Wirral University Hospital Trust.
Rojas El Yammouni RD 11 Weight Management
Vanessa is an Obesity and Diabetes Specialist Dietitian who supports patients in achieving sustainable health outcomes. She is also the author of The Success of Not Dieting: Say Yes to Carbohydrates!
Hola Nutri Clinic Holanutriclinic www.holanutriclinic.com

Priya Tew RD 30 Food for Thought
Priya is a Specialist Eating Disorders and IBS Dietitian. She runs Dietitian UK, works with the media and is the author of The DASH Diet and The Complete Low FODMAP Diet Plan.
Injore RD 15 Gut Health
Joanna is a Specialist Oncology Dietitian with over 20 years’ experience in the NHS, charity and private sector. She works at Macmillan Cancer Support and is the owner of JI Nutrition.
JINutrition
ji_nutrition JInjore www.jinutrition.co.uk

Ursula has a degree in dietetics and works as a Freelance Writer in nutrition and dietetics.
ursula-arens
Fareeha Jay RD 38 The Last Word
dietitian_fareehajay fareehaJay www.fareehajay.com
priya_tew priyatew priyatew www.dietitianuk.co.uk
Giuliana is a Programme Manager at University College Dublin. She delivers nutrition workshops and mentors for cooking programmes, providing advice on sustainable diets and healthy food choices to individuals, families and communities.
Alka, a Specialist Dietitian at Buckinghamshire Healthcare NHS Trust and founder of Nutrivibes with Alka, is a qualified health coach passionate about promoting health awareness in South Asian communities.
nutrivibeswithalka alka-pandey giulianarocca aqsamahmood
Fareeha is a Freelance Dietitian providing specialist advice to South Asians across the globe and has developed the South Asian Eatwell Guide.


5 Emerging roles in dietetics
6 Latest industry and product updates
& DEVELOPMENT
8 The expanding position of the advanced practitioner WEIGHT MANAGEMENT
11 Obesity jabs: where are we now?
15 Diet, health and emerging links to cancer FACE TO FACE
19 Ursula meets Deborah David

MYTH BUSTING
20 Sea moss: separating tradition from science
PUBLIC HEALTH
22 The ultra-processed foods debate
PAEDIATRIC
27 Paediatric food allergy
FOOD FOR THOUGHT
30 When whole food advice ignores real life
DIET & LIFESTYLE
32 Harnessing blue foods for health
CLINICAL
35 Micronutrient deficiencies in critical care
THE LAST WORD
38 Influences behind food choices
Copyright 2026. All rights reserved. NH Publishing Ltd. Errors and omissions are not the responsibility of the publishers or the editorial staff. Opinions expressed are not necessarily those of the publisher or the editorial staff. Unless specifically stated, goods and/or services are not formally endorsed by NH Publishing Ltd which does not guarantee or endorse or accept any liability for any goods, services and/or job roles featured in this publication. Contributions and letters are welcome. Please email only to publisher@networkhealthgroup.co.uk and include daytime contact phone number for verification purposes. Unless previously agreed all unsolicited contributions will not receive payment if published. All paid and unpaid submissions may be edited for space, taste and style reasons.
Editor Emma Coates RD
Publishing Director Julieanne Murray
Publishing Editor Iona Tulloch
Subeditor Lisa Pritchard
Copy Assistant Sue Vane
Website Content Coordinator Erin Dearlove
Marketing Coordinator Ava Blackwood
Design Douglas
Advertising Manager Richard Mair
Tel 01342 824073
richard@networkhealthgroup.co.uk
REFERENCES All references can be accessed here: www.NHDmag.co.uk/article-references.html ISSN 2398-8754
Phone 01342 824073
Email publisher@networkhealthgroup.co.uk www.NHDmag.co.uk
Address
Suite 1, Forest Row Village Hall, The Square, Lewes Road, Forest Row, East Sussex RH18 5ES
@networkhealthdietitians
@nhd _health_dietitians
@NHDmagazine
linkedin.com/company/nh-publishing
Hello and welcome to the June issue of NHD Magazine. This month marks Dietitians Week 2026 (1–5 June). ‘More than just a job’ is the theme, highlighting the vital role of dietitians and celebrating the breadth and impact of the profession across healthcare settings.
It seems timely, therefore, to discuss advanced practice, a key workforce lever in delivering the NHS 10 Year Health Plan, improving access to care, supporting a sustainable workforce and enabling multidisciplinary teams to provide safe, effective services. For almost a decade, the NHS has supported the development of advanced practitioner roles across a range of settings and disciplines. These roles often involve managing complex patient needs, delivering patient-focused care and driving innovation and quality.
In 2017, the NHS published its first framework for advanced practitioners –healthcare professionals who play a vital role in an evolving healthcare system. The framework sets clear expectations across leadership, clinical care, education and research, and has since been updated to reflect emerging evidence and practice. This model has been readily adopted within the dietetic profession.
The Advanced Practitioner in Dietetics is a growing area of expertise. We now see evolving senior and expert dietetic roles that align with the NHS Advanced Practice Framework. Within these roles, dietitians are working autonomously, managing complex clinical cases incorporating advanced decision-making and accountability, while contributing strategically to education, leadership and service improvement.
The BDA and HCPC support the development of these roles through resources and training. The BDA Advanced Practice Specialist Group


provides a network for those working in, or aspiring to, this career path.1-3 The HCPC has produced downloadable content and webinars that cover scope of practice, supervision and effective management of advanced practitioners.4
The impact of dietetic advanced practitioner roles is documented in BDA case studies. These highlight some of the key benefits of advanced practice, including improved patient outcomes and experience, cost effectiveness and strengthened workforce sustainability. One case study acknowledged that dietitian advanced practice roles in neuro-rehabilitation services can support better patient outcomes as a result of improved access and continuity of care.5 More research found that prescribing dietitians may have a significant impact on prescribing costs within the NHS.6
Jones RD, who brings us up to date on emerging roles, the increasing need for advanced practitioners in dietetics and the benefits and challenges involved.
Turning to someone who has been no stranger to chatting with dietitians and healthcare professionals working in varied and advanced roles, Ursula Arens shares her final Face to Face with us this month. As many readers know, Ursula has been a long-standing member of the NHD writing team, contributing countless features and book reviews over the years. We thank Ursula for her wonderful input and wish her all the best in her next chapter. This really is the end of an era! Enjoy this month’s Face to Face where Ursula meets Deborah David, bone health expert and Nutrition and Dietetics Consultant. And thanks as always to you for joining us.
If you’d like to read more on this, check out the article by Holly Monday- Emma
Enjoy the read!
Karen Voas-Wootton’s digest of nutrition news with clinical relevance


New research from Lund University suggests that the way weight gain occurs during adulthood may be as important as how much weight is gained.1 In a large cohort of over 600,000 individuals, earlier onset of weight gain – particularly between ages 17 and 29 – was associated with a substantially higher risk of premature mortality compared with later weight gain.
Findings indicate that prolonged exposure to excess adiposity may drive this increased risk, particularly for cardiometabolic outcomes. Interestingly, cancer risk in women did not vary by timing of weight gain, pointing to potential hormonal influences. For dietitians, the study reinforces the importance of early prevention strategies and sustained weight management support across the life course.


Dietitians can now renew their registration with the Health and Care Professions Council (HCPC) until the closing date of 30 June 2026. Renewal, required every two years, involves confirming continued compliance with HCPC standards, updating details and paying the fee online. A small proportion of dietitians (2.5%) will be selected for CPD audit and must submit a portfolio and personal statement. Those selected will be notified directly, and all registrants must complete renewal regardless of audit status. A great way to stay up to date with CPD is via NHD’s comprehensive CPD articles, which can be accessed here: www.nhdmag.co.uk/cpdearticles.html

A five-day-per-month fasting-mimicking diet may offer a helpful add-on approach for people with mild-to-moderate Crohn’s disease.2 In a recent Stanford-led trial, adults followed a low-calorie, plant-based diet for five consecutive days each month, returning to their usual eating patterns the rest of the time. After three cycles, around 70% reported an improvement in symptoms, with more people reaching remission compared with those who made no dietary changes.
These improvements were also reflected in lower levels of key inflammation markers. While not a replacement for medication, this short, structured approach may be easier to follow than ongoing restrictive diets, highlighting the potential of nutrition as part of Crohn’s care.
Maintaining a healthy weight may depend on what people eat and when they eat. A large study involving over 7000 adults followed for around five years found that eating patterns aligning with the body’s natural rhythms were associated with lower BMI over time.3 Participants who extended their overnight fast and ate breakfast earlier tended to have healthier weight outcomes. Researchers suggest this may reflect better alignment with circadian biology, supporting appetite regulation and energy use. However, skipping breakfast as part of intermittent fasting did not show the same benefit and was also linked to less healthy lifestyle patterns in some groups.
While findings support chrononutrition approaches, researchers caution that evidence is not yet strong enough for formal dietary recommendations.

…that cooking methods may significantly influence the nutritional value of everyday vegetables?
Researchers at the University of Seville’s Food Colour and Quality Laboratory in Spain examined how cooking methods affect carotenoid bioavailability in tomatoes and carrots. Methods included oven, microwave and air fryer preparation.4
Findings showed that bioavailability varied markedly with technique. In carrots, oven cooking increased total carotenoid bioavailability up to nine-fold. In tomatoes, air frying at 190°C for 10 minutes and conventional oven baking at 180°C for 20 minutes produced similarly high values, with about a 1.5-fold increase over raw tomatoes. Vitamin A precursor carotenoids showed particularly large gains. Microwave cooking of carrots and air frying of tomatoes also offered superior energy efficiency.
The research highlights sustainable cooking approaches that improve nutrient absorption while reducing electricity use, with potential implications for health guidance.

A new study suggests around 10% of patients may have a genetic form of GLP-1 resistance, reducing response to GLP-1 receptor agonists such as Ozempic and Wegovy.5 Researchers found that variants in people’s genes may impair biological signalling despite higher circulating GLP-1 levels. In clinical trials, carriers of these variants were less likely to reach glycaemic targets on GLP-1 therapies, although responses to other diabetes medications were unaffected.
The findings highlight emerging precision medicine considerations in obesity and T2D management. While weight-loss effects remain uncertain, experts suggest some patients may require alternative or longer-acting formulations.

The Advanced Practitioner (AP) Dietitian is set to play an important role in strengthening the dietetic workforce and addressing healthcare service pressures. While the dietetic AP role is relatively new, it is expected to expand as healthcare systems continue to prioritise other multidisciplinary AP roles.
The majority of dietitians in the UK currently work in the NHS, typically in supportive or specialist roles within multidisciplinary healthcare teams (MDTs).1 NHS work usually focuses on nutrition therapy of some kind or service user education. For dietetics to continue moving forward in a world of increasing healthcare demands, significant workforce shortages and service users with increasingly complex disease states, further conversation is required to ensure we can manage current and future healthcare challenges at a national level.
An AP is a healthcare professional working at a high level of practice, usually requiring a master’s level of education.2 There are usually two types of AP in the UK: those from a nursing background – otherwise known as Advanced Nurse Practitioners (ANP) – and those from an Allied Health Professional (AHP) background. The training for both ANPs and AP AHPs focuses on the four pillars of advanced practice: clinical practice; leadership and management; education; research.2
In dietetics, there are currently very few advertised AP jobs and available roles. In reality, however, many dietitians work at an AP level without being in an official AP job role. There are also increasing numbers of dietitians who have obtained an AP AHP master’s degree, without then working within an official AP job role.
From a clinical practice perspective, dietitians working in a recognised AP role typically undertake responsibilities traditionally associated with medical staff. This could be conducting advanced and comprehensive patient assessments, interpreting clinical and biochemical test results, planning complex care for service users, including developing and implementing treatment plans and adjusting complex nutrition interventions relatively independently.3 AP dietitians working in these official job roles typically rely less heavily on medical staff oversight and are more in control of their workloads.
AP dietitians can perform a variety of complex tasks. They may prescribe nutrition-related medications and intravenous infusions. This includes managing refeeding syndrome treatments and parenteral nutrition. They may also handle the insertion and care of enteral feeding tubes and lines. Furthermore, they can clinically lead management for specific patient groups where diet and nutrition are vital.
Nutrition support teams are finding it increasingly difficult to obtain and/or retain medical staff with an interest in or experience of nutrition. AP AHP and ANP roles are becoming more common in this area to facilitate sound and complex nutrition-related decision-making.
Autonomy from a clinical practice perspective has significant benefits. The more autonomous an AP dietitian is, the more streamlined patient care can be.4 Service users may prefer and/ or appreciate having a more holistic approach to their care, and an AP dietitian may be a better fit for some people in terms of comprehensive management of their care.

Holly Monday-Jones RD
In today’s healthcare world, autonomous practice is becoming essential in meeting increasing healthcare demands. Improving service user care and satisfaction has to be at the forefront of healthcare. Moving away from the typical pathway of medical staff-led services is a newer concept, but it will become more important in meeting healthcare demands.5,6 The NHS has struggled for many years due to a lack of funding, poor retention of staff and increasing population levels.5
Fixing the problems is intrinsically and extrinsically difficult, which places the NHS in a precarious position. The NHS needs to undergo a significant shift to improve services in a way that does not overly rely on external agencies and needs to better adapt to changing circumstances. Moving away from medical-led services in some cases is a good starting point.
There is evidence that efficacy and efficiency can be improved in services where diet is a primary focus if AP dietitians are leading them.7,8 Evidence also supports the fact that burnout, attrition, over-reliance and adverse well-being issues are rife within the medical staff sector.9
The new generation of AP dietitian roles would help fill gaps in healthcare staffing and reduce the burden on medical staff. This would improve NHS retention, rates of sickness, absence and burnout. AP dietitians can act as clinical leads within their specialist areas, providing significant long-term benefits for the health service.
AP dietitians can do much more than clinically lead. They contribute to strategic planning within healthcare organisations and are involved in many operational changes within dietetic departments at a local and national
level. Leadership tasks outside the clinical domain include mentoring/ coaching less experienced dietitians and implementing non-nutritionrelated changes such as well-being, engagement and peer support services within departments.
Implementing change is typically through education or research and development practices. AP dietitians conduct clinical research, evaluate service effectiveness and encourage regular implementation of evidencebased practices through effective communication. This ensures that dietetic practice remains aligned with current evidence and healthcare needs.
Further development and integration of AP dietitians within healthcare settings will enhance

career progression for dietitians. Clearly defined advanced career pathways, alongside opportunities for continued professional development and specialisation, strengthen the profession. Expanding the number of AP dietitians raises recognition of dietetic expertise, highlighting the critical role dietitians play in clinical decision-making and improving patient outcomes.
Although increased numbers of AP dietitians are a necessity to offset the demanding and ongoing healthcare challenges, there are potential challenges and barriers to implementation:
• AP roles can overlap with other healthcare professions.10
• AP roles require postgraduate education, which may put many people off. An experienced clinician may not have the time to complete postgraduate study and employers may not wish to pay for this.
• More experienced workers within healthcare systems are
more likely to be older and have additional responsibilities outside the workplace, such as children or caregiving responsibilities.
• AP roles improve retention of other staff professions (eg medical staff), but without significant financial backing, health employers may not be able to invest in APs.11
AP training needs to be attractive for both the individual undertaking it and the employer to support it. Some solutions to the challenges and barriers outlined include the following:
• Clear role definitions are needed to reduce overlap and optimise multidisciplinary collaboration.10
• AP education must be simple but useful and effective to ensure recruiting ability.
• Keep training as local as possible to the workplace to ensure minimal
travel and time away from both the workplace and home.
• Government funding could minimise employer financial burden. With financial support, employers could allow scheduled study time to allow employees to attend further study opportunities without falling behind at work. Employers would reap the rewards of more advanced clinicians, leaders and educators in the workplace and retention of staff would improve, due to increased job and promotion opportunities.
• Consider AP training in-house, rather than relying on training at a university level. This would negate the need for significant financial support from external agencies and would be attractive to employees.
• Not all universities offer AP programmes, so if universities must be used for training purposes,
the development of more local courses would be useful.
The bottom line is that healthcare organisations must support AP roles through funding, workforce planning, policy development and organisational change.
Investment in dietetics and ongoing AP training is essential to deliver much-needed benefits in healthcare for the UK population. Alongside this, some outside-thebox thinking is required to allow the NHS to significantly change for the better. In a healthcare system where efficiency is critical and current time pressures are high, developing the AP role in dietetics – as well as across therapy and nursing – is vital to managing the growing UK healthcare caseload.

The management of obesity has changed dramatically over the past few years. What was once framed as a debate between lifestyle intervention and pharmacotherapy has evolved into a more complex clinical landscape. The focus is no longer on whether medications should be used, but how they can be integrated safely and effectively into long-term care –bringing into focus both advances in pharmacotherapy and the vital role of dietitians in managing associated opportunities and risks.
For dietitians working in the UK, this shift has important implications. Our role is expanding beyond traditional weightmanagement counselling into a broader clinical partnership that focuses on preserving metabolic health, muscle mass and long-term nutritional status.
In clinical practice, medications targeting the glucagon-like peptide-1 (GLP-1) pathway have become a cornerstone of obesity management. These medications work by slowing gastric emptying, enhancing satiety and regulating appetite signals within the brain.
This pharmacological landscape has evolved rapidly, moving from single-receptor GLP-1 agonists to multi-receptor agents capable of influencing several metabolic pathways simultaneously. This has resulted in greater weight loss outcomes, but also greater physiological impact on the body. Table 1 summarises the key pharmacological developments shaping obesity care in 2026.
One of the most significant developments in obesity pharmacotherapy in recent years has been the emergence of highly potent multi-receptor agonists. These medications target several hormonal pathways involved in appetite regulation, glucose metabolism and energy balance and are showing substantial promise in the treatment of obesity.
One example is tirzepatide, a dual agonist that acts on both glucose-dependent insulinotropic polypeptide (GIP) and GLP-1 receptors. Clinical trials have demonstrated mean weight


Medication/classMechanism
Semaglutide (Wegovy)GLP-1 receptor agonist
Standard 2.4mg dose associated with ~17% weight loss in trials. Higher maintenance doses are now emerging.1
Wegovy 7.2mg High-dose GLP-1 agonist Results from the STEP UP phase 3b trial of semaglutide 7.2mg demonstrated a mean weight loss of approximately 20–21% over 72 weeks in adults with obesity.2
Tirzepatide (Mounjaro) Dual GIP and GLP-1 receptor agonist
CagriSema GLP-1 agonist and amylin analogue
Orforglipron Oral small-molecule GLP-1 receptor agonist
In the SURMOUNT-1 phase 3 trial, tirzepatide 15mg taken once weekly produced a mean weight loss of approximately 22.5% at 72 weeks in adults with obesity.3
In the phase 3 REDEFINE clinical programme, the combination therapy CagriSema produced a mean weight loss approaching 23% over approximately 68–84 weeks in adults with obesity.4
In the phase 3 ACHIEVE-3 trial, once-daily oral orforglipron produced approximately 9–10% mean weight loss in adults with T2D.5 Table 1: The

reductions approaching 22–23% at the highest therapeutic dose, with a proportion of participants achieving reductions of 25% or more of their baseline body weight. These outcomes are noteworthy because they begin to approach the magnitude of weight loss typically associated with some bariatric procedures, such as sleeve gastrectomy.
Another widely used medication is semaglutide, which is currently approved for weight management within UK clinical services. Standard dosing has already demonstrated substantial efficacy in supporting weight loss in people living with obesity. More recently, higher-dose maintenance strategies are being investigated to support individuals who reach a plateau with the current 2.4mg dose, with emerging data suggesting the potential for further improvements in weight loss outcomes.
A further development attracting considerable clinical interest is CagriSema, a combination therapy that pairs semaglutide with cagrilintide, an amylin analogue. By acting on complementary appetite-regulation pathways, this therapy appears to enhance satiety and reduce overall food intake, resulting in significant weight loss outcomes in clinical trials.
For many individuals who have
struggled with long-term weight management, these pharmacological options represent an important advancement in treatment. However, the degree and speed of weight loss observed with these therapies raise important clinical considerations. As weight reduction becomes more pronounced, careful attention must be paid to nutritional adequacy, preservation of lean muscle mass and long-term metabolic health. In this context, the role of the dietitian becomes essential in ensuring that pharmacological treatment is supported by appropriate nutritional guidance and monitoring.
Until recently, most GLP-1 medications required weekly injections. While effective, the injection route presented a barrier for some individuals. A major development this year is the emergence of oral GLP-1 receptor agonists that do not require the strict fasting conditions associated with earlier formulations.
Orforglipron, a non-peptide small-molecule GLP-1 receptor agonist, is currently one of the most promising examples. Findings from the ACHIEVE-3 trial, published in The
Lancet, showed that orforglipron taken once daily produced an almost 10% weight loss in individuals with T2D.5 Although this figure is lower than the outcomes seen with injectable agents, the convenience of an oral medication may significantly improve adherence in real-world settings. For many patients, removing the barrier of injections could increase accessibility and long-term treatment engagement.
For dietitians, this means we may see a broader population using pharmacological weight-management strategies, including individuals earlier in the disease pathway.
As these medications move from shortterm trials into long-term clinical use, attention is turning towards safety and metabolic consequences beyond weight loss. Two areas are currently receiving particular attention: bone health and lean muscle preservation.
Emerging discussions within the clinical community have raised questions about the potential skeletal implications of long-term use of GLP-1 receptor agonists. As these medications can lead to significant and sometimes
Protein intake
Bone health
Hydration
Gastrointestinal tolerance
rapid weight loss, concerns have been expressed regarding their possible impact on bone health over time. Some observations suggest that individuals using these therapies for prolonged periods may experience changes in bone metabolism that could increase susceptibility to conditions such as osteoporosis or reduced bone mineral density.6 Although the magnitude of this potential risk is still being explored and current evidence remains limited, the topic has highlighted an important consideration in obesity management.
For patients undergoing substantial weight reduction, whether through pharmacological treatment or other interventions, bone health must not be overlooked. From a dietetic perspective, ensuring adequate intake of key nutrients, such as calcium and vitamin D, alongside encouraging appropriate resistance or weight-bearing exercise, remains an important component of comprehensive care.
Rapid weight loss is rarely composed purely of fat mass. Studies suggest that 15–25% of weight lost through pharmacotherapy may come from lean muscle tissue.7 Loss of skeletal muscle can reduce resting metabolic rate and may increase the risk of weight gain if medication is discontinued. From a functional perspective, reduced muscle mass can also affect mobility, strength and long-term health outcomes. For this reason, preserving lean mass is becoming a central priority in obesity management.
The increasing complexity of obesity
Aim for approximately 1.2–1.5g protein per kg adjusted body weight to support lean muscle mass preservation.
Ensure adequate calcium intake (700–1000mg daily) and vitamin D (10µg daily) alongside weight-bearing or resistance exercise.
Monitor fluid intake closely; appetite suppression may also reduce thirst signals. Recommendations from 2-2.5L/day.
Encourage small, nutrient-dense meals and gradually increase fibre intake to minimise constipation.
pharmacotherapy has placed dietitians in a pivotal position within the care pathway. Rather than focusing solely on calorie reduction, our work now centres on protecting body composition, supporting nutritional adequacy and managing medication-related side effects. Table 2 outlines key areas where dietetic intervention can support patients using obesity medications. In clinical practice, patients often report that appetite suppression makes it difficult to meet basic nutritional requirements. Reduced food intake can unintentionally lead to inadequate protein, micronutrients and overall energy intake. This is where structured dietetic guidance becomes essential and multivitamin recommendations might be necessary.
Many individuals beginning pharmacotherapy are primarily focused on the number on the scale. However, sustainable health outcomes depend on far more than weight reduction alone.
Dietitians play an important role in helping patients develop sustainable dietary patterns that support long-term metabolic health. This includes:
• Prioritising adequate protein intake
• Maintaining micronutrient sufficiency
• Preserving muscle mass through nutrition and resistance exercise
• Preventing gastrointestinal complications
• Preparing patients for potential weight maintenance phases Importantly, patients also need guidance on what happens if medication is stopped. Without appropriate dietary and behavioural strategies, weight regain remains common.
Obesity is increasingly recognised as a chronic condition requiring long-term management. Pharmacotherapy can provide powerful metabolic support, but it does not replace the need for nutritional care.
In many ways, these medications act as a biological ‘assist’, helping to regulate appetite and metabolic pathways that may previously have been resistant to lifestyle intervention alone. However, without structured nutritional support, patients may still face risks such as muscle loss, micronutrient deficiencies and reduced bone density. For this reason, the most effective obesity care models are multidisciplinary. Collaboration between physicians, dietitians, psychologists and exercise specialists is becoming increasingly important.
The treatment of obesity is a rapidly changing field. New drugs are delivering levels that were previously impossible to achieve without surgery. Many patients consider this a significant breakthrough. However, these potent pharmacological tools bring new clinical challenges. This year, we will see the dietitian's role becoming more significant, as our efforts shift from just aiding weight loss to safeguarding metabolic health during rapid weight reduction. Care now involves ensuring that individuals consume sufficient protein and maintain healthy bones and lean muscle mass.
DEVELOPMENT OF THE GUT MICROBIOME
The gut microbiome colonisation begins at birth and develops throughout life.5 Various factors shape the gut microbiota in early life, such as the maternal microbiota composition (influenced by maternal diet), birth delivery (vaginal versus caesarean section), genetics, antibiotic exposure and feeding practices (breastfeeding versus bottle feeding).5,6 The gut microbiome remains dynamic and responds to external factors throughout life.
The gut microbiota can be described as in balance (eubiosis) when the host’s health is supported by the gut’s microbial metabolites. It can also be imbalanced (dysbiosis) when there is a dominance of

Joanna Injore RD
harmful microbes or a reduction in beneficial microbes. This is associated with a wide range of chronic conditions, including metabolic disorders, gastrointestinal disease and cancer.5
CORE FUNCTIONS OF THE GUT MICROBIOME IN HEALTH
The gut microbiome is identified as having several key functions in the body.
Metabolic function
The gut microbiome ferments dietary fibre in the upper gastrointestinal tract, which produces short-chain fatty acids (SCFAs), including acetate, propionate and butyrate.7,8 These SCFAs fuel colonocytes, regulate lipid and glucose metabolism and influence appetite and insulin sensitivity.7,8
The microbiome contributes to the synthesis of essential nutrients, including vitamin K and several B vitamins. It also influences bile acid metabolism and the bioavailability of dietary polyphenols.7
Immune function
The gut microbiome plays a fundamental role in the development and regulation of the immune system. Through interactions with gutassociated lymphoid tissue, microbes help train T cells to distinguish between harmful and harmless stimuli.9 The microbiome also contributes to maintaining the integrity of the intestinal barrier by maintaining mucus production, tight junction integrity and epithelial renewal.9 Disruption of this barrier can allow microbial components, such as lipopolysaccharides, to enter the circulation, triggering systemic inflammation.9
Gut-brain axis
Exciting emerging evidence highlights the role of the microbiome in neuroendocrine signalling via the gut-brain axis. Microbial metabolites and cell components influence the nervous system signalling, vagal activity, neurotransmitter production and neuroinflammation, which can impact mood, cognition and pain.9
Diet is one of the most powerful and modifiable influences on gut microbiome composition, with several dietary factors, such as fibre intake, dietary patterns, prebiotics and probiotics, having a role. Remarkably, dietary patterns can induce measurable changes in microbial communities within 24 hours to a few days.10





Diet type
Microbiota changes (increased)
Plant-based Bifidobacterium, Eubacterium, Roseburia, Faecalibacterium
Mediterranean Bifidobacterium, Prevotella, Firmicutes, Lactobacillus
Meat-based Enterobacteria, Ruminococcus
Processed Firmicutes
Diets rich in plant-based foods and dietary fibre are consistently associated with increased microbial diversity and higher production of SCFAs. Fibre acts as a substrate for beneficial bacteria, promoting a metabolically favourable environment within the gut. A meta analysis of 64 RCTs confirmed that fibre – particularly fructans and galactooligosaccharides – leads to higher faecal abundance of Bifidobacterium and Lactobacillus microbial species.11 In contrast, dietary patterns characterised by high intakes of saturated fat, refined sugars and low fibre are associated with reduced microbial diversity and an increase in pro-inflammatory species (see Table 1).12
DISEASE DEVELOPMENT
When the microbiota balance is affected, it can lead to dysregulation of the body’s various functions and disease (see Table 2). Growing evidence suggests that the microbiota is associated with
Microbiota changes (decreased)
Clostridium, Enterococcus
Clostridium, Enterococcus
Bifidobacterium, Eubacterium, Roseburia, Faecalibacterium
Akkermansia, Faecalibacterium, Lachnospira, Roseburia
Key metabolites/ products Main physiological effects
SCFAs (butyrate, acetate, propionate)
SCFAs (butyrate, acetate, propionate)
Choline, carnitine, trimethylamine
Lipopolysaccharides, long-chain fatty acids, cytokines
the development of cardiovascular disease, cancer, respiratory diseases, diabetes, inflammatory bowel disease, brain disorders, chronic kidney diseases and liver diseases.13 Gastrointestinal conditions, including inflammatory bowel disease and inflammatory bowel syndrome, are characterised by reduced microbial diversity, altered SCFA producers and loss of beneficial species.14
GUT MICROBIOME AND CANCER
In 1994, it was discovered that
Maintains blood-brain barrier; maintains intestinal integrity
Maintains intestinal integrity; improves inflammation and lipid profile
Increased cardiovascular disease risk; atherosclerosis
Systemic inflammatory response
Helicobacter pylori contributes to gastric cancer. More recent studies have shown that microbiota play an important role in carcinogenesis, mainly through:
1) Influencing the host cell proliferation and death
2) Altering immune system activity
3) Affecting host metabolism13
The strongest evidence exists for colorectal cancer, where microbial dysbiosis is well documented. Increased abundance of Fusobacterium nucleatum has been associated with tumour progression,15 while beneficial butyrateproducing bacteria are often reduced.
Table 2: Microbiota dysbiosis and contribution to various diseases13
Inflammatory bowel disease
Liver disease
Crohn’s disease
Ulcerative colitis
Cirrhosis
Hepatitis
Chronic kidney disease ~
Brain disorders
Parkinson’s disease
Alzheimer’s disease
Depression
Diabetes T1D
T2D
Gestational
Respiratory disease Asthma Bronchitis
Cancer Lung
Colorectal
Pancreatic Oral
Heart disease








Hypertension
Atherosclerosis








Dietary patterns play a key role, with high red meat and low fibre intake linked to increased colorectal cancer risk via microbial metabolism.16
Evidence increasingly shows that the gut microbiome can influence responses to cancer treatments. Gut microbes can enhance, abolish or worsen the effects of drugs such as 5-fluorouracil, cyclophosphamide, irinotecan, oxaliplatin, gemcitabine and methotrexate.17 A recent systematic review of 22 clinical studies found that specific groups of microorganisms were associated with better or worse chemotherapy response and toxicity in lung and gastrointestinal cancers.18 This evolving area of research may lead to using microbiome profiles to personalise cancer treatment in the future.
The gut microbiome plays a central role in human health, influencing metabolic, immune and neuroendocrine processes. Its involvement in disease, including cancer, highlights its clinical relevance. As diet remains one of the most important and modifiable factors shaping the microbiome, nutrition professionals play a central role in translating this evidence into practice. Emphasising diverse, fibre-rich dietary patterns and evidence-based strain-specific probiotics offer a practical and evidencebased approach to supporting gut health, while ongoing research will continue to refine our understanding of how best to target the microbiome for disease prevention and improved clinical outcomes.






































































We have floated past each other at many events over the years, so it was my pure delight to meet with Deborah David, bone health expert and Nutrition and Dietetics Consultant, at a charming venue in Central London. Coffee was lovely – as were the career nuggets she shared.
Dietetics was not Deborah’s first career choice. She initially graduated with joint honours in Microbiology and Zoology from Swansea University in 1979 and worked in a laboratory researching antimalarial parasites and vaccines. She then obtained a Postgraduate Certificate in Education (PGCE) at Bristol University and taught science in a secondary school. Seeking further expertise in research, Deborah returned to university and obtained a Master’s degree in Virology at Reading University. Back to work was then in a laboratory researching foot and mouth disease, followed by clinical trials management in the pharmaceutical industry, supporting research treatments for arthritis.
A subsequent meeting with a career consultant captured the three themes that define Deborah: nutrition, science and helping people. The profession was obvious; she graduated as a dietitian from the University of Surrey in 2002. Deborah’s first post in the Royal
Hampshire County Hospital, Winchester, was as a research dietitian working on the impact of low-fat diets on breast cancer in menopausal women. She then moved into community dietetics for elderly care. For the next five years, she worked as a dietitian at the Royal Surrey Hospital in Guildford, lectured in nutrition at Kingston University and worked with Professor Sue Lanham-New at the University of Surrey on a variety of research projects, including the vitamin D status of ethnic groups in the UK. She also volunteered on numerous projects supporting policy groups, including The Caroline Walker Trust, The Food Foundation, School Food Matters and The Trussell Trust.
We find common ground, having both attended conferences in the United States, organised by the Academy of Nutrition and Dietetics. These are huge professional occasions with thousands of dietitian attendees; we both enthuse about the energy and positivity of these events. Deborah has attended many times at her own expense, recognising the opportunities for friendships and insights into dietetic global research. She wrote articles for NHD Magazine and Dietetics Today describing her impressions.
Deborah now concentrates on a variety of freelance consultancy projects

covering the food industry, public health and academia. She currently supports teaching sessions in culinary nutrition for fifth-year medical students as part of their GP training.
Deborah’s freelance activities have focused on the importance of bone health through the life cycle, leading her to set up the consultancy service www.bonehealthdietitian.co.uk to provide individual support. She also heads up some interesting projects with the Royal Osteoporosis Society.
We discuss the issue of achieving peak bone density by the ages of 25 and 30 and the natural decline thereafter, with gradients modifiable by diet. Being underweight is a significant risk factor. Communication of higher calcium intakes is important during periods of growth in adolescence, but targeted messaging is difficult when the risk of osteoporosis is in the distant future. As dietitians, we need to keep abreast of research into nutrient associations with bone health, such as calcium, vitamin D and protein intakes, alongside regular physical activity.
Deborah is modest and cautious about promoting herself. I tell her how impressed I am with her many professional activities, but she bats away any praise.
“I have enjoyed the opportunity to review my career,” she says.
And I think, “Typical dietitian!”
Three themes define Deborah: nutrition, science and helping people
Sea moss has rapidly joined the ranks of highly promoted ‘wellness’ supplements, with gels, capsules and powders widely marketed for immune support, gut health, skin, energy and mineral intake. Social media platforms – particularly TikTok – are awash with influencers spooning brightly coloured sea moss gels straight from the jar, often accompanied by claims that it contains 92 essential minerals and can support almost every system in the body. The global sea moss market is now worth an estimated $2.2 billion, despite evidence for the benefits being extremely limited. As with many trending nutraceuticals, popularity has raced ahead of scientific consensus, leaving nutrition professionals to disentangle cultural use, plausible nutrition science and exaggerated marketing claims.
Sea moss is a collective term used for several species of red algae, most commonly Chondrus crispus, often referred to as Irish sea moss. It grows abundantly on rocky Atlantic coastlines in Europe and North America. Many commercial products list ‘sea moss’ without specifying the species, and some supplements may contain other Chondrus species or red algae harvested from Pacific waters.
Traditionally, sea moss has been used in Ireland – notably during the Potato Famine – and in Caribbean cuisines, where it was valued as a thickener for soups, stews and desserts


rather than as a concentrated health product. It has a mild seaweed flavour and forms a gel when cooked, due largely to its carrageenan content. Today, sea moss is most commonly consumed as a thick gel, sometimes flavoured to improve palatability, or in dried form for home preparation. Capsules and tablets made from sea moss extracts are also widely available.
Sea moss is often described as ‘nutrient-rich’, particularly in terms of minerals. It can contain iodine, iron, calcium, potassium and fibre, and sea vegetables more broadly are recognised as sources of phytonutrients. However, nutrient composition varies dramatically depending on species, geographic location, season, processing method and whether the product is fresh or dried. This variability is a critical issue, as many products provide little or no nutritional analysis.
Iodine content is particularly inconsistent. One analysis estimated iodine levels of 6100μg per 100g in fresh seaweed and up to 23,800μg per 100g when dried.1 In contrast, one commercial product that did provide testing data reported 1420μg of iodine per 100g – still extremely high relative to requirements. The often-touted claim that sea moss contains ‘92 vitamins and minerals essential for health’ is rarely backed with analysis, and no authoritative nutrient database supports this statement.
Most health claims associated with sea moss relate to its micronutrient and bioactive compound content. For example, some websites suggest it supports immune function due to its vitamin A and C content. In practice, levels of these nutrients are highly variable and rarely quantified on product labels.
Reviews of sea vegetable consumption more broadly suggest potential anti-inflammatory, antioxidant, antimicrobial and neuroprotective effects, largely attributed to bioactive compounds such as sulphated polysaccharides.2 However, these conclusions are primarily drawn from in vitro and animal studies, not from sea moss-specific human trials. At present, no human intervention studies have examined whole sea moss consumption.
Some human research exists on isolated seaweed extracts. For example, fucoidan and other sulphated polysaccharides are being explored for potential effects on inflammation and gut health.3 One small randomised controlled trial in individuals with inflammatory skin conditions found that a sea algae extract reduced inflammatory markers over six weeks, with some participants reporting skin improvements.4 While promising, this does not provide evidence for sea moss gels or supplements as currently marketed.
Excess iodine intake
While low iodine intakes remain a concern in the UK – particularly among women of childbearing age – sea moss poses a clear risk of excessive intake. The BDA recommends adults consume 150μg of iodine per day, with an upper safe limit of 600μg, and specifically advises against using sea vegetable supplements to meet iodine requirements.
Using the example product opposite, a 30mL (two tablespoon) serving of sea moss gel containing 1420μg of iodine per 100g would provide 426μg of iodine per serving – almost three times the recommended intake and approaching the upper limit.
Some products are promoted for daily use, including in children, without age-appropriate guidance. Excess iodine intake can disrupt thyroid function in both healthy individuals and those with pre-existing thyroid conditions. In addition, susceptibility varies between individuals, making a safe intake difficult to define.5
Heavy metals and contaminants
Sea algae can accumulate heavy metals, including mercury, cadmium,
lead and inorganic arsenic. The sea moss supplement market is largely unregulated, and while some brands claim third-party testing, many provide no evidence of contaminant screening.
Carrageenan content
Irish sea moss is also known as carrageenan moss, as it contains up to 50% carrageenan by dry weight. Carrageenan (E407) is widely used as a food additive but has been the subject of debate regarding gut health. While food-grade carrageenan may not always be transformed into degraded poligeenan (a possible carcinogen) in the body, some in vitro and animal studies suggest carrageenan may increase inflammatory markers.6 Human evidence remains inconsistent, but it is still a potential point of concern for individuals with disorders like IBD.7
Allergies and drug interactions
Allergic reactions may occur in individuals with seafood or shellfish allergies. There is also a theoretical concern regarding interactions with anticoagulant medications, although data are limited.
Sea moss is a traditional food with cultural significance and interesting nutritional properties. However, its modern positioning as a daily health supplement is not supported by robust human evidence. Claims frequently ignore variability in nutrient content and overlook meaningful safety considerations – particularly around iodine. Given the availability of cheaper, safer and better-studied nutrient-dense foods such as leafy greens, oily fish, berries, nuts and seeds, sea moss is unlikely to offer unique benefits for most individuals. Where seaweed intake is desired, more predictable options such as nori (used in sushi) provide a lower-iodine alternative. For nutrition professionals, sea moss is best viewed as a traditional food ingredient rather than a therapeutic supplement – and one that warrants caution, transparency and individual risk assessment rather than blanket endorsement. Interested in reading about blue foods? Giuliana Rocca explores this emerging concept on page 32.



Farihah Choudhury ANutr
categories, proposed by researchers at the University of São Paulo, Brazil ‘NOVA’ comes from the Portuguese NOVA classificação (new classification). The four categories
ocessed or minimally processed foods ocessed culinary ingredients ocessed foods a-processed foods
The definition of UPF as per the classification is: ‘Industrially manufactured food products made up of several ingredients (formulations) including sugar, oils, fats and salt (generally in combination and in higher amounts than in processed foods) and food substances of no or rare culinary use (such as high-fructose corn syrup, hydrogenated oils, modified starches and protein isolates)’.1
Industrial food processing became a popular way of increasing the convenience, profitability and palatability of food products after World War II, accelerating in the 1980s; it has been a rapid income generator for the food industry ever since. The profitability of UPFs compared with other foods has also engendered a predatory campaign by actors in the food industry that monopolises the global food system, targets consumers with marketing and competitive pricing, creates environmental harm and lobbies against
Whilst this classification has dominated the narrative around the relationship between UPFs and nutrition, it was not designed to assess the nutritional quality of foods in isolation or to serve as a nutrient profiling tool. Nonetheless, the level of processing is gaining traction as a way of categorising foods, driven by growing concerns about the public health impact of UPFs.
Many foods that fit the definition of UPFs can be described as high-fat, sugar and salt (HFSS) foods, which have well-established links to poor health outcomes, and well-established public health nutrition guidance to avoid where possible, such as in the UK’s Eatwell Guide.
The estimated overlap between HFSS and UPF foods in the UK is around 56% according to a study published in 2025.2 Inclusion of UPFs that are not under the scope of the current definition of HFSS (such as non-nutritive sweeteners and emulsifiers) would capture close to 100% of UPFs and could incentivise ‘deformulation’ of UPF products, enabling existing policies to have a wider reach.3
This issue has become a major focus of scientific research and ongoing debate among policymakers and healthcare professionals, with widespread discussion across traditional and online media. Capitalising on growing public concern, Marks & Spencer – whose customer base is typically middle class – has launched its ‘Only… Ingredients’ range,4 featuring products with no more than nine ingredients. However, as a premium retailer, with own-brand prices only slightly lower than Waitrose,5 it raises an important question: do initiatives like this meaningfully support those most in need, or do they primarily cater to a health-conscious middle class whose outcomes are already more favourable due to the social determinants of health?
Debate around UPFs centres on the strength of the evidence base for the impacts of processing, and on the validity of NOVA as a singular mechanism for defining UPFs. There is also concern about the implication that widely consumed staples – such as bread, breakfast cereals and even infant formula – should be avoided, which could have unintended public health consequences, particularly given the role of fortification in these foods. These discussions often frame the demonisation of UPFs through the lens of time- and asset-poor households and those most affected by deprivation amid inflated food prices and a UK cost of living crisis. But who really benefits from the proliferation of UPFs… and who loses out?

processing and health outcomes. In the UK’s dietary intake, 56.8% of total energy and 64.7% of free sugars are accounted for by UPFs,6 similar to the US and Canada. In November 2025, The Lancet published a three-part series on UPFs and health, combining systematic reviews and meta-analyses. This series found that UPFs are displacing longestablished dietary patterns in most regions of the world, which historically included foods in groups 1–3 of the NOVA classification (also known as the ‘nutrition transition’).7 It also found associations between UPF intake and conditions including increased risk of overweight and obesity, T2D,
hypertension, CVD, coronary heart disease, depression and all-cause mortality, concluding that UPFs are a key driver of the escalating global burden of multiple diet-related chronic diseases.7,8
The same series explored the possible sources of harm caused by UPFs: nutrient imbalances, overeating, reduced consumption of health-protective phytochemicals, toxic contaminants from processing or packaging, harmful additives and mixtures of additives, and subsequent inflammation, dysglycaemia, dyslipidaemia, microbiome dysbiosis, renal dysfunction and liver dysfunction.7
In 2023, the Scientific Advisory Committee on Nutrition (SACN) carried out a rapid review of evidence.9 Although it confirmed that it found consistent associations between higher

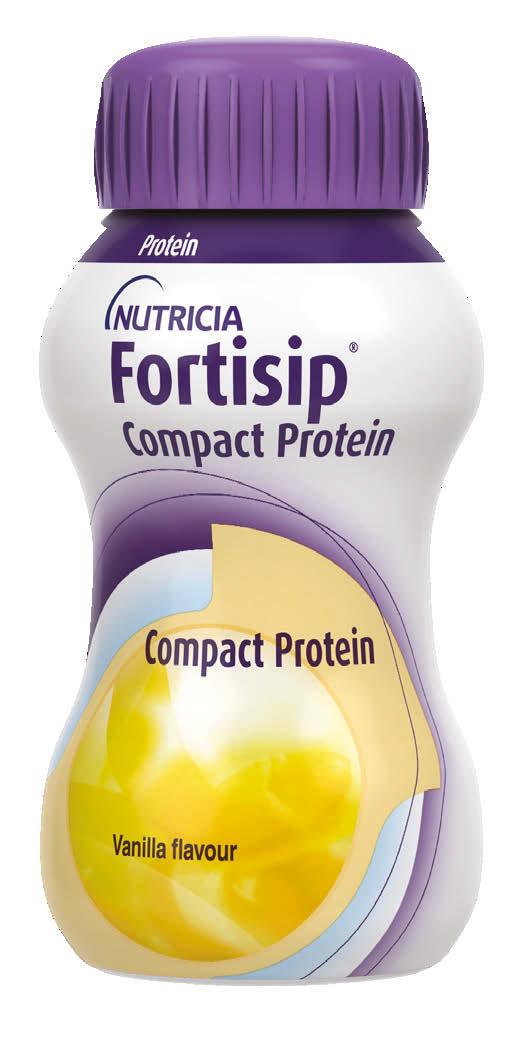
Up to 66% of patients do not meet minimum ESPEN protein requirements3-5
Twice daily Fortisip Compact Protein enables up to 88% of patients to meet their ESPEN protein requirements6
Fortisip Compact Protein has the best taste, by people surveyed, compared to other low volume, high protein ONS7
This is intended for Healthcare Professionals Only
here to ORDER SAMPLES†
Fortisip Compact Protein is a Food for Special Medical Purposes for the dietary management of disease related malnutrition and must be used under medical supervision. 1.Arends et al. Clin Nutr. 2017;36(1):11-48. 2.Muscaritoli et al. Clin Nutr. 2021;40(5):2898-2913. 3.Prado et al.Can J Diet Pract Res. 2012;73(4):e298-303. 4.McCurdy et al.Nutrients. 2019;11(11):2743. 5.Stobaus et al.Nutr Cancer. 2015;67(5):818-24. 6.Dingemans et al.Nutrients. 2023;15(24):5013. 7.2025 data on file - Independent taste research in n=109 healthy adults aged 30-80 years old. 63% (p=0.014) stated a preference for Fortisip Compact Protein peach-mango vs Fresubin Pro Compact apricot-peach; 56% stated a non-significant preference for Fortisip Compact Protein mocha vs Fresubin Pro Compact cappuccino; 65% (p=0.003) stated a preference for Fortisip Compact Protein vanilla vs Fresubin Pro Compact vanilla. European Society for Clinical Nutrition & Metabolism (ESPEN) †Product can be provided to patients upon request of a Healthcare Professional. They are intended for the purpose of professional evaluation only. Accurate at time of publication: March 2026
consumption of UPFs and adverse health outcomes, it concluded there was not yet sufficient evidence to definitively confirm the links between harm to public health and UPFs to affect UK dietary advice. SACN also assessed the suitability of eight mechanisms of food processing to decide on an acceptable UK definition. NOVA is the only classification that was found to be suitable for use in the UK, though SACN noted limitations of its use. This was updated in 2025 with new evidence and the same conclusion, as well as a statement that this would be revisited in 2026.10 The key unknown remains whether the harm of UPFs is due to the processing itself, or due to most UPFs being high in free sugars, salt and/or fat. Conflicts of interest within the policy and research landscape hinder progress towards clear, decisive action on UPFs. A review of conflicts of interest in UK food regulation found that nine of the 15 SACN members received funding from UPF companies at various points in their careers.11
In January 2025, UK Research and Innovation began a year-long project seeking public opinion on processed foods as part of a new initiative intended

to help shape research and policy on UPFs. The findings are due to be reported in 2026.12 Several countries refer to food processing in their national dietary guidelines, including Belgium, Brazil, Norway, Ecuador and Kenya,10 and the UK is being urged by many to do the same.
The food industry has disproportionately profited from the rise of UPFs and continues to do so globally. As reliance on these foods grows, the industry continues to lobby against policies aimed at reducing their consumption. Coordinated resistance against UPFs has been described as a ‘generational opportunity to reclaim food systems for health, equity, and sustainability';13 however, policy change must be done in a way that modifies the food environment and expands the architecture of choice, rather than stigmatises individual choices or creates unintended consequences.
Given the above, the key actions point towards the following:
• Decide upon a clear, universal definition of UPFs.
• Continue to build the evidence base for the impact of UPFs on health.
• For public health guidance, reflect the harms associated with UPFs, ensuring clear messaging to avoid unintended consequences, or emphasis on individual choices.
• Consider key policy levers and tools to reduce the proliferation of UPFs in global diets and consider mechanisms to force the food industry to regulate and reformulate.
award winning chefs and dietitians







Aqsa Mahmood RD, ANutr


Paediatric food allergy is a common and increasingly recognised condition in UK paediatric practice.1 It is defined as an adverse immune response to food proteins and can range from mild reactions to severe, life-threatening anaphylaxis.1 Early recognition, accurate diagnosis and appropriate management are essential to reduce morbidity, prevent nutritional deficiencies and improve quality of life for those affected and their families.1
Paediatric food allergies are broadly classified as IgE-mediated, non-IgE-mediated or mixed IgE/ non-IgE-mediated.2,3 These differ in their underlying immunology, timing of symptoms, clinical presentation, diagnosis and management.
Understanding these distinctions is essential for healthcare professionals to ensure accurate diagnosis and appropriate treatment.2
IGE-MEDIATED FOOD ALLERGY
IgE-mediated reactions occur when food-specific IgE antibodies bind to mast cells and basophils.4 Re-exposure to an allergen triggers the rapid release of histamine and other inflammatory mediators, with symptoms typically developing within minutes to a few hours
and involving multiple organ systems.4
Common features include:
• Skin: Urticaria (raised, itchy wheals) and angioedema (deeper swelling of lips, eyelids or face)4
• Face flushing and pruritus: Transient redness and intense itching4
• Gastrointestinal: Vomiting, abdominal pain, diarrhoea5
• Respiratory: Wheezing, coughing, nasal congestion5
• Anaphylaxis: Diagnosed with airway compromise or involvement of two or more organ systems5
Non-IgE-mediated reactions are driven by T cell-mediated responses rather than IgE antibodies,5 with delayed onset of hours to days after ingestion, predominantly affecting the gastrointestinal tract.5 Typical features include persistent vomiting, chronic diarrhoea, failure to thrive and blood in mucus.5
Common food allergens in children vary with age:
• Infants and young children: Cow’s milk, peanut, egg, tree nuts, wheat, soy6
• Older children and adolescents: Fish, shellfish, sesame Cow’s milk and egg allergies are
frequently outgrown, whereas peanut, tree nut, fish and shellfish allergies tend to persist into adulthood.6
Cow’s milk allergy (CMA)
CMA affects 2–3% of infants and can be IgE- or non-IgE-mediated.7,8
• IgE-mediated: Rapid symptoms include vomiting, wheezing or anaphylaxis.
• Non-IgE-mediated: Delayed gastrointestinal symptoms include diarrhoea, reflux, faltering growth, or food protein-induced enterocolitis syndrome.
• Management: Strict avoidance of cow’s milk protein. Breastfed infants may require maternal exclusion and formula-fed infants may need extensively hydrolysed formula (EHF) where cow’s milk proteins are broken down (eg Nutramigen, Aptamil Pepti and SMA Althera).7 If a baby’s symptoms do not improve on an EHF or the symptoms become severe, an amino acid formula (AAF) can be used (eg Neocate and Nutramigen Puramino), as these contain no intact protein.7,9 These formulas are classed as foods for special medical purposes and are usually prescribed on the NHS with guidance from a GP, paediatrician or dietitian.7 Prognosis is generally good, particularly in non-IgE CMA.7
Peanut allergy affects approximately 1–2% of children.10 Symptoms are mostly IgE-mediated, with rapid onset of urticaria, angioedema, vomiting or anaphylaxis.10 Reactions can be severe and unpredictable with even small amounts of peanut triggering symptoms. Diagnosis is based on a compatible clinical history and evidence of sensitisation on skin prick testing. Strict
avoidance, education about allergen exposure and cross-contamination and provision of adrenaline auto-injections (EpiPen) are approriate.10 Peanut allergy is less commonly outgrown than milk allergy, with only a minority of children developing tolerance.10
Tree nut allergy
This commonly presents in childhood and is usually IgE-mediated, with symptoms including urticaria, gastrointestinal, breathing difficulties and anaphylaxis.6 Common nuts include cashews, walnuts and hazelnuts. Cross-reactivity can occur (eg cashews and pistachios or walnuts and pecan nuts), although not all tree nuts are immunologically related.6 Diagnosis relies on history, allergy testing and, where appropriate, oral food challenges to confirm tolerance to nuts.6
Tree nut allergy is typically persistent, and long-term management focuses on selective avoidance, risk assessment and dietetic support to minimise unnecessary dietary restriction and ensure nutritional adequacy.6
Egg and soy allergy
These can be IgE- or non-IgE-mediated.11
• IgE-mediated: Immediate reactions are triggered by proteins such as ovomucoid (egg) or glycine max proteins (soya).11
• Non-IgE-mediated: Delayed gastrointestinal symptoms occur.11
• Management: Allergy-focused history, skin prick or serum IgE testing
Accurate diagnosis relies on a detailed clinical history, including the suspected food trigger, quantity ingested, timing of symptoms, reactions and presence of cofactors such as intercurrent illness or family history.1
Investigations – In IgE-mediated allergy, diagnostic tools include skin prick testing and serum-specific IgE testing.1 A positive test indicates sensitisation but does not confirm clinical allergy; results must always be interpreted in the context of history. In non-IgE-mediated allergy, investigations are usually unhelpful and diagnosis is clinical.1 Symptom resolution following elimination of the suspected food, with recurrence on reintroduction, supports the diagnosis.1
Oral food challenge – The oral food challenge is the gold standard for diagnosis and is conducted in a controlled specialist environment to confirm allergy or demonstrate tolerance.1 Evidence supports early introduction of allergenic foods, including peanut and egg, around six months of age, particularly in infants with eczema. Delayed introduction is no longer recommended and maternal dietary avoidance during pregnancy or breastfeeding has not been shown to prevent food allergy.1
Allergen avoidance – Management begins with strict avoidance of the

education on food labelling, crosscontamination and appropriate food substitutions to prevent unnecessary restrictions.13
Anaphylaxis – This is a medical emergency and requires an immediate dose of adrenaline via auto-injection.13 While mild to moderate reactions may be managed with oral antihistamines and observation, antihistamines and corticosteroids are not first-line treatments for anaphylaxis. Education on correct use and the importance of carrying these devices at all times is essential.13
Nutritional management – Dietetic input is crucial to ensure nutritional adequacy, particularly for children with CMA or multiple food allergies.7 Suitable alternatives include EHF or AAF when required.12 Monitoring growth and micronutrient intake is a key component of ongoing care.13
School and childcare management –Children with food allergy require a written allergy plan, staff education and clear protocols for emergency management in schools and childcare settings.13 Risk minimisation strategies should balance safety with normal participation in activities.13

Paediatric food allergies remain a significant and evolving challenge for children, families and healthcare systems.14 Early recognition and intervention, accurate diagnosis and evidencebased management are essential to reduce risk and improve quality of life.14 Equally important is empowering families with clear information, practical support and confidence in managing allergies in everyday settings such as schools and social environments.6 Continued research and collaborative care between clinicians, educators and the wider community is key to ensuring that children with food allergies can grow, learn and participate safely in daily life.6



Fish is commonly grouped under the umbrella term ‘seafood’ – a label that reflects historical associations with marine environments and coastal food systems. The emerging concept of ‘blue foods’ broadens this perspective. Blue foods encompass a diverse range of aquatic animals, plants and algae harvested or cultivated in both marine and freshwater environments (see Table 1).1 Closely aligned with the term ‘aquatic foods’, this shift in language signals a growing recognition of the role these foods may play in addressing global challenges.
Recent evidence indicates that blue foods could contribute significantly to the transformation of global food systems. Nutrient-dense,2 they are often associated with lower greenhouse gas emissions and reduced land and freshwater use compared with many terrestrial animal-source foods.3,4 They also support health and well-being and underpin the livelihoods of millions of people worldwide.5,6
BLUE FOODS AND SUSTAINABILITY
Environmental benefits
Blue foods offer environmental advantages and support more sustainable diets. Compared with terrestrial agriculture, aquatic food systems generally produce lower greenhouse gas emissions and require
less land.7 Sea vegetables, clams and oysters are nutrient-dense and can enhance ecosystems by improving water quality.8 However, sustainability depends on responsible practices and monitoring, as overfishing and habitat degradation remain major concerns.9
Nutritional value and health impact
Although blue foods support healthy diets for billions, their nutritional diversity is often undervalued, reduced to protein and energy content of a single seafood or fish type.2 The Aquatic Food Composition Database profiles nutrients for over 3750 aquatic species.2 Due to their high nutrient density, expanding blue food production could prevent an estimated 166 million micronutrient deficiencies by 2030.2 Studies led by the Blue Food Assessment highlight their affordability, cultural relevance and contributions to environmental, economic and social outcomes.1,7
Small-scale fisheries and aquaculture (SSFA)
In the Global South, SSFA are more energy-efficient and environmentally sustainable than industrial fishing,
Classification Examples and included species
Pelagic and salmonidsBig-sized fish, eg tuna, swordfish, salmon
Crustaceans Crab, lobster, crayfish, shrimp
Cephalopods Octopus, squid, cuttlefish
Finfish Herring, sardine, cod, mackerel, perch, pollock
Aquatic plantsWater spinach or Ipomoea aquatica, watercress, lotus
Bivalves/molluscsClams, cockles, oysters, mussels, scallops, sea snails
Algae Seaweed (kelp, kombu or laminaria japonica, wakame)
Table 1: Blue or aquatic foods classifi cation 2


Giuliana Rocca ANutr
providing 40% of global fisheries’ catch and supporting the livelihoods of one in every 12 people.10,11 Approximately 45 million women participate in these systems, which are vital for indigenous communities where blue foods are often used in traditional medicine.12 Numerous studies focus on the need to expand production of blue foods to meet rising global population needs, but this must balance with nutritional security, cultural integrity and environmental protection.13,14 Nutritional and environmental effects of increased demand hinge on how fish replace other animal-source foods in diets.15
Risks and challenges
Over 90% of blue food production is at risk due to climate change, including ocean warming, acidification and sealevel rise.16,17 Sustainable fish stocks declined from 90% in 1974 to under 66% in 2017, and destructive practices like bottom trawling remain widespread. Future growth should prioritise sustainable aquaculture, with alternative foods such as algae or insects to reduce reliance on wild fish.7 Populations in Africa, Asia and the Indian and Pacific Oceans are particularly vulnerable to climate-driven food insecurity caused by warming ocean temperatures.16
Policy and global initiatives
The Aquatic Blue Food Coalition was established in 2021 to promote the
protection of blue foods from climate change; it aligns with the UN Sustainable Development Goals.18 Sustainable expansion can reduce micronutrient deficiencies, improve nutritional gender equity (women in many countries can benefit more than men from the high density of iron, zinc and B12 found in aquatic species) and strengthen food security.19 Improving global food systems is essential to address climate change, mitigate biodiversity loss and meet sustainability and human development goals.20
As the global population grows and consumer demand for proteinrich foods increases, there is amplified interest in novel production methods to improve the efficiency and nutritional quality of blue foods while reducing the environmental impact of their production.21 As farmed blue foods are among the fastest-growing food sectors, targeted policies – including taxes, subsidies and environmentally informed dietary guidance – can drive sustainable growth.13,22–25 To address regulatory gaps favouring industrial fleets, an Intergovernmental Panel on Blue Foods could standardise global governance, manage transboundary resources and mitigate illegal, unreported and unregulated fishing.26
Globally, three in seven people rely on the ocean as their primary protein source, yet conversations about sustainable and equitable food systems have historically focused on land-based agriculture.27,28 In Western diets, fish consumption is dominated by shrimp, tuna and salmon and represents a small proportion of weekly intake, despite the existence of over 2500 blue food species.7
Although rising consumption of low-nutrient imported foods threatens traditional diets, blue foods provide 50–90% of protein intake in coastal Pacific communities, highlighting their critical role in local food security.1 In many Global North nations, moderating ruminant meat consumption could reduce cardiovascular disease risk and greenhouse gas emissions while incorporating seafood and sea vegetables with low environmental impact.29 Consumer preferences also shape demand: freshness, safety, health and taste often outweigh sustainability
considerations, underscoring the importance of promoting blue foods as nutritious and appealing.10 Blue foods are a proven part of a healthy eating pattern, helping prevent and treat chronic illness. A rich source of micronutrients like omega-3 fats (DHA and EPA), vitamins A, D and B12 and high-quality proteins, blue foods can meet the nutritional needs of vulnerable populations, including pregnant and lactating women, children and the elderly.30
Including blue foods in the diet has positive effects on health:7
1. Reduction of micronutrient deficiencies (vitamins B12 and E, iodine, calcium, zinc, iron and selenium)31
2. 20% reduction in depression and anxiety; protection against cancer32
3. Optimal brain development, neuroprotection and brain disease prevention33
4. Improvement of cardiovascular health34
5. Reduction in the incidence of chronic diseases35–37
Sea vegetables and seaweeds
• Many cultures use sea vegetables and seaweed safely as everyday side dishes, condiments or ingredients.38
• Seaweeds are low in fat, high in fibre and rich in iron (green and red varieties provide up to 25% of daily requirements).39
• They are the only plant-based source of EPA omega-3 fatty acids (up to 220mg per 7g serving) and contain ALA fatty acids and bioactives that support cardiovascular health.40
• In Japan, where seaweed is often consumed daily, intake averages 4–7g per day in two to three small servings.41
• Due to phytochemicals that can inhibit iodine uptake and the potential bioaccumulation of heavy metals, seaweeds should be consumed one to two times per week maximum. Recommended serving sizes are 3–7g of dried or 9–21g of fresh/ rehydrated per day.41
Animal-based blue foods
• Replacing one daily serving of red meat with aquatic foods can reduce all-cause mortality by 17–25%,45 and even occasional swaps lower the risk of T2D and cardiovascular disease.
• The benefits of healthy fats and micronutrients in both animal- and plant-based blue foods generally outweigh mercury risks, which are higher in larger fish.46
• Incorporating a greater variety of blue foods supports health and environmental sustainability, as bivalves, molluscs and sea vegetables absorb nutrients, minerals and carbon dioxide while filtering water.8
Blue foods are a diverse ‘superfood’ group that offer health benefits and environmental advantages. They provide an efficient way to nourish populations while supporting aquatic ecosystems. Strengthening policies that support small-scale fisheries, mitigate climate change and expand the inclusion of diverse blue food species in diets can enhance nutrition and promote social equity. Global initiatives can improve food safety and help secure a more sustainable, resilient and ocean-orientated future for our food systems.
Interested in learning more about sea moss? Turn to Myth Busting on page 20, where Madi Myers separates traditional use, emerging nutrition science and

• Fish such as herring, mackerel and perch are more nutritious than beef, pork and chicken, with lower climate impact and higher nutritional scores.





Nutrition support in critical care is not a ‘nice to have’; it is part of organ support.1 The ICU population is highly heterogeneous. The 2018 ESPEN guidelines emphasise that the timing, route, dose and composition of nutrition must be adapted to the individual patient and the stage of critical illness.2 Critical illness creates a perfect storm for micronutrient depletion: reduced intake before admission, high metabolic stress, gastrointestinal dysfunction, renal replacement therapy, losses from drains or exudate and drugnutrient interactions.1 Losses from stoma output can be part of the picture, too. Critically ill patients need timely nutrition support that is individualised and operationally realistic, as underfeeding, overfeeding and feed interruptions (albeit avoidable) all affect recovery.1

In the NHS, the specialist dietitian’s role is to keep nutrition aligned with the phase of illness, the gut’s function and the patient’s risk profile, while working within local protocols and multidisciplinary decision-making. Specialist dietitians are key to interpreting risk and delivering practical nutrition support.1 Table 1 outlines the main ICU feeding routes, their best use and key dietetic priorities.
Micronutrients have essential antioxidant and immune functions.4 Critically ill patients are at high risk of deficiency, and low levels of micronutrients can worsen oxidative stress, immune dysfunction, collagen synthesis, wound healing, haematopoiesis and cellular metabolism. Prolonged inadequacy can compound weakness, infection risk and delay rehabilitation.5
THE SILENT DEFICIT IN ICU
Micronutrient deficiency in ICU is common, complex and often masked by inflammation, so it can be difficult to interpret.6 It is one of the quietest forms of malnutrition in critical care. It does not usually present with a single dramatic abnormality. Instead, it develops through a combination of poor intake before admission, metabolic stress, gastrointestinal dysfunction, fluid shifts, organ support and repeated interruptions to feeding.
Inflammation changes how micronutrients appear in the bloodstream. Zinc, selenium, iron and vitamins A and E may all be reduced during acute illness, even when body stores are not fully depleted.5 That is why a lab result should never be read in isolation.
Nasogastric or enteral nutrition
First-line artificial feeding when the gut is functional
Parenteral nutrition Gut inaccessible; enteral nutrition contraindicated or persistently inadequate
Start early; advance steadily; reduce interruptions; consider post-pyloric access if gastric feeding fails1
Avoid overfeeding; account for non-feed calories; monitor line and metabolic complications1
More useful questions are: Does the patient have a credible risk of deficiency? Has intake been poor for several days? Are there GI losses, wounds, post-surgery healing, burns or in continuous renal replacement therapy (CRRT) required? Is feeding consistently interrupted? Is parenteral nutrition complete and uninterrupted?
These questions matter more than a single value taken during sepsis or multiorgan failure.
In ICU practice, several micronutrients are especially relevant.5,7 A 2025 review concluded that higher needs are common in critical illness, but high-dose monotherapy is not recommended. Instead, basal daily needs should be met and proven deficiencies corrected.
Vitamin D interpretation is complicated by inflammation and the patient’s baseline status. Vitamin D is the most common example of interpretive uncertainty. A low level of 25-hydroxyvitamin D in the blood is common in ICU patients, but levels can fall with inflammation, so a single low result should not automatically trigger a one-size-fits-all mega-dose strategy.
Zinc and selenium are particularly relevant during prolonged ICU stays. This is due to immune function, wound healing and the role of antioxidants. Circulating levels also fall with inflammation. These nutrients are important but measuring them does not solve the interpretive problem.
Refeeding risk remains one of the most important triggers for thiamine vigilance, as the clinical stakes are immediate. Thiamine should be considered early in patients with prolonged poor intake, significant weight loss or alcohol misuse. Thiamine is a low-risk, high-value intervention that can prevent serious metabolic complications when feeding is restarted or advanced, as carbohydrate reintroduction without thiamine replacement can create preventable metabolic harm.
In practice, thiamine is the nutrient most urgently associated with this risk. However, it sits alongside phosphate, magnesium and potassium in the wider metabolic picture. This is why micronutrient support should be built into refeeding plans from the start, not added later as an afterthought.
Iron, vitamin C and magnesium also enter the discussion in patients with anaemia, poor wound healing or high metabolic stress (eg burns). The key point is to identify the patients most likely to benefit from targeted replacement and to ensure routine daily provision is not missed.
Parenteral nutrition is often the route where micronutrient planning becomes most visible. Dietitians should check that vitamin and trace-element provision is not inadvertently omitted during shortages, line issues, bag changes or transitions between compounded
Table 2: Micronutrient management in critical care1,5-7
MicronutrientWhy it matters in ICU
Vitamin D Immune and musculoskeletal function; low levels are common in ICU
Zinc Wound healing, immune support taste and protein synthesis
Selenium Antioxidant defence and thyroidrelated pathways
Thiamine Carbohydrate metabolism and refeeding risk
Magnesium Wound healing, cardiovascular stability, immune system regulation and inflammatory response
Practical dietitian focus
parenteral nutrition and commercially prepared formulations.
The same principle applies to longstay ICU patients on enteral feeding who receive large feed interruptions. If feed delivery falls well below target, micronutrient intake also drops and the hidden deficiency may be underrecognised until the patient develops poor wound healing, weakness, anaemia, skin changes or prolonged inflammatory recovery. Table 2 shows key micronutrients in ICU together with dietetic priorities. The list is not exhaustive and many other micronutrients work in conjunction and collaborate at a cellular level. More research in the amounts of individual micronutrients and suitable combinations is required.
Dietitians in ICU need to read micronutrient data like a clinical story, not a single laboratory number.6 A low result is most useful when it fits the context of poor intake, malabsorption, prolonged ventilation, CRRT, significant gastrointestinal losses, severe burns or a prolonged inability to meet requirements enterally.
If the patient is septic, heavily inflamed or in early multi-organ failure, a low serum concentration may be partly due to redistribution. In this situation, the safest approach is usually to ensure routine multivitamin and trace-element provision, address obvious risk factors and reserve targeted repletion for patients with strong clinical or biochemical evidence of deficiency.
Interpret with inflammation; replace if deficient/high risk
Consider losses, prolonged critical illness and enteral adequacy
Watch for low intake, long ICU stays and possible CRRT losses
Prioritise in malnutrition, alcohol use, sepsis and refeeding risk
Interpret in conjunction with clinical presentation and supplement appropriately
Iron Oxygen transport and erythropoiesisInterpret cautiously with ferritin/C-reactive protein and inflammation
The most defensible position in 2026 is selective supplementation, not indiscriminate mega dosing.5 Recent reviews and guideline summaries argue for meeting daily requirements, correcting documented deficiencies and using higher doses only when there is a credible reason such as a proven deficit, known increased losses or a recognised high-risk state.
This approach is supported by observational ICU data showing that additional micronutrient administration does not necessarily normalise blood levels quickly, especially when inflammation is still active. That does not mean supplementation is ineffective; it means the biology is messy. The dose, route, duration, baseline inflammation and patient subgroup all count, and the literature still lacks a universally effective ‘ICU micronutrient cocktail’.
Routine broad micronutrient testing for every ICU patient is rarely feasible or useful, but selected testing can be justified in prolonged ICU stays, repeated feed failure, unexplained anaemia, difficult wound healing, high-output losses, CRRT or suspected deficiency states.5
When interpreting results, always ask three questions:
1. Is the patient inflamed?
2. Are there obvious losses or inadequate intake?
3. Would the result change management today?
If the answer to the last question is no, then the most valuable intervention may be to ensure complete multivitamin and trace-element support, rather than chasing borderline numbers.
Specialist ICU dietitians are often the clinicians best placed to spot cumulative nutritional deficits.6 We see the feed interruptions, the delays, the transitions from enteral to oral intake and the patients whose nutrition looks adequate on paper but not in reality.
That makes our role central. We translate physiology into a practical prescription, ensure supplements are used where they matter and help the MDT avoid both neglect and overreaction. In ICU, that balance is essential. The specialist ICU dietitian is central to making this work at the bedside. The BDA critical care guidance highlights that patients remaining in ICU beyond 48 hours require tailored support from a specialist dietitian, and that feeding protocols alone are not enough to prevent nutritional deficits.1 That is why ICU micronutrient care should be framed as part of the nutrition prescription, not as a separate afterthought.
The best practice is collaborative: accurate route choice; full daily provision when feeding is established; targeted correction of high-risk deficiencies; and regular review as inflammation settles and the patient’s phase of illness changes.
• Low serum levels in ICU do not always mean true deficiency; inflammation can distort the picture.
• Micronutrient care should be proactive, not reactive.
• The safest strategy is often to ensure complete daily provision, then target repletion to patients at genuine risk.
• Thiamine is one of the most important low-risk interventions in refeeding prevention.
Micronutrient deficiency in ICU is common, clinically relevant and easy to misread. The best approach is cautious, contextual and consistent: identify risk early, choose the right route, ensure complete daily provision and supplement selectively where there is a clear reason. The key task is to translate imperfect laboratory data into safe, proportionate supplementation decisions that support recovery without drifting into blind over-repletion.
Dietary choices are shaped by a complex interplay of cultural, social, environmental and economic factors rather than individual preference alone. Culture plays a central role, influencing food habits through traditions, beliefs, identity and social connections, while factors such as family, religion, cost and food environments further shape what people eat.1
Social perception and cultural expectations strongly influence what we eat and can restrict personal choice. Because food is closely linked to identity, social norms and how we believe others perceive us, our eating habits are often shaped as much by external pressures as by our own preferences.2
This is supported by research on food taboos, which are dietary restrictions that are not arbitrary, but rather often rooted in practical needs and cultural traditions.3 Many taboos develop to protect health, such as avoiding foods that may be unsafe or more likely to cause illness, while others help conserve important resources. They can also stem from religious or cultural beliefs, reinforcing a sense of identity and belonging. In some cases, these rules serve to protect specific groups, such as pregnant women, or guide behaviour within society. Overall, food taboos are shaped by a combination of health, environmental and cultural factors, even if their original purpose is not always recognised today.
Social class and status further influence food choices. Research shows that individuals who associate with power and dominance tend to prefer larger portions and hearty foods that signal strength and abundance. In contrast, those motivated by prestige and social respect are more likely to choose smaller portions, healthier options and foods perceived as refined or sophisticated. This highlights that food preferences are not driven solely
by hunger or taste, but also by how individuals wish to present themselves, using food as a way to express status and identity.4
Traditional foods are shaped by local ingredients, climate and cultural practices, and they often carry symbolic and social significance within communities. They reflect historical, cultural and nutritional traditions, with preparation and processing methods passed down through generations, which influence their safety, quality and nutritional value.5
Beyond providing sustenance, traditional foods play a vital role in maintaining cultural identity and preserving heritage.
More broadly, foods in general are influenced by culture, history and society, which affect not only what we eat but also how and when we eat. Cultural factors such as religion, family traditions and local

Fareeha Jay

customs guide our food choices, while food itself reflects identity, values and social status.6 Although modernisation and globalisation are changing traditional diets, food continues to carry deep social and cultural meaning. This is seen around the world: Japanese cuisine traditionally centres on rice-based meals; maize and beans are staples in the Mexican diet; Brazilians consume high amounts of meat; Indians rely heavily on plant-based dishes; and traditional Turkish cuisine is known for its abundance of dairy-based foods.1
Many religions, such as Islam, Hinduism, Judaism and Christianity, prescribe specific dietary rules like fasting, abstaining from certain foods or following plant-based diets, which can influence both physical and mental health. Research shows that these practices are
often linked to positive health outcomes, including better weight management, reduced risk of chronic diseases and improved mental clarity or self-discipline.
A study shows that beyond physical effects, religious diets also provide psychological benefits by fostering a sense of spiritual connection, self-control and community belonging.7 The study underscores that dietary practices rooted in religion have multidimensional effects, shaping not just nutrition but also emotional and social well-being.
Dietary choices are also influenced by geography. For instance, warmer Mediterranean regions tend to support diets rich in fruits, vegetables and olive oil, while coastal areas often rely more heavily on seafood. Geography also drives migration, which in turn reshapes food cultures around the world. A clear example is South Asian migration to Western countries such as the UK, where migrants have introduced spices, cooking techniques and dishes like curry
and biryani. Over time, these have been adapted to local tastes, resulting in popular fusion dishes such as chicken tikka masala. Consequently, South Asian cuisine has become an integral part of British culture, demonstrating how geography and migration together shape dietary patterns and food environments.1 Additionally, research shows that where adolescents live significantly influences their health behaviours and outcomes. Adolescents in rural areas are more likely to consume energy-dense, nutrient-poor foods and fewer fruits and vegetables, whereas those in urban areas generally have better access to a wider variety of foods, even if their diets are not always ideal. Overall, this highlights that health behaviours are not solely based on individual choice but are strongly shaped by geographic and environmental factors.8
Socioeconomic status strongly influences dietary patterns, with individuals from lower socioeconomic
backgrounds more likely to experience poorer diets and higher rates of dietrelated diseases. This is largely due to differences in food environments, where disadvantaged areas often have limited access to affordable, healthy food and fewer food outlets. These challenges are even more pronounced in rural regions, where food costs are higher and accessibility is lower. Overall, socioeconomic status plays a key role in shaping diet and health outcomes, highlighting the link between economic inequality and nutrition.1
Ultimately, dietary habits represent a complex interplay of cultural, social, and economic forces rather than just individual preference. Addressing food choices requires recognising these deep-rooted environmental and socioeconomic factors, highlighting the need for systemic changes to improve nutrition.


For children with cerebral palsy (CP), progress is fuelled by care and the right nutritional support
The best ONS range is one that offers choice1
Fortini has the widest ONS range of flavours, textures and formats to support complex feeding needs2




