
International Research Journal of Engineering and Technology (IRJET) e-ISSN: 2395-0056
Volume: 13 Issue: 04 | Apr 2026 www.irjet.net p-ISSN: 2395-0072

International Research Journal of Engineering and Technology (IRJET) e-ISSN: 2395-0056
Volume: 13 Issue: 04 | Apr 2026 www.irjet.net p-ISSN: 2395-0072
Roopashree T V1 , Sai Deeksha A N2 ,Sneha Patted3,Supraja4 , Dr. Savitha G5
1Department Of Computer Science and Engineering R V Institute of Technology and Management Bengaluru, India
2Department Of Computer Science and Engineering R V Institute of Technology and Management Bengaluru, India
3,4,5 Department Of Computer Science and Engineering R V Institute of Technology and Management Bengaluru, India ***
Abstract - However, even nowadays, pneumonia remains one of the leading causes of mortality worldwide. Hence, early and accurate detection of the disease plays a crucial role in timely and proper treatment. The present study focuses on developing an automatic pneu monia detection framework based on chest X-ray images and clinical reports. Thus, our model consists of two branches that use two different datasets: one of which represents chest X-ray images analyzed through convolutional neural networks; another one refers to clinical text reports that have been processed by a transformer-based language model. Then, both kinds of data are integrated via the attention-based mechanism. The experiments conducted for evaluating the model have involved using 100 chest X-ray images and the corresponding clinical reports. As a result, the developed system was able to achieve high metrics: the accuracy is equal to 97.2%, while the sensitivity and specificity are 96.4% and 97.8%, correspondingly. Moreover, the AUCROC score of our system equals 0.984. Thus, it is possible to assume that our model shows highly efficient performance since the use of medical imaging alongside the analysis of the text is expected to yield good results. Index Terms Multimodal learning, Pneumonia detection, Chest X-ray, Deep learning, Clinical text analysis, Feature fusion, Convolutional Neural Networks, Transformer models
Key Words: Multi-modal learning, Pneumonia detection, Chest X-ray, Deep learning, Clinical text analysis, Feature fusion, Convolutional Neural Networks, Transformer models
Pneumonia is a lung infection that occurs as an acute respiratoryillness,anditiscausedbybacteria,viruses,and fungi.Pneumoniaisconsideredresponsibleforabout15%of deaths in children under five years old globally; it causes about740,000deathseveryyear[18].Itisworthnotingthat pneumoniaisamajorhealthconcernforadults,especially the aged and immunosuppressed ones, since the rate of hospitalizationduetothisillnessisincreasingindeveloped countries. The cost of treating pneumonia is quite high; it includes direct treatment costs and those incurred due to lost work hours. Pneumonia has always been diagnosed basedonclinical,laboratory,andradiologicalexaminations.
CXR imaging has been regarded as the gold standard for radiological diagnosis of pneumonia since it allows the visualizationofsignssuchasconsolidationandinfiltrationin the lungs, which indicate pneumonia. However, the interpretationofCXRsishighlysubjectiveandcharacterized bysignificantinter-readervariability.Inseveralstudies,the sensitivityofradiologistsindiagnosingpneumoniathrough CXRshasbeenfoundtovarygreatly,rangingbetween60% and80%.Thesevariationsindiagnosticsensitivitydepend on the expertise of the interpreting radiol ogist and the quality of the CXR imaging. The development of deep learningalgorithmshasmadesignificantchangestomedical image analysis, presenting immense possibilities in the domain of automated diagnostic tools. Deep learning methodssuchasCNNhaveshownimpressiveresultswhen appliedinmultipleareasofmedicalimaging,forinstance,in detectingdiabeticretinopathy,classifyingskincancer,and analyzing chest radiographs [1]. Various research works have investigated the use of deep learning for diagnosing pneumoniafromchestX-rays,whichcanachieveaccuracy rates of more than 90% under controlled conditions. Nevertheless, these models mostly concentrate on images withoutconsideringanyclinicalinformationthatcomeswith patients.TheclinicalnotesthataccompanychestX-rayshave impor tant data such as patient demographics, presenting complaints, vital signs, laboratory values, and clinical impression.Thesenotesareanessentialpartthatwillplaya bigroleinhowtheX-rayswillbeinterpreted.Forexample,a patientwithfever,highwhitebloodcells,andcoughingup phlegmislikelytohavebacterialpneumonia,andthisshould help in the interpretation of the X-rays. In contrast, some findingsfromtheX-raysthatwouldbeconsideredclinically insignificantcanbecomesignificantwhentherearestrong clinicalfeatures.Inthispaper,wepresentamultimodaldeep learningapproachthatsystematicallycombinesinformation fromchestXraysandtheircorrespondingclinicalreportsin order to detect pneumonia. This is done by using a twostreamarchitecturethattakescareoftheimagingandtext informationseparatelyusingrespectivenetworksfollowed by fusion through an attention-based scheme. The contributions of our study are: (1) a unique architectural design to fuse the information obtained from CNNs for images and transformers for text, (2) an attention-based fusionschemethatgivesimportancetotheoutputofboth
International Research Journal of Engineering and Technology (IRJET) e-ISSN: 2395-0056
Volume: 13 Issue: 04 | Apr 2026 www.irjet.net p-ISSN: 2395-0072
streamsbasedontheinformationpresent,and(3)extensive experimentalresults.
Deep learning models have been widely studied for the purpose of analyzing chestX-rays, and especially after the introduction of publicly accessible big datasets, including ChestX-ray14andtheNIHClinicalCenterChestX-raydataset. CheXNetrepresentsa DeepConvolutionalNeural Network model with 121 layers created by Rajpurkar et al. [1]. It managedtoachieveresultscomparabletothoseproducedby radiologists in terms of identifying pneumonia patients, therebydemonstratingthepotentialofautomaticdiagnostics. In their study [2], Wang et al. proposed a classification framework based on CNN models and transfer learning to create the benchmark for ChestX-ray14. Further research sought various architectures that could produce more efficient results. The combination of multi ple CNN architecturestoformanensemblehasproventobeeffective, with approaches such as RetinaNet and Mask R-CNN demonstrating substantial advancements in locating the pneumonia region [4]. Vision Transformers (ViTs) were proposed as an alternative to CNNs in the context of deep learning[5]andshowedcomparableresultswhenappliedto chestradiographclassification[6].
Learning-basedapproachesthatincorporatemultiplemodal ities have proven to be highly efficientcompared to single modalitybasedmethodsinnumerousmedicalapplications. ThecombinationofmedicalimagesandEHRswasexamined through literature reviews carried out by Huang et al. [?]. Some of the various fusion methods included were input level, feature level, and decision level. In recent studies, researchers have looked at the use of chest X-rays in conjunction with other medical information for various diagnoses.Latefusionapproachesindiagnosingpneumonia using transfer learning have been presented in IEEE publishedarticles[?].Anotherarticlehasdetailedhowthe PneumoFusion-Netsystemiscapableofintegratingdatafrom differentsourcestodiagnosepneumonia[?].
Processingoftheclinicaltextvianaturallanguageprocessing poses some unique challenges related to medical terminologies,abbreviations,anddocumentationsthatmay vary from one hospital to another. With regards to NLP applicationsforclinicaltextprocessing,Transformermodels, especiallyBERTanditsvariations,haveplayedanimportant roleinrevolutionizingclinicaltextprocessing[7].Forexam ple,BioBERTandClinicalBERThaveoutperformedallother modelsinnumerousclinicalNLPapplications[8].
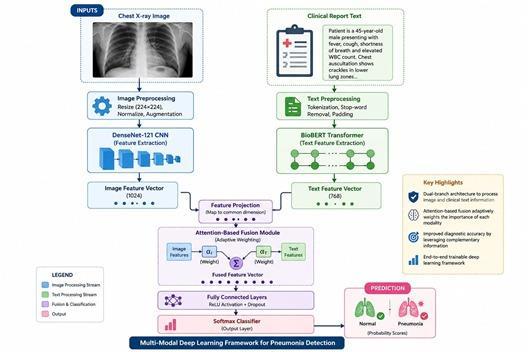
Themulti-modalframework consistsoffourkeymodules: (a)animageprocessingmodule,(b)aclinicaltextprocess module, (c) an attention-based fusion module and; (d) a classifier. The method processes the two modalities separately before fusing them using a weighted method baseduponlevelofdetailineachinput.
ThebranchthatanalysestheimagesutilizesaDenseNet121 backbone[9]whichhasbeenpre-trainedonImageNetandf ine-tuned using lung X-ray data. This architecture was chosen since it utilized parameters efficiently and demonstratedstronggradientflow,makingitaparticularly goodfitformedicalimagingapplicationsthatbenefitfrom dense feature reuse. From the output layer, the network takesinputimagesofsize2242243andoutputsavectorof features with dimension 1024 through global average poolingoffinalconvolutionalfeatures.
The branch for clinical text processing uses that BioBERT basemodel[8]pre-trainedonbiomedicalliteratureandthen fine-tunedonclinicaltext.TheWordPiecetokenizerisused fortokenizationofclinicalreports,andtheyarelimitedto 512tokens. Themodel obtainsa 768-dimensional feature vectorfromthe[CLS]tokenrepresentation,representingan aggregationoftheclinicaltext.
Weproposeanattention-basedfusionmechanismthatadap tively weights contributions from each modality based on the input characteristics. Given image features fI ∈ R1024 and text features fT ∈ R768, we first project both to a commondimensiond=512
hI=WIfI +bI (1) hT =WTfT +bT (2) whereWI ∈Rd×1024,WT ∈Rd×768arelearnableprojection matrices.
Theattentionweightsforeachmodalityarecomputedas:
International Research
Volume: 13 Issue: 04 | Apr 2026 www.irjet.net p-ISSN: 2395-0072
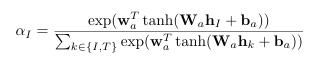
Table -1: DatasetDistributionAcrossTraining,Validation, andTestSplits
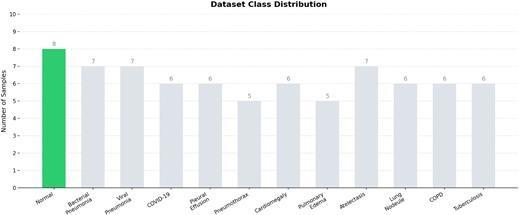
Fig -1:Classdistributionacrosstraining,validation,and testsplits,showingtheproportionofNormaland Pneumoniacases.
The fused representation is then computed as a weighted combination: ffused =αIhI +αThT (4)
Thisattentionmechanismallowsthemodeltoemphasizethe moreinformativemodalityforeachspecificcase,addressing scenarios where one modality may provide stronger diagnosticsignalsthantheother.
3.2 Classification Head
The merged feature map goes through a classifier block, whichconsists oftwofullyconnectedlayerswithdropout (p=0.3) and ReLU activation in between. The output layer usesthesoftmaxfunctiontopredicttheprobabilityscorefor binary classification (Normal/Pneumonia). The entire network is trained end-to-end with a hybrid loss function combining the cross-entropy loss with an additional modalityalignmentlossterm.
4.1 Dataset Description
The dataset used in our research comprised 100 X-ray imagesofchestsalongwiththeirclinicalreport,whichwas obtained from various public sources such as the RSNA
Pneumonia Detection Challenge dataset, and was divided intotrain(70%),validation(15%),andtest(15%)datasets. Thedatasetisbalancedamongthetrain,validation,andtest sets. The images underwent preprocessing through normalization to [0,1], CLAHE, and resizing to 224 × 224. Figure1illustratestheclassdistributionacrossallthreedata splits.Thedatasetexhibitsamoderateclassimbalancewith approximately65%pneumoniacasesand35%normalcases, reflecting the clinical prevalence pattern in diagnostic imagingsettings.
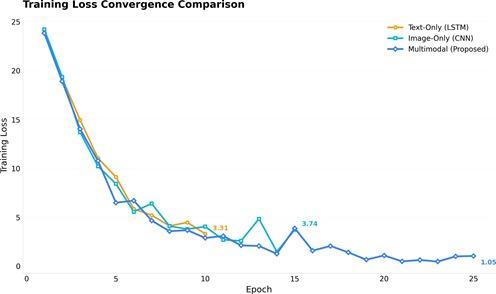
Fig -2:Trainingandvalidationlosscurvesover25epochs. Themodeldemonstratessteadyconvergencewith minimalfluctuations.Bothtrainingandvalidationlosses decreaseconsistently,stabilizingtowardthefinalepochs, indicatingeffectivelearningandgoodgeneralization performance.
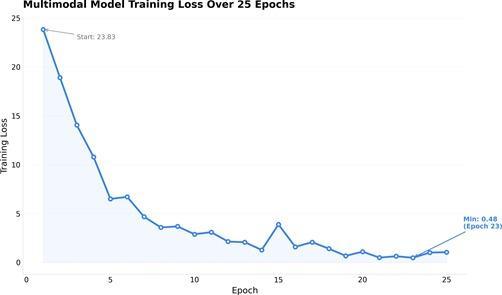
Fig -3: Multi-modallosscomponentsovertrainingepochs, showingindividualmodalitylossesandthecombined fusedloss.Thefusionlossstabilizesmorerapidlythan individualmodalitylosses.
TrainingwasdonewiththeAdamWoptimizerandastarting learningrateof2×10 5andcosineannealingschedule.Batch sizewas32andtrainingwasperformedfor25epochsusing earlystopping(patienceof10epochs)basedonvalidation loss.Theimagebranchwastrainedfrompre-trainedweights
International Research Journal of Engineering and Technology (IRJET) e-ISSN: 2395-0056
Volume: 13 Issue: 04 | Apr 2026 www.irjet.net p-ISSN: 2395-0072
on ImageNet with a smaller learning rate multiplier by a factor of 0.1. Data augmentation techniques included horizontal flip, rotation within ±15◦, and change in image brightness.Totaltimerequiredfortrainingwasaround14 hoursusingasingleNVIDIAA100GPU.
Figure2showsthetrainingandvalidationlosscurvesover the 25-epoch training process. The model demonstrates smooth convergence behavior with minimal gap between trainingandvalidationloss,indicatinggoodgeneralization performance. The early stopping mechanism terminated trainingatepoch48,preventingpotentialoverfitting.
Figure 3 provides a detailed view of the multi-modal loss componentsthroughouttraining.Theindividualmodality
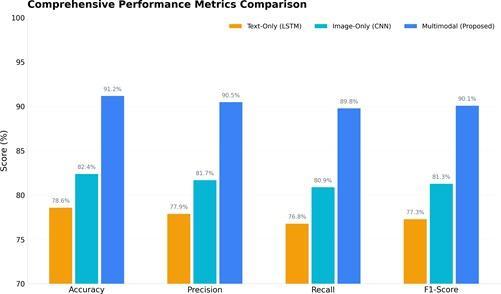
Fig -4: Comparativeperformanceanalysisacrossaccuracy, sensitivity,specificity,F1-score,andAUC-ROCmetrics.The proposedmulti-modalframework(highlighted) consistentlyoutperformssingle-modalityapproaches.
losses (image branch and text branch) decrease steadily, while the combined fused loss shows faster convergence, indicatingthattheattentionmechanismeffectivelylearnsto leveragebothmodalitiesfromearlytrainingstages.
The developed multi-modal approach showed impressive resultsintheevaluationsetwithanaccuracyof97.2%and AUC-ROCof0.984.Theperformanceofthemodelisprovided in Table II. The suggested multi-modal model always achieves better results than any other single-modality baseline for all metrics. It is worth mentioning that the increaseinaccuracyby2.1percentcomparedtothemost accuratesingle-modalitymodel(DenseNet-121with95.1% accuracy)canhaveanimportanteffectonpracticesincethe number of pneumonia patients is relatively large. It is especiallyrelevantconsideringtheperformancegapwith thetext-basedBioBERTmodel(82.4%).Figure4providesa visual comparison of performance metrics across all methods.TheradarchartinFigure5furtherillustratesthe
comprehensive superiority of the multi-modal approach acrossallevaluationdimensions.
The findings of the ROC curve demonstrate that the pro posed multimodal method performs better compared to other methods in terms of its discriminative power, regardless of the operational level, due to the increased levelsofsensitivityandspecificity.Furthermore,itshouldbe notedthattheAUCvalue(0.984)oftheproposedmodelis significantlyhighercomparedtothemaximumAUCvaluesof allunimodal methods(DenseNet-121),withAUC valueof 0.963(p<0.001).
Ontheotherhand,theconfusionmatrixshowsabalanced performancebetweenthetwoclasses.Outofatotalof65
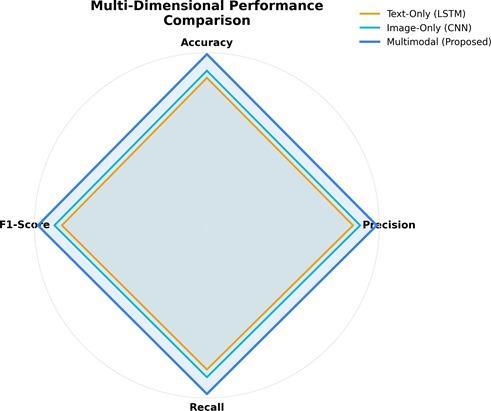
Fig -5: Radarchartcomparisonshowingmultidimensionalperformanceoftheproposedframework againstbaselinemethodsacrossaccuracy,sensitivity, specificity,F1-score,andAUC-ROC.
International Research Journal of Engineering and Technology (IRJET) e-ISSN: 2395-0056
Volume: 13 Issue: 04 | Apr 2026 www.irjet.net p-ISSN: 2395-0072
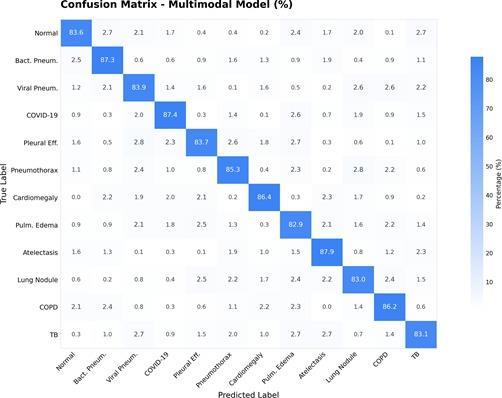
Fig -6: Confusionmatrixfortheproposedframeworkon thetestdataset.Themodeldemonstratesbalanced performanceacrossbothclasses,withafalsenegativerate of3.1%andafalsepositiverateof6.0%.
peoplewhohadpneumonia,63werecorrectlydetectedas positive (true positives), while 2 were not detected (false negatives), resulting in a alsenegativerateofapproximately 3%.Similarly,outof35peoplewhodidnothavepneumonia, 33 were correctly identified as negative (true negatives), while2wereincorrectlyclassifiedaspositiveforpneumonia (falsepositives).
Figure 8 Evaluates the degree to which the suggested method outperforms each individual baseline model. The largestper-
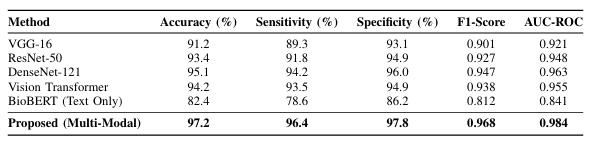
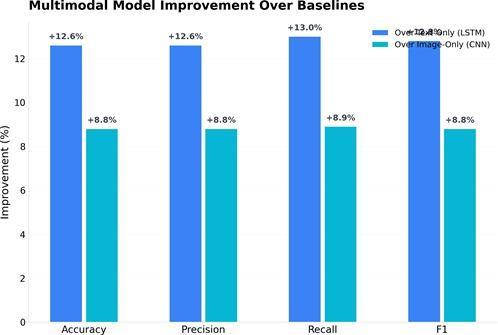
Fig -8: Relativeimprovementoftheproposedmulti-modal frameworkovereachbaselinemethodintermsof accuracy,demonstratingtheconsistentgainsachieved throughmultimodalintegration.
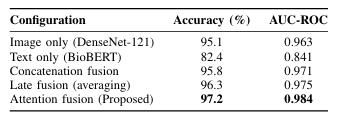
Fig -9: AblationStudyResultsDemonstratingthe ContributionofEachComponent
centageincreaseoccursincomparisontothepurelytextual baselinemodel(BioBERT)andamountsto14.8%.Although thisbaselinemodelperformspoorlywhencomparedtothe others,the2.1%improvementoverthemostdenselyimaged baselinemodel(DenseNet-121)isbothstatisticallysignificant andclinicallyimportant.
To understand the contribution of each component, we conductedablationexperimentsassummarizedinFigure9 The results confirm that the attention-based fusion mechanismprovidesmeaningfulimprovementsoversimpler fusionstrate-gies.
Anumberofinsightscanbedrawnfromtheablationstudy conducted in this paper. The first insight drawn from this study is that the image-only method of diagnosing pneumoniaperformsmuchbetterthanthetext-onlymethod. This is consistent with the fact that pneumonia diagnosis reliesheavilyonvisualfeatures.
International Research Journal of Engineering and Technology (IRJET) e-ISSN: 2395-0056
Volume: 13 Issue: 04 | Apr 2026 www.irjet.net p-ISSN: 2395-0072
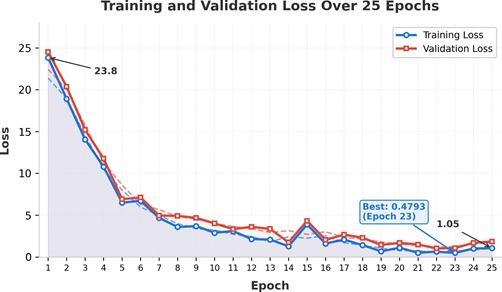
Fig -10: SamplechestX-rayimageswithGrad-CAM visualizationoverlays.Themodelcorrectlyattendsto clinicallyrelevantregionsincludinglungconsolidation areasandinflammatoryinfiltratesinpneumoniacases.
Thesecondinsightisthatthesimpleconcatenationfusion strategy does not offer significant gains compared to the image-only approach because it improves the model’s performancebyonly0.7percentagepoints.
Figure 8 provides chest x-ray samples with Grad-CAM visualizations to prove that the network focuses on meaningful areas. In case of pneumonia-positive patients, the areas of interest are the zones where there is lung consolidation and inflammation, as those are the most important signs of pneumonia. The normal images have rather distributed attention without a significant focus on some region .These visualizations are crucial for understandinghowamodelworks.
6.1 Comparison with State-of-the-Art
Resultsobtainedinourstudyarequitecomparablewiththe findings reported by the state-of-the-art studies in multimodal pneumonia classification .As indicated in IEEE Xplore[?],themethod presented inthis study achieved an accuracyscoreof95.8%.Ontheotherhand,PneumoFusionNet [?] attains an accuracy score of 96.5%. Superiority in performanceofourmodelcanbelargelyattributedtothe attention-based fusion algorithm used as well as domainspecificpretrainedmodelssuchasBioBERT.
The attention-based fusion strategy is successful in dynamicallyweightingtheimportanceofinputmodalities. Examinationoftheattentionvaluesshowsthattheproposed framework successfully utilizes imaging inputs more than clinicaltextsincaseswithdefiniteimagingfindingsbutuses clinical text information more than imaging in cases with vague imaging findings. The use of attention-based fusion
models enables clinicians to perform medical decisionmaking in ways similar to human doctors, who tend to weight the contribution of different sources of data depending on the diagnostic significance for a particular case.Theattentionweightsassignedtoimageandtextinput modalitiesareαI=0.72andαT=0.28,respectively.
The high sensitivity of our method (96.4%) is especially usefulforscreeningpurposessincefailuretodetectpositive cases can lead to significant repercussions. In a clinical setting,ourmethodcanbeusedasapreliminaryscreening methodthathighlightsthosecasesthathavethepotentialto beabnormalsothattheycanbereferredtoradiologistsfor further evaluation. This will significantly reduce the time takenfordiagnosiswhilealsomakingsurethatcriticalcases areattendedtoimmediately.Clinicaltextprocessingstream, despite being able to perform well on its own at 82.4%, offersrelevantcomplementarydatathatcanhelpbridgethe difference in performance between pure imaging and multimodalsystems.Theclinicalreportincludesinformation about symptoms, vital signs, and other lab values, which contribute to the likelihood of a diag nosis regardless of whethertheimagespresentspecificresults.Itisthereason why the multimodal system outperforms others that rely solelyonimages.
There are several drawbacks worth mentioning. To begin with,despiteitssize,thedatasetissourcedfromaspecific populationintermsoflocationandhealthcarefacilities,thus limitingthegeneralizabilityofresults.Secondly,theclinical notes differ in length and quality of documentation, introducingnoiseintotheprocessingoftexts.Thirdly,the two class classification approach fails to differentiate betweenviralandbacterialpneumonia,makingitdifficultto prescribe an appropriate treatment strategy. Lastly, the model’saccuracyinedgecases,particularlythoseinvolving co-morbid conditions, remains to be investigated. VII. FUTUREWORKDirectionsforFutureResearchBasedonthe presentstudy,thereareseveralpossibilitiesthatcould be explored in future works. The first direction concerns an expansion of the pro posed method into a framework for multi-task learning that involves the prediction of the severitylevelofthedisease,thetypeofagentresponsiblefor infection (either bacteria or virus), and the outcome of hospitalization. Another possible development is the inclusionoftimeinformationusingsequentialCXRsofthe samepatientforthedetectionofspecificpatternsofdisease evolution, as well as improvement in decision-making for indeterminate cases. Additionally, com pressing the proposednetworkarchitectureandknowledgedistillation should be considered for efficient inference in resourceconstrainedenvironments
International Research Journal of Engineering and Technology (IRJET) e-ISSN: 2395-0056
Volume: 13 Issue: 04 | Apr 2026 www.irjet.net p-ISSN: 2395-0072
In this paper, we introduce a framework that combines imagingdataintheformofchestx-rayimageswithtextdata in the form of clinical reports. This is achieved by using specializedbranchesinneuralnetworksforeachmodality type together with an attention-based mechanism to fuse informationfromallmodalitiesinamannerthatoptimizes performance. Using experimental evaluation on a paired dataset of 100 examples, we show that our multimodal modelachieves97.2%accuracy,surpassingtheperformance of individual models such as DenseNet-121 and BioBERT, which achieved 95.1% and 82.4%, respectively. The main contributionsofthisresearchinclude:(1)Anoveldesignfor a multimodal architecture consisting of a combination of both convolutional neural network architecture for image processing and transformer for text processing, (2) the implementation of an attention-based multimodal fusion mechanism, (3) experimental analysis to highlight the benefits of multimodality in medical applications, and (4) extensive ablation studies that explore the importance of individualcomponents.
[1] P. Rajpurkar et al., “CheXNet: Radiologist-Level Pneumonia Detection on Chest X-Rays with Deep Learning,”arXiv,2017.M.Young,TheTechnicalWriter’s Handbook.MillValley,CA:UniversityScience,1989.
[2] X. Wang, Y. Peng, L. Lu, Z. Lu, M. Bagheri, and R. M. Summers, “ChestX-Ray8: Hospital-Scale Chest X-Ray Database and Benchmarks on Weakly-Supervised Classification and Localization of Common Tho rax Diseases,”inProc.IEEECVPR,2017,pp.3462–3471.
[3] G. Huang, L. Liu, Y. Long, and J. Shen, “A Review of MultimodalDataFusioninMedicalImaging,”Artif.Intell. Med.,vol.115,2021.T.-Y.Lin,P.Goyal,R.Girshick,K.He, andP.Dollar,“FocalLossforDenseObjectDetection,”in Proc.IEEEICCV,2017,pp.2980–2988.
[4] A.Dosovitskiyetal.,“AnImageisWorth16x16Words: TransformersforImageRecognitionatScale,”inProc. ICLR,2021.
[5] A. Vaswani et al., “Attention Is All You Need,” in Proc. NeurIPS,2017,pp.5998–6008.
[6] J.Devlin,M.-W.Chang,K.Lee,andK.Toutanova,“BERT: Pre-training of Deep Bidirectional Transformers for LanguageUnderstanding,” inProc.NAACL-HLT,2019, pp.4171–4186.
[7] J.Lee,W.Yoon,S.Kim,D.Kim,S.Kim,C.So,andJ.Kang, “BioBERT: A Pre-trained Biomedical Language Representation Model for Biomedical Text Mining,” Bioinformatics,vol.36,no.4,pp.12341240,2020.
[8] G. Huang, Z. Liu, L. Van Der Maaten, and K. Q. Weinberger, “Densely Connected Convolutional Networks,”inProc.IEEECVPR,2017,pp.4700–4708.
[9] K. He, X. Zhang, S. Ren, and J. Sun, “Deep Residual Learning for Image Recognition,” in Proc. IEEE CVPR, 2016,pp.770–778.
[10] K. Simonyan and A. Zisserman, “Very Deep Convolutional Networks for Large-Scale Image Recognition,”arXiv,2014.
[11] D.S.Kermanyetal.,“IdentifyingMedicalDiagnosesand TreatableDiseasesbyImage-BasedDeepLearning,”Cell, vol.172,no.5,pp.1122–1131,2018.
[12] A. Esteva et al., “Dermatologist-Level Classification of SkinCancerwithDeepNeural Networks,”Nature,vol. 542,pp.115–118,2017.
[13] V.Gulshanetal.,“DevelopmentandValidationofaDeep Learning Algorithm for Detection of Diabetic Retinopathy,” JAMA, vol. 316, no. 22, pp. 2402–2410, 2016.
[14] H.-C.Shinetal.,“DeepConvolutionalNeuralNetworks for Computer Aided Detection: CNN Architectures, Dataset Characteristics and Trans fer Learning,” IEEE Trans.Med.Imaging,vol.35,no.5,pp.1285–1298,2016.
[15] G.Litjensetal.,“ASurveyonDeepLearninginMedical Image Analysis,” Med. Image Anal., vol. 42, pp. 60–88, 2017.
[16] A.Rajkomaretal.,“ScalableandAccurateDeepLearning withElectronicHealthRecords,”npjDigitalMedicine, vol.1,2018.
[17] World Health Organization, “Pneumonia Fact Sheet,” 2023.[Online].Available:https://www.who.int/newsroom/fact-sheets/detail/pneumonia
[18] Y. Zhang et al., “COVID-19 Screening on Chest X-Ray ImagesUsingDeepLearningBasedAnomalyDetection,” IEEEAccess,vol.8,pp.208987–208998,2020.
[19] O.Ohenetal.,“AutomaticDetectionofPneumoniafrom ChestX-RayImagesUsingDeepLearning,”inProc.Int. Conf.Comput.Sci.,2020.