


The IMF InfoLine team is here to support you and your loved ones with the most up-to-date information about myeloma
Call the IMF InfoLine at 1.800.452.CURE (toll-free in the U.S. & Canada) or 1.818.487.7455 (worldwide), or email InfoLine@myeloma.org with your questions, or if you wish to discuss the contents of this booklet.
Want answers and don’t want to wait?
Get the answers you need anytime from Myelo® , your 24/7 generative AI assistant that is designed to support you living well with myeloma. Ask Myelo your questions at myeloma.org.
Join the Myeloma Knowledge Platform Visit myprofile.myeloma.org and create your online IMF account to receive the most helpful content recommendations tailored to support your personal myeloma experience.
You are not alone
The International Myeloma Foundation (IMF) is here to help you. We are committed to providing information and support for people with multiple myeloma (which we refer to simply as “myeloma”) and their care partners, friends, and family members. The IMF supports the myeloma community with a broad range of resources available on our website myeloma.org, and through numerous programs and services such as publications, seminars, webinars, workshops, and the IMF InfoLine.
Have questions? We can help
The IMF InfoLine responds to your myeloma-related questions and concerns in a compassionate and caring manner. To receive the most up-to-date information, call 1.818.487.7455 or email InfoLine@myeloma.org, or visit mmsm.link/infoline to schedule a convenient time to talk with an IMF InfoLine Coordinator.
Want answers and don’t want to wait? Ask Myelo®, your 24/7 generative AI assistant at myeloma.org that is designed to support you in your life with myeloma and help you find the right resources.
IMF publications
Myeloma is a cancer that most people have not heard of at the time of their diagnosis. If you have been diagnosed with myeloma or if you suspect that you might have myeloma, the IMF can help you understand this disease so that you can take an active role in your own medical care and make good decisions about your care in partnership with your doctor.
The IMF’s Patient Handbook provides an explanation of myeloma, its diagnosis and risk stratification, its effects on the body, as well as treatment options and supportive care methods. The Patient Handbook will also point you to other helpful resources.
The IMF’s Understanding-series is intended to offer more information about a large range of myeloma-specific topics, including symptoms, treatments, and side effects that may be caused by myeloma or by its treatments.
All IMF publications are free and can be read, downloaded, or requested in printed format at publications.myeloma.org. If you prefer to read IMF publications digitally, just click on the light blue links.
Understanding myeloma vocabulary
Words in bold+blue in IMF publications are explained in a companion booklet, Understanding Myeloma Vocabulary, which you can read or download at glossary.myeloma.org. Myeloma is a complicated disease, but the language that describes it doesn’t have to be hard to understand.
Being comfortable with myeloma-related terms is helpful to understanding the content of these publications and to making your conversations with your doctor more effective.
What you will learn from this booklet
This booklet discusses the drug Lynozyfic™ (also known as linvoseltamabgcpt, its generic drug name). You will learn who can be treated with Lynozyfic, how Lynozyfic works, its dose and schedule, clinical trial experience with Lynozyfic, the special precautions and possible side effects for you to discuss with your doctor, as well as about support programs for patients who are prescribed Lynozyfic.
Who can be treated with Lynozyfic
In July 2025, the U.S. Food and Drug Administration (FDA) approved the use of Lynozyfic for the treatment of adult patients with relapsed/ refractory multiple myeloma (RRMM) who have received at least 4 prior lines of therapy, including a proteasome inhibitor, an immunomodulatory agent, and an anti-CD38 monoclonal antibody. The FDA approval of Lynozyfic expands the treatment options available to patients with RRMM.
How Lynozyfic works
Lynozyfic is an immunotherapy, a treatment that uses the patient’s own immune system to attack their myeloma. Lynozyfic is part of a class of drugs called bispecific antibody therapies. Bispecific antibodies have two (“bi”) arms that target and attach to two types of cells. One arm attaches to a myeloma cell, and the other arm attaches to an immune cell. This is what makes bispecific antibodies a double threat to myeloma.
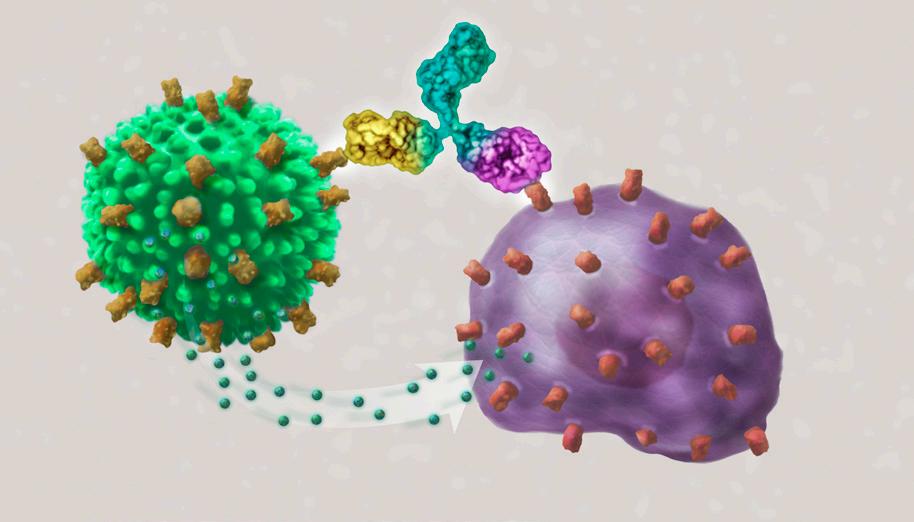
Lynozyfic binds to CD3 on the surface of the T cell CD3


Lynozyfic binds to BCMA on the myeloma cell surface
BCMA tumor-specific antigen on the surface of the myeloma cell
myeloma cell T cell
T cell receptor (TCR)


Lynozyfic activates the T cell to release toxic particles that kill the myeloma cell
Lynozyfic uses one arm to attach to the B-cell maturation antigen (BCMA) on the surface of the patient’s myeloma cells; BCMA is involved in myeloma cell growth and survival. Lynozyfic uses a second arm to attach to the CD3 antigen on the surface of the patient’s T cells (T lymphocytes), a type of white blood cell (WBC). Lynozyfic activates T cells to release lethal particles that connect with and destroy myeloma cells.
A similar strategy, called chimeric antigen receptor (CAR) T-cell therapy, is already used to treat myeloma. With CAR T-cell therapy, a patient’s T cells are collected and modified in a laboratory so that they can attach to BCMA on the surface of a myeloma cell. The modified T cells are multiplied and then re-infused into the patient to attack their myeloma cells.
When compared to CAR T-cell therapy, treatment with Lynozyfic does not require T-cells to be collected, modified, or manufactured. Lynozyfic is an “off-the-shelf” drug that’s ready to be used right away, removing the wait time of several weeks for the patient.
Clinical trial experience with Lynozyfic
A clinical trial is a medical research study with people who volunteer to test scientific approaches to a new treatment or a new combination therapy. Each clinical trial is designed to find better ways to prevent, detect, diagnose, or treat a medical condition, or to answer scientific questions.
A clinical trial is launched only after laboratory studies have shown the potential of a treatment or procedure to be more effective and/or less harmful than previous methods. For patients with myeloma, clinical trials can be part of normal care that may provide earlier access to new drugs and therapies that are not yet available outside of a study.
The LINKER-MM1 clinical trial
Lynozyfic received FDA approval based on data from the LINKER-MM1 phase I/II clinical trial of myeloma patients treated with 200 mg of Lynozyfic as monotherapy (single-agent, or treatment with only one drug at a time). The median patient age was 70 years and 39% of participants had high-risk multiple myeloma (HRMM) based on chromosomal abnormalities, with 28% of patients being “penta-refractory” (resistant to at least 5 drug classes).
At a median follow-up of 11.1 months, the overall response rate (ORR) was 71%, meaning 71% of people who received Lynozyfic responded to it, and 45% achieved complete response (CR) or better. The median duration of response (DoR) was 29.4 months. Lynozyfic at a dose of 200 mg caused deep and durable responses in patients with RRMM who had received many previous treatments.
Finding a clinical trial to match your needs
Myeloma clinical research is very exciting, with many studies enrolling patients. To help you with personalized support for identifying clinical trial options across the U.S., the IMF has partnered with SparkCures. Visit myeloma.org/sparkcures or contact the IMF InfoLine for more information.
If you would like to explore possible participation in a clinical trial, ask your myeloma doctor if a study may be right for you and about the potential risks and benefits that may apply to you. For more information about what’s involved in study participation, read the IMF’s publication Understanding Clinical Trials in Myeloma.
Prophylactic medication
The National Comprehensive Cancer Network (NCCN) Guidelines for myeloma state that the drug tocilizumab can be given as prophylactic to help prevent side effects before treatment with a bispecific antibody. Tocilizumab can be used before treatment with Lynozyfic in order to prevent unwanted events after a treatment with Lynozyfic.
Tocilizumab is not required for the use of Lynozyfic. Ask your doctor if it is recommended in your case. In the LINKER-MM1 clinical trial, tocilizumab was given to 22 patients (18.8%) who experienced cytokine release syndrome (CRS) but did not respond to steroid therapy. See CRS on page 8.
Dose and schedule
The dose and administration information provided below is based on clinical trial data that served as the basis of the FDA approvals. Your myeloma doctor may modify your dose and schedule based on your response to treatment and factors specific to your case.
Lynozyfic is given as an intravenous (IV) infusion into a vein, and you are monitored after receiving your infusions.
¡ “Step-up” dosing is used for the first 2 weeks to help your body adjust to the medication and to lower the risk of side effects. Some medical centers give Lynozyfic on an inpatient basis, with hospitalization for 24 hours on Day 1 of treatment, then again for 24 hours on Day 8. However, some medical centers give Lynozyfic on an outpatient basis.
Step-up dose 1 (week 1) of 5 mg Lynozyfic, 4-hour infusion.
Step-up dose 2 (week 2) of 25 mg Lynozyfic, 4-hour infusion.
¡ After step-up dosing is completed, full dosing is administered once-a-week.
Full dose 1 (week 3) of 200 mg Lynozyfic, 4-hour infusion.
Full dose 2 (week 4) of 200 mg Lynozyfic, 1-hour infusion.
Full doses 3 through 13 (weeks 5 through 15), 30-minute infusions.
¡ Full dosing is continued once every 2 weeks for 5 more doses. Full doses 14 through 18 are given as 30-minute infusions.
¡ After your 18th dose, your myeloma doctor will review your response to treatment and decide if you should continue receiving Lynozyfic once every 2 weeks or if you can receive Lynozyfic once every 4 weeks. Your doctor will decide how long your treatment should continue.
In the LINKER-MM1 clinical trial, patients who achieved a very good partial response (VGPR) or better were switched from receiving Lynozyfic once every 2 weeks to once every 4 weeks. VGPR means that your monoclonal protein (myeloma protein, M-protein) in the serum (blood) and in the urine are detectable by the immunofixation test but not by the electrophoresis test (≥ 90% reduction in serum M-protein, < 100 mg per 24 hours urine M-protein).
If you wish to read the prescribing information for treatment with Lynozyfic, visit regeneron.com/downloads/lynozyfic_fpi.pdf.
Special precautions with Lynozyfic
Before you begin treatment with Lynozyfic, talk with your doctor about any special precautions and possible side effects that may apply to you. If you have already started treatment with Lynozyfic, promptly report any changes in your health to your doctor, including new or worsening signs or symptoms.
Risk Evaluation and Mitigation Strategy (REMS)
REMS programs are required by the FDA for treatments that may have serious safety concerns. REMS programs support the use of treatment and help ensure that the potential benefits outweigh the risks. Lynozyfic is available through a REMS program.
Cytokine release syndrome (CRS)
Cytokines are proteins released by cells that can increase or reduce the growth or activity of other cells. In patients with myeloma, cytokines are produced in the bone marrow and circulate in the bloodstream. Cytokines are normally released in response to low blood counts and infection.
CRS is a potentially fatal, uncontrolled immune reaction in which cytokines trigger an overwhelming immune system response. A “cytokine storm” can seriously damage body tissues and organs. CRS is the most frequent side effect observed with T-cell therapies, but the frequency and severity of CRS are lower with bispecific antibodies than with CAR T-cell therapies.
Lynozyfic step-up dosing is used to decrease the risk of CRS, and patients are monitored following their IV infusions. At the first sign of CRS, immediate assessment must be made to consider if the patient needs to be hospitalized. Supportive care is provided if needed. Further management should follow current practice guidelines. Depending on how bad CRS might be, Lynozyfic therapy may be paused or stopped.
Neurologic toxicities
Immune effector cell-associated neurotoxicity syndrome (ICANS) was reported in 7.7% of the patients in the LINKER-MM1 clinical trial. After treatment with Lynozyfic, ICANS can happen to a patient after they receive Lynozyfic and may happen before, during, or after CRS starts or CRS ends. ICANS can also happen by itself, without CRS.
ICANS may be serious, life-threatening, or deadly. Symptoms of neurologic side effects include but are not limited to confusion, disorientation, loss of consciousness, seizures, tremors, slower movements, changes in personality, depression, tingling and numbness of hands and feet, leg and arm weakness, facial numbness, and difficulty speaking, reading, or writing.
Patients are monitored during treatment with Lynozyfic. At the first sign of neurologic toxicity, including but not limited to ICANS, patients receive supportive therapy based on how serious their symptoms are, and Lynozyfic treatment may be paused or stopped.
Possible side effects with Lynozyfic
These are the most common side effects experienced by participants in the LINKER-MM1 clinical trial.
Infections
Lynozyfic can cause serious, life-threatening, or deadly infections. In the LINKER-MM1 clinical trial, 74.4% of patients experienced infections, with the rate and seriousness going down over time. Do not start treatment with Lynozyfic if you have an active infection.
You will be monitored for signs and symptoms of infection prior to and during treatment with Lynozyfic. Antibiotics and/or antivirals may be prescribed. It is critical that you immediately report any infection to your doctor. Based on seriousness, treatment with Lynozyfic may be paused or stopped.
Your immunoglobulin (Ig) levels will be monitored to assess if you may need to receive intravenous immunoglobulin (IVIG). Be sure to talk to your doctor about the importance of keeping your vaccinations current.
Neutropenia
Lynozyfic can cause neutropenia, a reduced level of neutrophils (a type of white blood cell necessary to combat bacterial infection). Having too few neutrophils can lead to infection. Your complete blood counts (CBC) should be tested at baseline and monitored during treatment.
Febrile neutropenia is the development of fever, often with signs of infection, in a patient with neutropenia. Fever is the most common sign of neutropenia, and it is usually treated with antibiotics. If you have a fever, you must get immediate medical attention.
Lynozyfic support programs
Patient Wallet Card
Patients who are prescribed Lynozyfic will receive a Patient Wallet Card that summarizes the signs and symptoms of problems that may occur with treatment. Patients who develop any of the signs and symptoms listed on the Lynozyfic Patient Wallet Card must seek medical help immediately.
Lynozyfic Surround™
Lynozyfic Surround is a support program offered by Regeneron, the manufacturer of Lynozyfic. This program offers financial and educational resources to help patients throughout their treatment journey with Lynozyfic. Call 1.844.746.4363 and visit regeneron.com for more information.
In closing
This booklet is not meant to replace the advice of your doctors and nurses who are best able to answer questions about your specific healthcare management plan. The IMF provides educational information that will guide you in your conversations with your healthcare team.
To help ensure a good quality of life through effective treatment, you must have an active role in your own medical care. Please visit myeloma.org and join the IMF Myeloma Knowledge Platform at myprofile.myeloma.org.
Click on the links included in this booklet for quick access to a variety of resources. Sign up at subscribe.myeloma.org for our quarterly journal Myeloma Today and weekly e-newsletter Myeloma Minute, as well as alerts about IMF news, events, and actions.

Founded in 1990, the International Myeloma Foundation (IMF) is the world’s leading organization dedicated to multiple myeloma. The IMF is steadfast in its mission: Accelerating the prevention and cure of myeloma and improving the quality of life for patients and families.
The IMF serves people impacted by myeloma at every stage of the disease by combining world-class research, trusted education, global advocacy, and direct support. A cornerstone of this work is the International Myeloma Working Group® (IMWG) – a network of more than 300 internationally renowned researchers and clinicians who establish the guidelines that shape how myeloma is diagnosed, treated, and managed across the globe.
Through its global network of support groups, educational programs, its 24/7 generative-AI myeloma assistant Myelo® , its InfoLine staff, and its advocacy for greater healthcare access, the IMF helps people living with myeloma and their care partners navigate diagnosis, treatment, and survivorship. At the same time, the IMF ensures scientific advances translate into better care and outcomes.