Predictable Immediate Implant Placement Starts with Biology
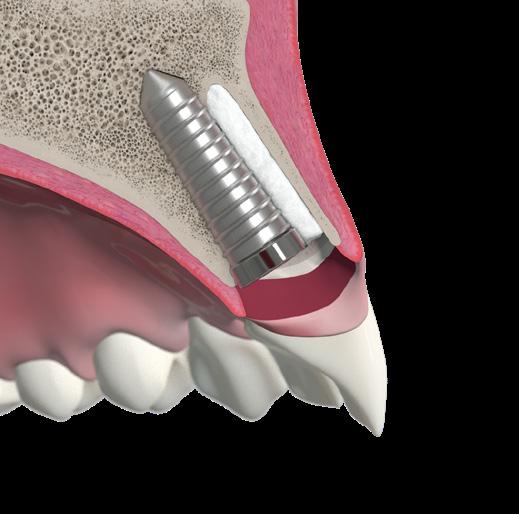
When biologic principles are respected, aestheticzone outcomes become consistent and stable.
THE BIOLOGIC ADVANTAGE
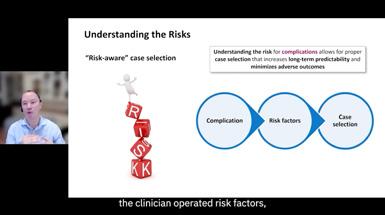
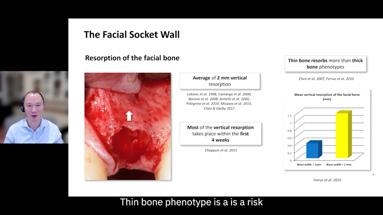
Know facial bone anatomy to improve case selection.
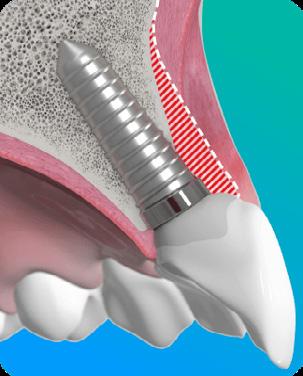
Manage remodelling to preserve contour and papillae.
Control soft tissue phenotype to support long-term aesthetic stability.
Immediate implant placement becomes predictable when biology and protocol work together.
Your Roadmap to Predictable Aesthetic Outcomes
Identify the Right Case
Recognise ideal and manageable risk situations Apply a Structured Decision Framework
Use biologic criteria to guide treatment planning
1 2 4 5 3
Follow the 10 Keys Protocol Execute a sequential roadmap for stability Manage Gap & Soft Tissue Strategically Support long-term volume and contour See Real-World Applications
Learn from expert-led aesthetic zone cases
STEP 1: Identify the Right Case
The criteria below help you quickly assess risk, guide decision-making, and determine when immediate placement in the aesthetic zone is appropriate – or when it’s not.1
Core Eligibility Criteria
↪Ideally, these should be fulfilled.
ࠦ Both the buccal and palatal walls should be intact
ࠦ ≥3–4 mm of apical bone for primary stability
ࠦ Facial bone of at least 1 mm in thickness
ࠦ No acute infection with pus or bone destruction
ࠦ At least 35 Ncm insertion torque or ISQ of 70 (if aiming for immediate loading)
Gap between facial bone and planned implant position >2 mm
intra-operative assessment ࠦ LOW RISK
Minimally invasive extraction
Primary stability achieved
Ideal 3-dimensional position achieved
ࠦ
Ideal IIP Case
• Predominantly favourable factors
• High predictability
• Standard IIP protocol
⚠ MEDIUM RISK
Buccal defect <5 mm
Thin phenotype
Apical bone for primary stability
Chronic periodontal infection and controlled periodontal disease
Minor recession
Gap between facial bone and planned implant position 1–2 mm
⚠ MEDIUM RISK
Damage to surrounding soft tissues including severed and detached papillae
OCTAGON-XMARK HIGH RISK
Marked buccal defect (>5 mm)
Severe thin phenotype
Lack of apical bone for primary stability
Acute infection and periodontal disease
Gingival recession >2 mm
Gap between facial bone and planned implant position <1 mm
OCTAGON-XMARK HIGH RISK
Significant damage to soft tissues and bone
Lack of primary stability
Facially positioned or overangulated implant or excessive implant depth
⚠ IIP with Caution
• Multiple medium-risk factors
• Advanced techniques required
• Grafting and contour management critical
Dr. Stephen Chen on the ITI treatment guide for immediate implant placement
OCTAGON-XMARK Avoid IIP
• One or more high-risk factors
• High aesthetic or biologic risk
• Consider early or delayed placement
Immediate implant placement begins with the right decision—but long-term success is driven by how hard and soft tissues are managed. The following 10 Keys outline the principles that support predictable regeneration and aesthetic stability.
2. Lambert F, et al.: Pre-operative analysis and treatment planning. In D. Wismeijer, Bart, & N. Donos (Eds.), ITI treatment guide 14: Immediate implant placement and restoration in partially edentulous patients (Vol. 14). Quintessence, 2023. (Table above is a truncated list,
STEP 3: Follow the 10 Keys to Success
Your practical checklist from planning → surgery → restoration.3-5
The following 10 Keys, described by Dr. Robert A. Levine, outline a practical, sequential checklist for predictable aesthetic-zone immediate implant placement.
Aesthetic risk assessment
• Smile line • Gingival phenotype • Patient’s expectations
• Implant selection and positioning to ensure a buccal gap >2 mm 1 2 treatment planning
CBCT analysis and IOS
Virtual surgical and restorative-driven treatment planning
CONSIDER:
• Intact buccal bone wall — the thicker, the better (>1mm if possible)
• Alveolar process at least 8 mm wide
• Position of the alveolar socket inside the bone envelope
Minimally traumatic tooth extraction (flapless if possible)
• Assess buccal and palatal plates after extraction
• If buccal height is compromised, consider an alternative protocol6
3D implant placement (using a surgical guide)
• Good bone availability for palatal wall implant positioning
Use of a narrow or regular diameter implant
• Achieve primary stability and maintain a buccal gap >2 mm
Buccal gap bone grafting (with low substitution material)
Screw-retained final restoration (when possible) 8 9 10
Immediate or delayed emergence profile management
• Customised healing abutment or temporary crown
Use of a custom impression coping technique
• To duplicate the created transition zone
If a key cannot be achieved at any stage, clinicians should pause and consider early or delayed implant placement instead.
STEP 4: Manage Gap & Soft Tissue Strategically
Strategic gap and soft-tissue management preserves long-term aesthetic outcomes.
Why Gap Management Matters
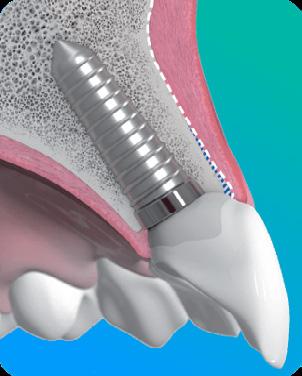
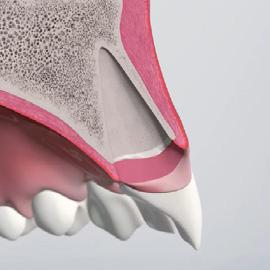
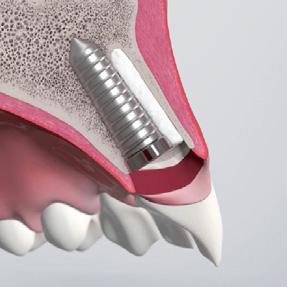
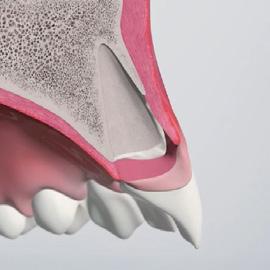
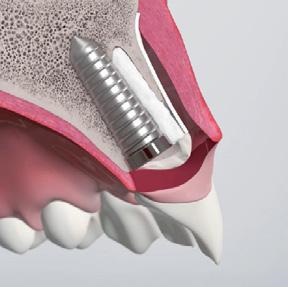
While implant positioning is critical, it does not prevent post-extraction remodelling. Biomaterials play a key role in managing the peri-implant gap and maintaining long-term hard- and soft-tissue stability.
Dr. Stephen Chen discusses the role of biomaterials and grafting in managing the peri-implant gap in immediate implant placement.
“Placing an implant does not stop facial bone remodelling. The implant is a passive occupant — reconstruction with biomaterials is required to maintain volume and long-term hard- and soft-tissue stability.”
Clinical Impact of Gap Grafting
Evidence supporting this approach
Geistlich biomaterials for immediate implant placement
50+ peer-reviewed IIP studies covering 1,100+ patients and 1,300+ implants8
High long-term implant survival demonstrated with Geistlich Bio-Oss® and Geistlich Bio-Oss Collagen®
Largest evidence base in immediate implant placement with long-term follow-up
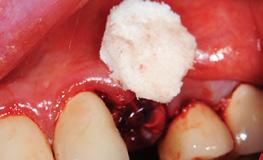
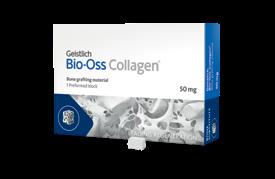
Filling the gap with Geistlich Bio-Oss Collagen®
WATCH WEBINAR
7. Cardaropoli D, et al. Int J Periodontics Restorative Dent. 2014
(clinical study)
Data on file. Geistlich Pharma AG, Wolhusen, Switzerland.
Tissue Grafting Options for Long-term Stability
Selecting the right grafting strategy supports long-term hard- and soft-tissue stability in immediate implant placement.
When grafting is indicated, the choice of technique and biomaterials depends on whether the buccal bone wall is preserved or compromised.
Preserved buccal wall ↷
Fill the Gap: stabilise the clot and support ridge contour stability.
Defective buccal wall <5 mm ↷
Fill + Protect: stabilise the clot and limit soft-tissue ingrowth to support aesthetics .
Soft-Tissue Augmentation
Buccal soft-tissue augmentation becomes relevant when the thickness of keratinised tissue is <2 mm, as thin phenotypes are associated with a higher risk of recession and contour loss.
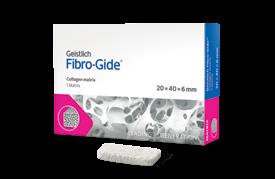
A collagen matrix such as Geistlich Fibro-Gide® can be used to increase tissue thickness and support long-term aesthetic stability.8
STEP 5: See Real-world Applications
Follow the roadmap in action — from diagnosis to stable aesthetic results.
You’ve got the principles, now see how they’re applied in real-world clinical
scenarios.
Immediate Implant Placement and Provisionalisation for Anterior Aesthetics David E. Urbanek, DMD, MS | St. Louis, MO
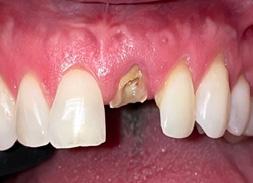
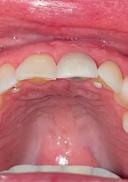
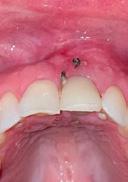
A healthy, 56-year-old female presented with fractured, endodontically treated tooth #9. The tooth was fractured at the gingival level and asymptomatic. Both the patient and the restorative dentist had high aesthetic expectations, and preferred immediate implant placement with Provisionalisation if possible.
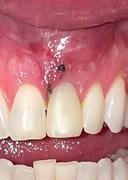
1. Pre-operative image showing a fractured, endodontically treated tooth #9.
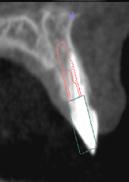
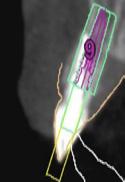
2. Image 2a: Pre-operative sagittal CBCT image demonstrating a Kan Class 1 sagittal root position with initial digital implant planning conducted during the consultation appointment. Image 2b: Definitive digital implant planning.
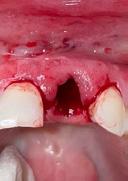
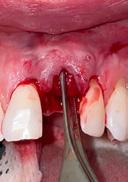
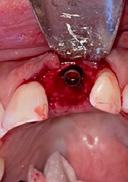
3. Image 3a: Tooth #9 was extracted with minimal flap elevation, preserving the papillae. Image 3b: A 3.6 x 15 mm implant was placed in a fully guided manner with a palatal bias to maximise the facial gap dimension, achieving a +2 mm gap.
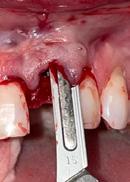
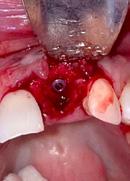
4. Image 4a: The underside of the periosteum was incised just apical to the mucogingival junction, and a supra-periosteal pocket was created using sharp dissection with a #15 blade. Image 4b: The facial gap was packed with 50 mg of Geistlich Bio-Oss Collagen®. A cover screw was temporarily placed to prevent bone graft granules from entering the implant chamber.
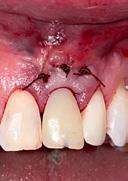
5. Image 5a: A 15 x 20 x 3 mm Geistlich FibroGide® collagen matrix was inserted into the supra-periosteal pocket, with the coronal portion positioned to cover the facial bone crest. Image 5b: The provisional crown was placed, and the facial mucosal flap was coronally advanced to cover the Geistlich Fibro-Gide® collagen matrix.
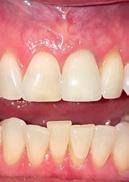
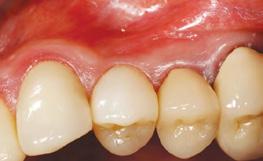
7. Images 7a & 7b: Final restoration at 16 months post-operative.
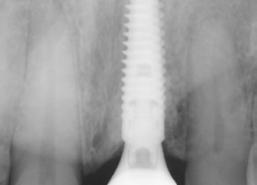
8. Periapical radiograph at 16 months postoperative demonstrating stable crestal bone levels.
“To obtain the best result with challenging cases, such as this one, I always approach them with thorough pre-surgical assessment, proper hard- and soft-tissue management, and the use of high-quality, evidence-based materials.” — Dr. David E. Urbanek
Phenotype Modification Using Geistlich Fibro-Gide® for Immediate Implants in the Aesthetic Zone
Robert A. Levine DDS
A healthy non-smoking 50-year-old female patient who desired a single-tooth solution to replace a non-restorable tooth, #12. A root fracture at the level of the palatal post was diagnosed in a root canalled tooth. Maintaining aesthetics of the adjacent teeth was important as they are also restored with single full coverage porcelain crowns.
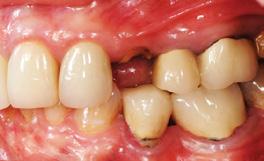
1. Pre-operative assessment demonstrates minimal zone and thickness of buccal keratinised gingiva, with a medium periodontal phenotype.
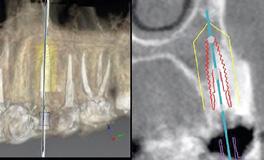
2. Pre-operative CBCT with virtually planned implant placement. A thin buccal plate (<1 mm) is measured. Good apical bone is noted for the placement of a Straumann® 12 mm x 4.1 mm bone level tapered implant.
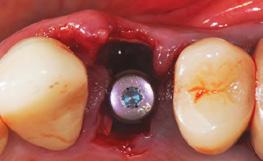
3. Minimally invasive removal of #12 using only a buccal approach mini-flap showing an intact buccal plate with immediate placement of the implant (1 mm below the intact buccal wall) in a screw-retained position. A 3 mm buccal gap is measured and a 1.5 mm palatal gap.
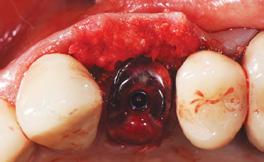
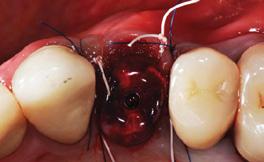
4. Both the buccal and palatal gaps have been packed with Geistlich Bio-Oss Collagen® hydrated with Gem 21S. I prefer to squeeze Geistlich Fibro-Gide® between thumb and forefinger, prior to placement. A dry-carved piece of Geistlich FibroGide® is in position thinned approximately 2 mm with beveling laterally and coronally with a new #15 blade.
5. Geistlich Fibro-Gide® in place facial to the intact buccal wall under a full thickness buccal approach mini-flap. Immediate contour management was completed using an Anatotemp® for a maxillary bicuspid tooth.
6. Suturing completed using 4-0 PTFE and 5 -0 polypropylene nonresorbable sutures. Anticipated short-term 25% postoperative swelling is discussed with the patient.
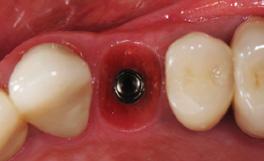
7. 3 months post-operative appointment showing a welldeveloped subgingival transition zone created with immediate contour management. A reverse torque test was completed, and the case proceeded to completion.
8. 14-month post-operative view with final screw-retained crown in place. Good interproximal papilla healing is noted with thickening of the buccal periodontal phenotype compared with Fig. #1. (Restorative Therapy: Drew Shulman DMD, MAGD; Philadelphia, PA)
“The importance of the ‘one-two punch’ of ROUTINE phenotype modification using Geistlich Fibro-Gide® in conjunction with bone grafting the >2 mm buccal gap with Geistlich Bio-Oss Collagen® provides excellent buccal convex tissue maintenance long-term.”
— Dr. Robert A. Levine
5-STEP Roadmap
STEP 1:
Identify the Right Case Predictability starts with disciplined case selection and biologic assessment.
STEP 2: Apply a Structured Decision Framework
Combining biologic factors and risk modifiers reduces uncertainty.
STEP 3:
Follow the 10 Keys to Success Structured execution — from planning to restoration — minimises complications.
STEP 4: Manage Gap & Soft Tissue Strategically Hard- and soft-tissue management preserves contour and long-term aesthetics .
STEP 5: Apply in Real Clinical Cases When the protocol is respected, predictable aesthetic outcomes follow.